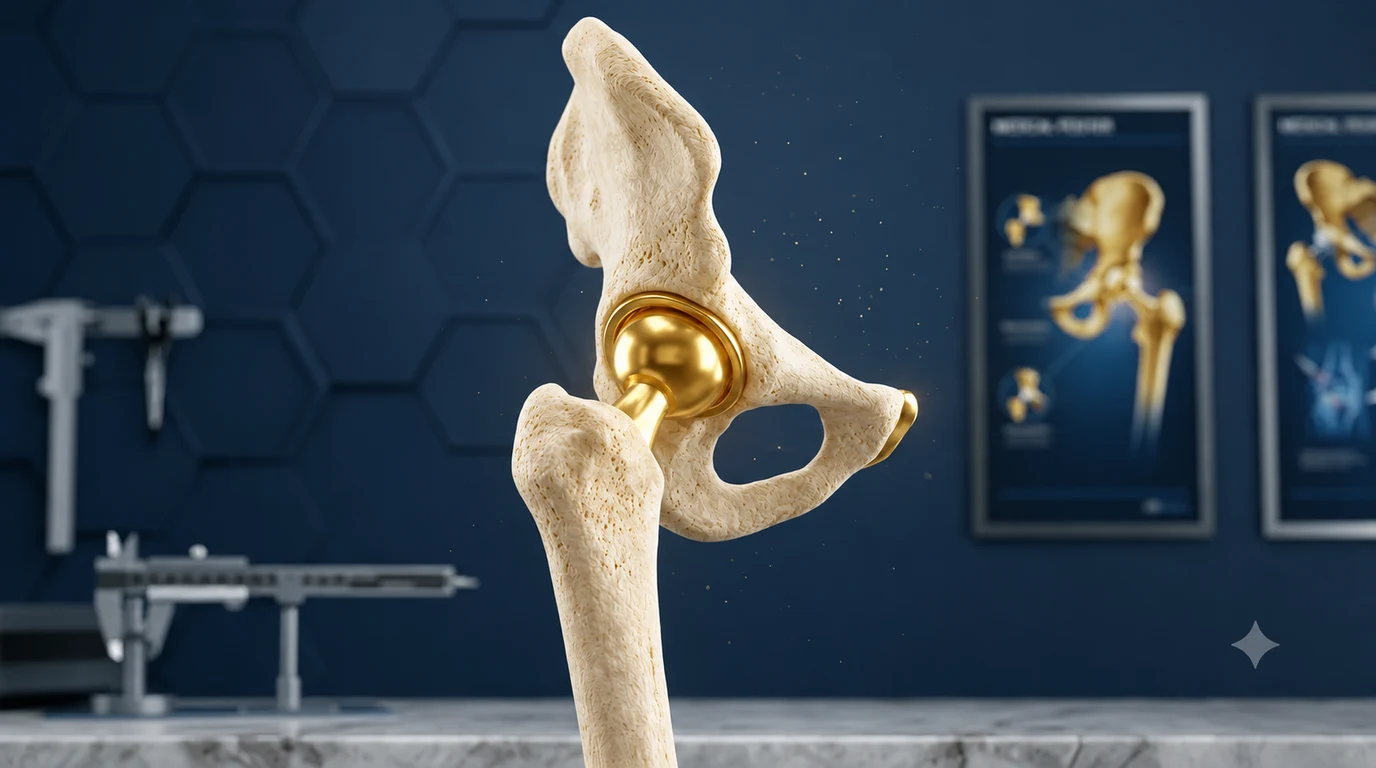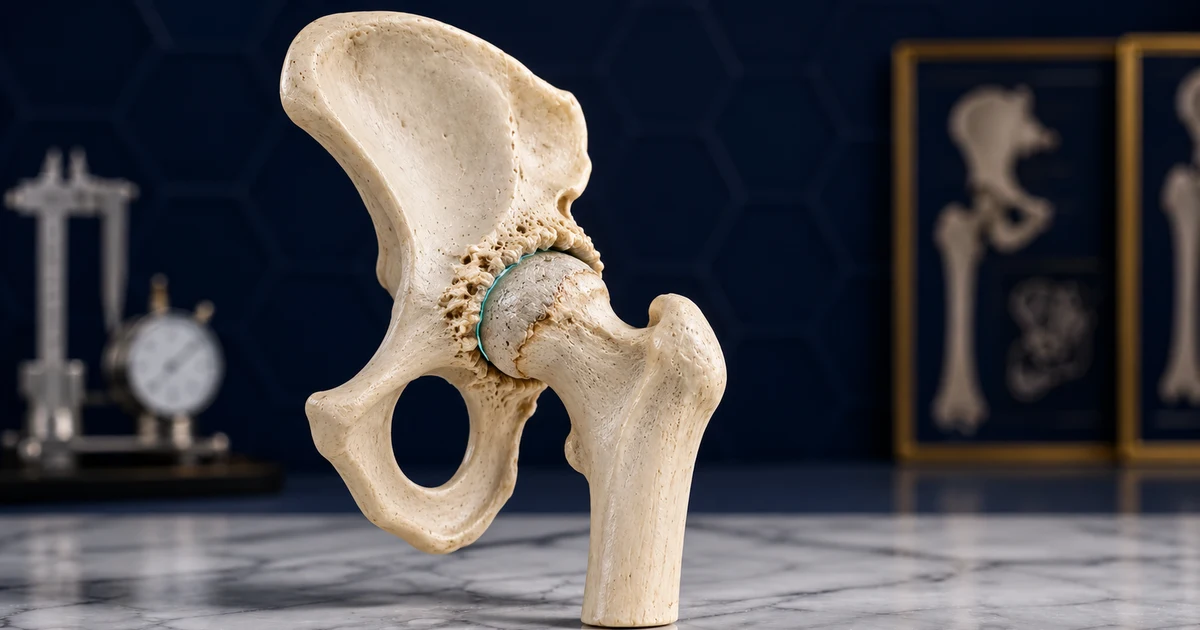
Hip replacement is an option when pain and stiffness disrupt walking, sleep, or simple tasks and non-surgical treatment is insufficient. The aim is to reduce pain and improve movement and independence. This guide explains the decision, preparation, and the day of surgery, and answers common questions about returning to everyday life. It focuses on primary total replacement using this clinic’s direct lateral approach, through the side of the joint; surgery for a fracture or revision replacement has a separate plan.
🦴 What is hip osteoarthritis, and when does it need surgery?
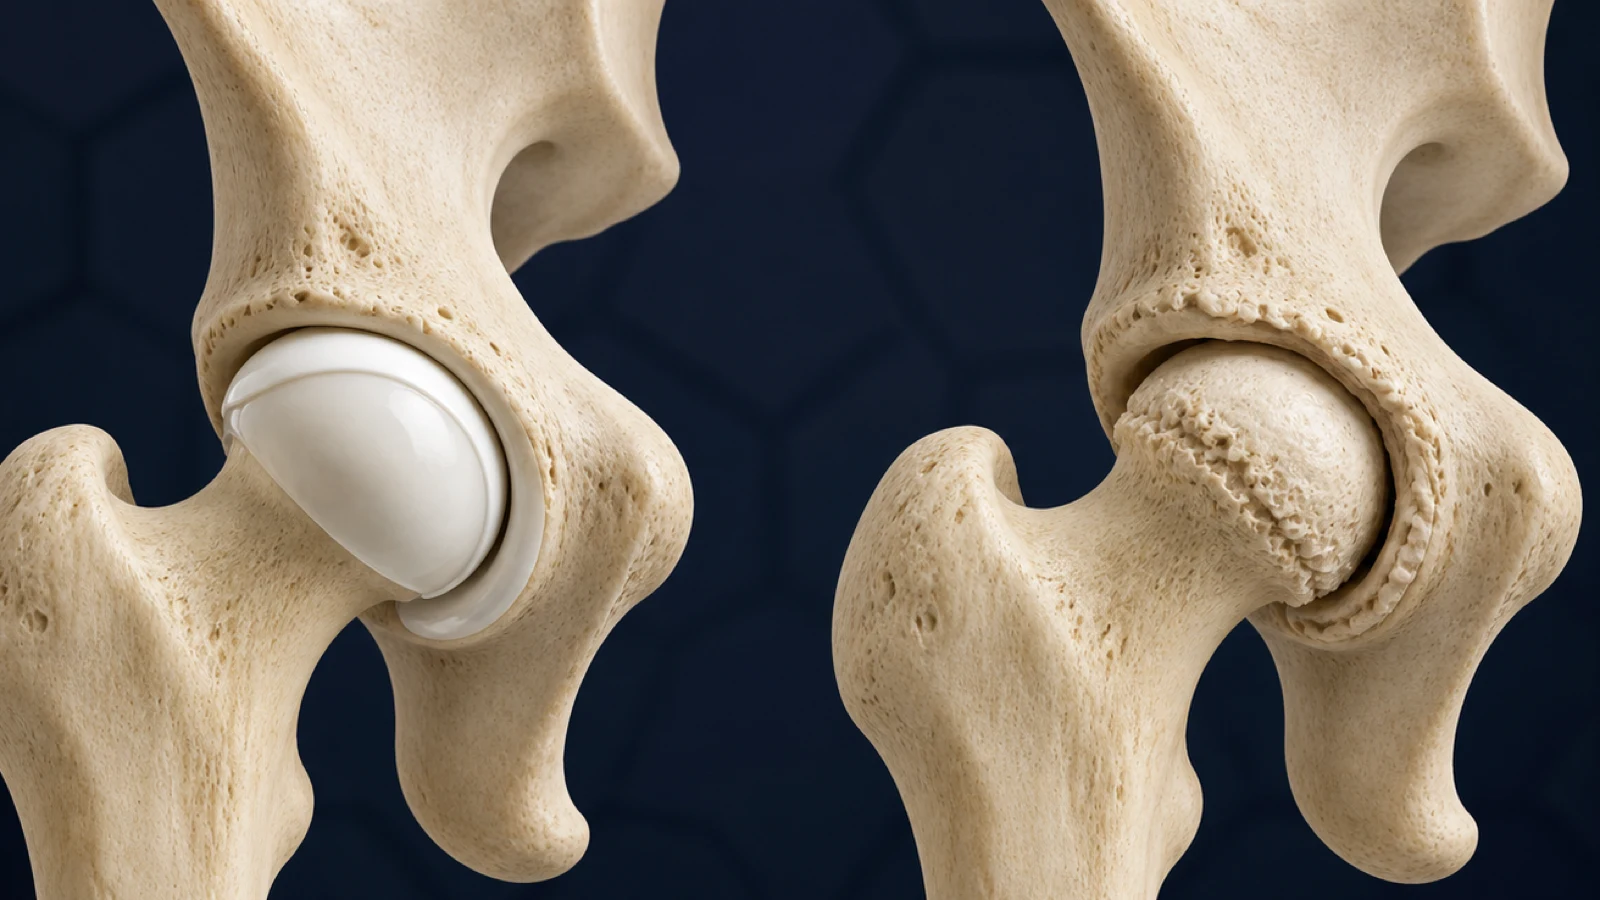
The hip joint is where the rounded head of the thigh bone fits into a socket in the pelvis. Cartilage on both surfaces allows smooth movement. In osteoarthritis, cartilage and other joint tissues change, causing pain and stiffness. Pain is often felt in the groin or front of the thigh but may extend to the knee. Difficulty putting on socks or rising from a chair can indicate limited movement.
Arthritis is not the only reason for replacement: old injury, some inflammatory diseases, or impaired blood supply to the femoral head can also damage the joint. Pain location and cause must be clear when choosing treatment. Not all pain around the hip comes from the joint; back or tendon pain may need a different approach. Examination and X-rays help distinguish these causes.
Non-surgical care may include suitable exercise, activity modification, weight loss when needed, appropriate medicines, and a cane. These treatments aim to control pain and maintain function. Surgery is not required if they provide an acceptable quality of life. If pain persists at rest or at night and daily tasks remain limited despite appropriate treatment, discussing replacement is reasonable.
Surgical decisions consider quality of life, examination and imaging, and individual risks together. Age and weight alone do not establish suitability. Hip replacement often improves pain and everyday activity, but results vary. If your goal is high-impact sport or a particular movement, discuss its possibilities and limits before surgery.
⏳ What happens if you do not have surgery?
For usual osteoarthritis, replacement is elective; surgery is not required merely to prevent an uncertain future event. Some patients maintain acceptable function with non-surgical care for a long time. Changes in pain and limitations differ between people; not every short delay harms a future result. Time to decide and prepare is part of informed treatment.
Persistent pain may reduce activity, weaken muscles, and decrease movement. In some patients, deformity or bone loss increases and surgery becomes more complex. This does not happen to everyone. If pain is costing you sleep, walking, or independence, do not postpone reassessment until complete disability.
While waiting, maintain tolerable activity and use a suitable walking aid. A cane can reduce strain and limping and support safer movement. If severe hip pain starts suddenly without an injury, seek urgent assessment. If you have severe pain after a fall, or cannot walk or put weight on the leg, go to the emergency department immediately; do not simply attribute these symptoms to arthritis. Appropriate timing depends on joint condition, general health, and your goals.
🏋️ Preparing for surgery
Preparation does not mean achieving unrealistic strength in a few days. The aim is to preserve current ability, undertake suitable activity, and understand the return-home plan. Evidence on exercise before hip replacement, particularly its long-term effects, is inconsistent. Light, tolerable activity is useful, but should not continue through sharp pain, more limping, or increased night discomfort.
Before surgery, practise walker use, rising from a chair, and moving safely at home. Calling a movement a strengthening exercise does not make it suitable if it worsens pain. Exercise should match examination findings and current ability. Do not confuse preoperative preparation with postoperative restrictions: after this clinic’s lateral approach, exercises that move the operated leg out to the side (hip abduction) are prohibited through the end of week 6.
Blood glucose, anaemia, and underlying illnesses are checked before surgery. Report active infection in the skin, teeth, or elsewhere so it can be treated appropriately. Bring a full list of medicines and supplements. Seek help to stop smoking; this supports general preparation and wound healing. Do not change blood thinners or diabetes medicines on your own.
Prepare a firm chair with arms and a seated toilet or suitable aid. Remove slippery rugs and cables and keep the night-time route to the toilet lit. Suitable shoes and tools such as a long shoehorn reduce difficult bending. Arrange help with shopping, meals, and transport during the first days; tell the team before admission if you live alone.
🏥 The day before surgery and the day of surgery
The sequence is similar in most centres: admission and changing into theatre clothing, checking vital signs and inserting an IV line, meeting the anaesthetist and signing consent, and the surgeon marking the correct leg. Site marking is a standard safety step; remind the team if it has not happened. You then go to the operating room. Your family waits during this time, and the surgeon tells them the outcome after surgery.
- Fasting: For healthy adults having scheduled, non-emergency surgery, allow at least 2 hours between the last clear liquid, such as water, and anaesthesia, 6 hours after a light meal, and at least 8 hours after fatty food or meat. Milk is not a clear liquid. Diabetes, delayed stomach emptying, and some medicines may change the plan; your anaesthetist’s written instructions take priority.
- Medicines: Bring a complete list of the medicines, supplements, and herbal products you take. Daily medicines, particularly blood thinners and diabetes medicines, must be discussed with the surgeon and anaesthesia team beforehand; do not stop or add any medicine on your own.
- Bathing: Shower the night before or on the morning of surgery according to hospital instructions. Do not shave the surgical area at home with a razor; small cuts can provide an entry point for infection.
- Bring: Identification and insurance documents, recent X-rays and tests, a medicine list, a walker or cane, comfortable loose clothing, and enclosed non-slip shoes.
- Remove nail polish and jewellery, and arrange a companion for the day of surgery and the first days at home.
⚕️ How is hip replacement performed?
The operation may use spinal or general anaesthesia. The anaesthetist chooses according to your illnesses, medicines, and circumstances. Spinal anaesthesia numbs the lower body, and you may also receive sedation. Pain control and what to expect from anaesthesia are explained before surgery.
The usual method in this clinic is the direct lateral approach: the surgeon accesses the joint from its side. Part of the attachment of the muscles that move the hip sideways is moved aside for access and repaired at the end. Protecting this repair explains the early restriction on hip-abduction exercises. Other approaches also exist; none is best for every patient.
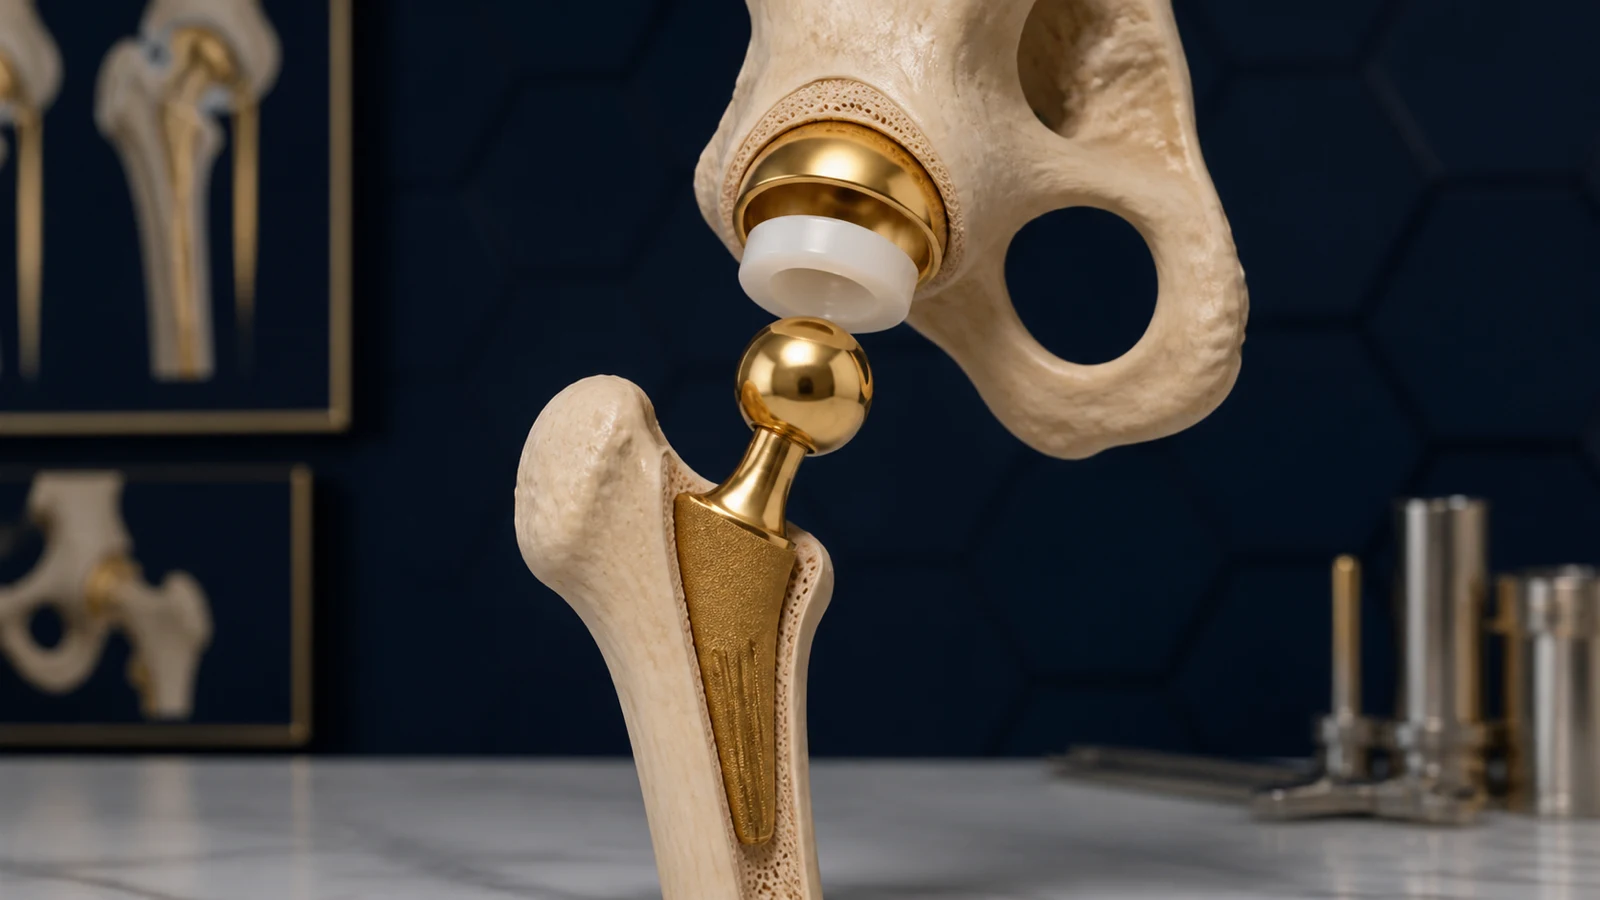
The damaged femoral head is removed and the pelvic socket prepared for an artificial cup. A smooth bearing surface sits inside the cup. A stem is inserted into the thigh bone, and a new round head placed on it. These components restore the joint’s ball-and-socket movement. Fixation and materials are selected according to bone condition and your needs.
At the end, the surgeon checks stability, movement, and leg lengths. Appropriate length and tension are sought, but a feeling of unequal legs after surgery does not always mean a true bone-length difference and needs assessment. Tissues are closed and dressed, and you go to the recovery area for monitoring after anaesthesia. Monitoring does not end on arrival there; pain and general condition remain under review.
Infection, clots, dislocation, fracture around the artificial joint or prosthesis, and possible revision surgery are risks discussed during consent. Their existence does not mean they will occur in your case. Most patients benefit from less pain and better daily tasks, but improvement is gradual and activity restrictions matter. The goal is a joint that serves your life, rather than a guarantee for every sport.
🗓️ Recovery at a glance
The usual stay in this clinic is 1 to 2 nights. Walking with a walker and weight bearing as tolerated start with rehabilitation; special circumstances may require a different plan. After the direct lateral approach, active hip-abduction exercises are not performed through the end of week 6. Less pain does not end this muscle-protection restriction earlier.
The walking aid is gradually reduced as strength and walking improve. Pain control, wound care, and correct exercise all support recovery. Read the guide to care and rehabilitation after hip replacement for full instructions and progression criteria. This article gives an overview; the staged exercise plan is in the postoperative guide.
🎯 Returning to everyday life: answers to 20 questions
1) How much pain will I have, and how long will it last?
Pain and swelling usually improve over 3–4 weeks, but swelling can last 3–6 months; this does not mark a definite end to pain. Contact the clinic for assessment if pain is new, increasing, or not controlled by your prescription.
2) How many nights will I stay in hospital?
The usual stay in this clinic is 1 to 2 nights. Discharge follows pain control, recovery of general condition, and learning safe movement. Arrange a companion’s help with early tasks and transport beforehand.
3) When can I put weight on the operated leg?
Weight bearing as tolerated with a walker starts on the day of surgery or the next day; this clinic usually applies this plan to both cemented and uncemented fixation. Take short steps with toes facing forward and do not pivot on the operated leg. Special circumstances during surgery may require a different plan.
4) How long will I need a walker or cane?
A walker is usually needed for 2–4 weeks; before changing aids, you should be able to stand and walk for more than 10 minutes without leaning your weight on the walker. Then use a cane in the hand opposite the operated leg until you walk without a limp or the pelvis dropping to one side. This stage often lasts to around 6 weeks.
5) When are stitches or staples removed?
Stitches or staples are usually removed around two weeks (14 days) after surgery. The waterproof dressing stays until the first clinic visit unless it becomes wet, dirty, loose, or blood-stained earlier. Report repeated drainage, a bad smell, or opening wound edges the same day.
6) When does physiotherapy start, and how long does it continue?
Simple exercises begin on the day of surgery or day 1, and formal physiotherapy on day 2 in hospital. After discharge, arrange your own physiotherapy appointment and continue home exercises. For planning, early rehabilitation takes place in the first 6 weeks, with strengthening and gait improvement during months 3–6. In-person sessions depend on progress; not everyone needs prolonged sessions. Hip-abductor exercises are added from week 7; do not start them earlier.
7) When can I drive?
Driving is considered around 6 weeks after surgery on either side. You should enter and leave the car without a cane or pain and perform an emergency stop quickly and without pain. Do not drive while taking opioids, alprazolam, or gabapentin; first practise braking in a car with the engine off.
8) When can I return to desk or seated work?
Desk work usually resumes 4–6 weeks after surgery. Short movement breaks and adjusted hours are useful at first. Prepare your commute and a suitable chair before returning.
9) What about standing or heavy work?
Prolonged standing work is usually considered at 6–12 weeks, after stopping the cane and walking without a limp. Heavy work takes around 3 months; ask others to carry heavy loads during this time. The job and your next-day response to increased activity influence return speed.
10) How should I use stairs?
At first, take stairs one step at a time: lead with the unaffected leg going up, and with the walking aid followed by the operated leg going down. Hold the handrail and have someone with you until your strength and balance are adequate. Practise stairs in hospital; do not carry the walker onto a step while relying on it for support.
11) How should I sleep?
From the first night, you can sleep on your back or unaffected side; when side-sleeping in the first 6 weeks, place a pillow between the knees and calves. Sleeping on the operated side may be possible after stitch removal, around day 14, if wound pressure is not significantly painful. Sleeping on your stomach is considered from week 7; do not let the leg move backwards with the toes turned out.
12) When can I shower?
A short shower may be possible from 48 hours after surgery if the wound is dry and the waterproof dressing is intact and firmly attached. Do not direct a strong stream of water onto the dressing; if water gets underneath it, change it the same day. A shower chair and a helper reduce the risk of a fall during the first showers.
13) How should I pray?
Use a chair through the first 3 months. After the end of month 3, bowing and prostration on the floor may be considered if kneeling on a soft mat is comfortable; continue using a chair for tashahhud and prolonged sitting. This is movement advice; ask your religious authority about permissible alternatives.
14) When can I resume sexual activity?
Once the wound is closed and stitches removed, sexual activity can usually resume during weeks 3–6. During the first 6 weeks, lying on your back or unaffected side with a pillow between the knees can be lower-strain options if pain-free. Do not move the operated leg backwards and rotate it outwards at the same time; stop if pain or a shifting sensation occurs.
15) When can I travel or fly?
During the first 5 weeks of prescribed clot-prevention treatment, postpone long flights or land journeys if possible. If travel is unavoidable, plan stops, short walks, and ankle movements; walk along the aircraft aisle every hour. Contact the clinic before buying a ticket for a flight longer than 4 hours.
16) Which sports are suitable after hip replacement?
Low-impact sports such as swimming, outdoor cycling, or light hiking are considered after month 3. The wound should be fully closed and you should walk without a cane or limp. Start with short duration and low intensity, adjusting to next-day pain or limping; rehabilitation walking and stationary cycling have separate, earlier schedules.
17) What about running, football, and impact sports?
Regular running, jumping, skiing, and contact sports are not recommended in this clinic. Choose low-impact activity to preserve strength and fitness while putting less strain on the prosthesis. A history of professional sport does not automatically remove this restriction.
18) What about floor sitting and squat toilets?
Sitting cross-legged, prolonged kneeling, and squat toilets are not recommended; a chair and seated toilet or toilet adapter are preferable. If floor sitting is unavoidable after month 3, use a firm support and keep the operated leg extended when sitting down and getting up. A full squat or strong hip twisting is not a shortcut to floor sitting.
19) Will my legs be different lengths after surgery?
The surgeon checks leg length and stability during surgery, but some patients initially feel a difference. This may relate to stiffness, pelvic position, or walking pattern and does not always mean a true bone-length difference. A persistent feeling should be examined; do not add a shoe lift on your own.
20) How many years does an artificial joint last?
A review published in 2019 found that about 58% of primary total hip replacements in Finnish registry data had not needed revision by 25 years. This historical estimate is not a guarantee for modern prostheses or an individual patient; wear, infection, loosening, and bone condition affect durability. Regular follow-up and reporting new pain or limping remain important even after years without problems.
✅ Your next step
Hip replacement aims to reduce pain and improve everyday life. When non-surgical treatment is insufficient, choose timing according to limitations, general health, and your goals. Preparing the home and learning walker use support a safer start. Discuss the approach, early restrictions, and realistic expectations before surgery so the plan fits your needs.
To discuss treatment options and prepare for surgery, call Dr Jalil Emad’s clinic on 0913 782 5207, or book an appointment online.
Read more about treatment methods on this page: Total hip replacement.
Related guides: Post-operative care and rehabilitation: Total Hip Replacement Surgery: Postoperative Care and Rehabilitation · Service page: Joint Replacement & Reconstruction
This guide is for your education and preparation. Treatment is chosen after an examination, review of imaging, and discussion of your circumstances and goals.
📚 Scientific references
View scientific references
- NICE NG157 Primary hip, knee and shoulder joint replacement, 2020 · www.nice.org.uk
- ACR/AAHKS optimal timing elective arthroplasty guideline, 2023 · assets.contentstack.io
- AAOS OrthoInfo Total Hip Replacement · www.orthoinfo.org
- AAOS OrthoInfo Activities After Total Hip Replacement · www.orthoinfo.org
- Svinøy et al. Prehabilitation for older patients awaiting total hip replacement, RCT 2025 · pmc.ncbi.nlm.nih.gov
- ASA Practice Guidelines for Preoperative Fasting, Anesthesiology 2017;126:376–393 · www.asahq.org
- 2023 American Society of Anesthesiologists Practice Guidelines for Preoperative Fasting: Carbohydrate-containing Clear Liquids with or without Protein, Chewing Gum, and Pediatric Fasting Duration-A Modular Update of the 2017 American Society of Anesthesiologists Practice Guidelines for Preoperative Fasting · Anesthesiology · 2023 · pubmed.ncbi.nlm.nih.gov
- NICE NG125 Surgical site infections: prevention and treatment, updated2020 · www.nice.org.uk
- WHO Surgical Safety Checklist Implementation Manual, 2009 · www.who.int
- AAOS OrthoInfo Minimally Invasive Total Hip Replacement · www.orthoinfo.org
- Surgical approach in primary THA: anatomy, technique and clinical outcomes, 2015 · pmc.ncbi.nlm.nih.gov
- Hull University Teaching Hospitals NHS Total Hip Replacement, updated31October2024 · www.hey.nhs.uk
- Bexley NHS Total Hip Replacement rehabilitation milestones · msk-bexley.nhs.uk
- How long does a hip replacement last? A systematic review and meta-analysis of case series and national registry reports with more than 15 years of follow-up · The Lancet · 2019 · doi.org
- AAOS OrthoInfo · Osteoarthritis of the Hip · www.orthoinfo.org
- NHS · Hip pain in adults · reviewed20November2025 · www.nhs.uk
- NHS · Preparing for surgery · reviewed9July2024 · www.nhs.uk
- NHS · Preparing for a hip replacement · reviewed6March2024 · www.nhs.uk