🏥 What happens on the day of total hip replacement surgery?
Anaesthesia: The operation is done under spinal anaesthesia together with a sedative, or under general anaesthesia, and the choice depends on your physical condition and on the anaesthetist’s opinion. Sometimes, to ease pain in the first hours, a local anaesthetic is injected around the joint during the operation, or the nerve at the front of the thigh is numbed for a while. After the operation, the anaesthesia team checks your alertness, blood pressure, pain, nausea, and the feeling and movement in your leg.
Moving from the day of surgery: You start moving your ankle and tightening your thigh and buttock muscles from the first few hours. Your first walk with a walker takes place on the day of surgery or, at the latest, the day after. In Dr Emad’s programme, whether the artificial hip joint (implant) has been fixed in the bone with cement or without cement, you put weight on the operated leg from that same day, as far as pain allows. Physiotherapy sessions start on the second day after surgery and continue at a physiotherapy centre after discharge; you book these sessions yourself.
Hospital stay and discharge: In Dr Emad’s programme, you stay in hospital for 1 to 2 nights, and a check X-ray of the hip is taken before discharge. Before you go home, you must be able to get out of bed and back into it by yourself, walk on a flat surface with the walker, and go up and down 2 to 3 steps. Your pain must also be bearable, and you must be able to eat, drink and use the toilet. Before discharge, you also learn the movement precautions for the first 6 weeks.
For home: You receive your instruction sheet and the prescription for your medicines at discharge. From the first day at home you will need the walker, a cane for the stairs, compression stockings and a sturdy, ordinary-height chair with armrests; if the toilet at home is a squat toilet, also prepare a commode chair to place over it. Until the end of the third month, sleep in a bed, not on a mattress laid on the floor. You do not need a brace (a joint support), a splint or a special pillow between your legs; an ordinary pillow is enough for sleeping on your side. For the first few days to few weeks, someone should also help you with household tasks.
Pain and swelling: In the first days, pain, swelling and bruising at the side of the hip and thigh are to be expected, and they gradually ease. But pain that is not controlled by your medicines, or new or increasing swelling of the calf or the whole leg, is not normal; in these cases, call the clinic the same day.
⚠️ Warning signs: when should you call urgently?
Call the clinic the same day: Spreading redness, warmth or swelling around the wound; Thick, smelly or persistent discharge; Wound edge opening; Repeatedly wet dressing; Fever of 38.5°C or above, or chills; Pain not controlled by medicines; New or increasing pain, tightness or swelling in the calf or whole leg; Lower-leg or foot numbness or tingling lasting over a week, or new; New weakness lifting the front of the foot; Any fall or blow to the hip; Feeling the joint shift and slip back; Red urine, unexplained bruising, gum or nose bleeding that stops; No bowel movement for 3 days.
Seek emergency help: Shortness of breath; Chest pain; A very fast heartbeat; Coughing up blood; Pain and swelling of the calf or the whole leg together with shortness of breath or chest pain; Bleeding that does not stop with pressure, vomiting blood, or black stools; Fainting; Toes or the sole of the foot that turn cold, pale or blue (not bruised skin on the thigh and calf after surgery); Progressive weakness or numbness; Severe sleepiness or slow breathing after an opioid pain medicine or alprazolam; Hives or swelling of the face after taking a medicine; A fall after which you cannot stand on your feet; A blow to the head, with or without a fall, or a new, severe headache during the 5 weeks you take aspirin or apixaban; Signs of a dislocated joint: sudden, severe pain in the hip or groin together with the leg looking shorter or longer, the toes staying turned outwards or inwards, being unable to put weight on the leg or move it, or a sound of the joint shifting. If you have signs of a dislocation, stay where you are, do not walk and do not let anyone try to put the leg back in place; until help arrives and on the way to hospital, keep the leg supported with pillows just as it is. In Iran, call emergency medical services on 115 or go to the nearest hospital emergency department.
If your symptom is on neither list, first read its section in this guide; limping and a leg that feels longer are in the FAQs. If still worried, act today: call Dr Jalil Emad’s clinic on 09137825207, or book an appointment online. In an emergency, do not wait for the clinic to reply; follow the instructions in the emergency box above.
1Care in the first days after surgery
In the first few days, the hip is not expected to be free of pain and swelling; the aim is for pain and swelling to stay under control, for the wound to stay clean and dry, for you to walk with the walker several times every day, and for you to follow the movement precautions. The sections below tell you what to do and what to expect in the first days.
🩹 Wound care and dressing changes
The wound is on the outer side of the hip and thigh and is closing under the waterproof dressing; it is best left untouched until your first visit, and your only task is to keep it clean and dry. Looking at the wound or changing the dressing may feel a little worrying, but there is no need to rush into doing anything.
More detailLess detail
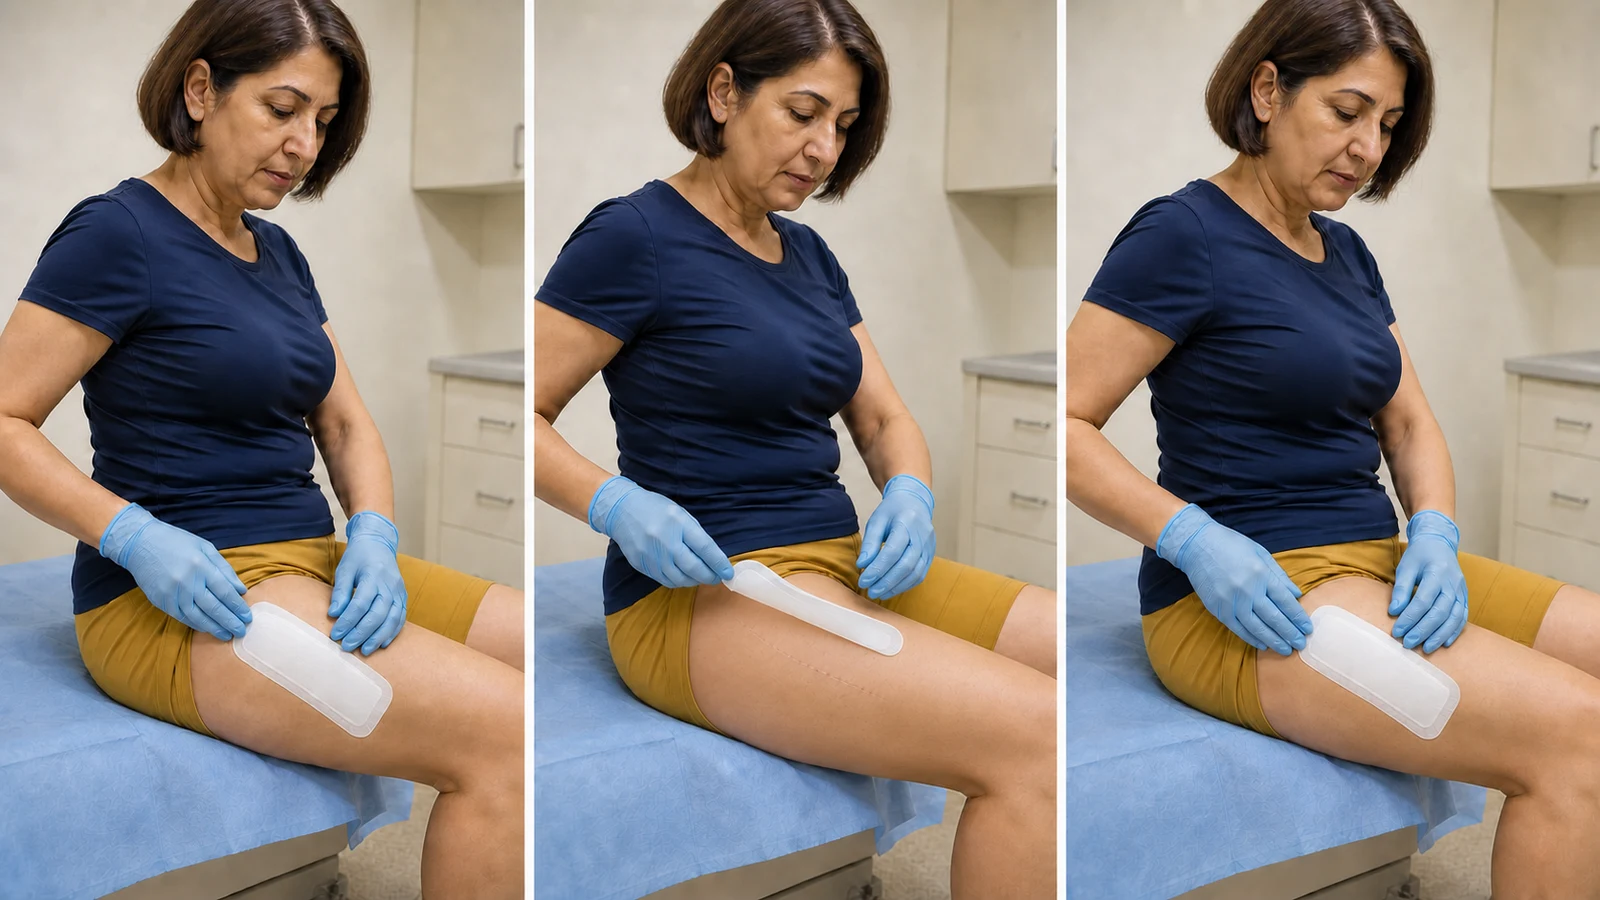
- Do not open the waterproof dressing before your first visit, which is 10 to 14 days after surgery; it is changed at that visit, in the clinic. Only if it becomes wet, dirty, loose or soaked with blood before then, change it at home that same day for a new waterproof dressing. If the dressing gets wet several times, whether with blood or wound discharge or with water, call the clinic the same day.
- Before changing it, wash your hands with soap and water and get everything ready on a clean surface beside the bed: a new waterproof dressing, sterile gauze, sterile saline, a rubbish bag and a pair of sterile gloves. In Dr Emad’s programme, get sterile gloves together with the dressing pack.
- Peel the old dressing off gently, starting from one corner and working along the length of the thigh; do not pull it off in one go, and put it in the bag. Then wash your hands again and put on sterile gloves. Stitches, staples, the adhesive strips on the wound and scabs should stay in place. Stitches or staples are removed at the clinic about two weeks (14 days) after surgery.
- If the wound needs cleaning, wipe a sterile gauze moistened with sterile saline once from one end of the wound to the other, and dry it the same way with a dry gauze. Apart from sterile saline, do not put anything on the incision line, such as alcohol, Betadine, ointment, cream or powder.
- Place the new dressing over the same incision line without touching its inner surface, and press the adhesive edges down gently. The dressing should cover the whole incision line, should not pull on the skin and should not be wrapped around the thigh.
- Bruising at the side of the hip and thigh and slight redness of the skin beside the wound are normal in the first days and fade on their own. If you see spreading redness or warmth, thick or foul-smelling discharge, or the wound edge opening, follow the warning-signs section.
🚿 Showering with a waterproof dressing
The key points when showering are that water must not get under the dressing, the wound must not be rubbed, and you must not fall in the bathroom.
More detailLess detail
- From 48 hours after surgery you may take a short shower, provided the wound is dry and the waterproof dressing is intact and fully stuck down.
- Do not aim a strong jet of water directly at the dressing, and do not rub a washcloth or soap over it. After the shower, dry around the dressing by patting gently with a towel.
- For the first few showers, sit on a shower chair and do not be alone. A grab rail on the wall and a non-slip mat also help to stop you falling in the bathroom; under the shower, do not pivot on the operated leg either.
- If water gets under the dressing or its corners lift, change it that same day for a new waterproof dressing; the method is described in the wound care section above.
💊 Medicines and supplements
Your prescription may not include all of these medicines. Read the amount of each medicine from your own prescription, and if you are unsure, ask your doctor or pharmacist.
More detailLess detail
- Cephalexin: This antibiotic prevents infection at the surgical site, and in Dr Emad’s programme it is taken for 7 days. If hives, swelling of the face or shortness of breath appear, stop the medicine and call emergency services right away.
- Aspirin or apixaban: To prevent blood clots in the leg veins, Dr Emad prescribes one of these two, depending on your risk of clots, for 5 weeks (35 days). After hip replacement, this period is not shortened. If you walk little or have had a clot in the past, apixaban is usually prescribed. Take the medicine at a fixed time and do not stop it on your own, because stopping early raises the risk of a clot. The most important side effect of these medicines is bleeding; its signs, and what to do for each one, are set out in the warning-signs section. If you hit your head while taking aspirin or apixaban, even without a fall, or you get a new, severe headache, act as set out in the “Seek emergency help” box in the warning-signs section.
- Famotidine or pantoprazole: One of these two medicines is prescribed to protect the stomach from pain relievers and aspirin. Take it as prescribed.
- Gabapentin: In Dr Emad’s programme, gabapentin is sometimes prescribed alongside pain relievers to reduce pain after surgery. Do not stop this medicine suddenly: in the last week of the prescription, reduce the daily amount little by little over about a week until you stop.
- Acetaminophen with codeine: This tablet contains codeine, which is an opioid pain medicine; take it only when you are in pain. While you are taking this tablet, do not take any other medicine that contains acetaminophen, such as a cold tablet or cold powder.
- Oxycodone: Take this opioid pain medicine only if it is on your prescription and you need it; it is usually not needed for more than a few days. If you do need it, take it instead of one dose of acetaminophen with codeine, at least 6 hours after your last acetaminophen with codeine tablet; at each dose, take only one of these two medicines. On days when you take this medicine, do not take alprazolam and do not drink alcohol.
- Alprazolam: This calming medicine is prescribed only in the first days, when needed. On days when you take oxycodone, do not take alprazolam, because together these two medicines may slow your breathing dangerously. Codeine is also an opioid, and taking it with alprazolam can carry the same risk. Do not combine them on your own; if both are on your prescription, check with the clinic or a pharmacist before taking them together.
- Laxative: Opioid pain medicines may cause constipation. Have more water, fruit and vegetables, keep walking, and if needed, take a simple laxative. If you have not had a bowel movement for 3 days, call the clinic the same day.
- Anti-inflammatory medicines, such as ibuprofen, Gelofen and naproxen: Do not take these medicines without checking with the clinic, because alongside aspirin or apixaban they raise the risk of bleeding. In Dr Emad’s programme, no separate medicine is prescribed to prevent extra bone forming in the muscles around the joint (heterotopic ossification); this is explained in the frequently asked questions.
- Collagen: Collagen is a food supplement, not a medicine. In Dr Emad’s programme 10 g of collagen a day is recommended for 3 months after surgery; take it alongside doing your exercises, not instead of them.
- Vitamin D: Vitamin D helps the body absorb calcium, and the body needs calcium to build bone. In the same programme, 1000 to 2000 units a day are taken for 3 months; do not take more than this, because large amounts may raise the calcium level in your blood.
- Vitamin C: The body needs vitamin C to make collagen and to heal wounds. In the same programme, 1000 milligrams of vitamin C a day are taken for 6 weeks.
- While you are taking alprazolam, gabapentin or an opioid pain medicine, do not drive and do not drink alcohol. Keep opioid pain medicines out of children’s reach, and do not add any new medicine, supplement or herbal medicine without asking your doctor or pharmacist. If severe sleepiness or slow breathing occurs, the people with you must act at once as set out in the “Seek emergency help” box in the warning-signs section.
🧊 Controlling pain and swelling
To control pain and swelling, put a cold pack on the side of the hip and thigh for 15 to 20 minutes at a time, with a thin cloth between your skin and the pack; raise your leg a little on a pillow when you rest; and take several short walks during the day. In the first weeks, the swelling at the side of the hip and thigh may be considerable, and mild to moderate swelling may last 3 to 6 months. The overall trend should be towards improvement; if your muscles ache after exercise, do less exercise, but do not give it up.
More detailLess detail
- In the first days and after exercise, put a cold pack on the side of the hip and thigh for 15 to 20 minutes at a time, 3 to 4 times a day. Cold eases pain in the first days. Keep a thin cloth between your skin and the pack, never let a session go beyond 20 minutes, and do not leave the cold pack on your skin while you sleep.
- After each session, check the colour and feeling of your skin. Cold dulls the feeling in the skin; if the skin turns very white, or you notice numbness that does not go away or a burning pain, remove the pack and do not put it back until the skin is back to normal.
- When resting, place the calf and heel of the operated leg on a pillow so that the leg is a little raised.
- In the first days, if you need pain medicine for exercise, take it about 30 minutes before exercise or physiotherapy. This helps to control pain during exercise.
- Do not stay on complete bed rest, and take several short walks during the day. Long periods without moving make the operated leg swell more.
- New or sudden swelling, especially together with calf pain, is not part of this process; in that case, follow the warning-signs section.
🚶 Walking, the walker, the cane and stairs
You walk with a walker from the day of surgery or the day after, and put weight on the operated leg as far as pain allows. In Dr Emad’s programme a walker is needed for about 2 to 4 weeks, and after that a cane, until you walk without a limp; you usually reach this point around the sixth week after surgery.
More detailLess detail
- Walk several short times during the day, a little more each day. The amount and method for each walk are on the “Walking with a walker” exercise card.
- Move the walker a little forward, then bring the operated leg forward, and then the non-operated leg. Keep your steps short and your toes pointing forward; to turn, take several small steps.
- Start using the cane instead of the walker when you can stand and walk for more than 10 minutes without leaning your weight on the walker. Hold the cane in the hand opposite the operated leg; for example, if your right hip was operated on, hold the cane in your left hand.
- Set the cane aside when you walk without a limp and without your pelvis dropping to one side. What counts is the quality of your walking, not just reaching a date.
- On stairs, lead with the non-operated leg going up and with the operated leg coming down, and put both feet on the same step each time. The walker stays at the bottom or top of the stairs, and you go up and down with the handrail and one cane: hold the handrail with one hand and the cane with the other, whichever side the handrail is on. In the first days, have someone beside you. Normal stair climbing, that is, one foot per step, starts once you walk without the cane and without a limp, which is usually around the sixth week; even then, hold the handrail.
- Make your home safe for walking: remove small slippery rugs and cables from your path and keep the way well lit. Keep the things you often need within reach so that you do not have to bend down or stretch for them, and do not carry anything in your hands while walking. A fall in the first weeks may damage your new hip.
🫀 Preventing blood clots
Blood clots in the veins of the pelvis and leg are among the most common complications of hip replacement, and they become dangerous if they reach the lungs. In one study, despite preventive medicine, about 1 in 100 people developed a clot with symptoms in the first 3 months. Prevention has four parts; keep up all four until the end of their set period.
More detailLess detail
- Blood thinner (aspirin or apixaban): take it for 5 weeks (35 days), at a fixed time, without stopping it on your own.
- Compression stockings: in Dr Emad’s programme, wear them during the day for 4 to 6 weeks and take them off at night. The stockings must not wrinkle; check the colour and feeling of your toes every day.
- Moving your foot up and down at the ankle (ankle pumps): do this regularly during your waking hours; the amount is on the card for this exercise.
- Short, frequent walks: do not forget them. Do not sit for more than 45 minutes at a stretch; after 45 minutes, get up and walk a few steps.
- Know the signs of a blood clot: new or increasing pain, tightness or swelling of the calf or the whole leg, especially on one side. If a clot reaches the lung, sudden shortness of breath or sudden chest pain may also appear. What to do for each sign is set out in the warning-signs section.
⚠️ Movement precautions for the first 6 weeks
After surgery through the side of the hip, dislocation of the joint is rare. Even so, in the first 6 weeks, while the tissues and muscles at the side of the hip are healing, follow the four rules below, and do not do exercises that move the leg out to the side either. Sitting on an ordinary chair, bending to get dressed and tying your shoelaces are all allowed for you.
More detailLess detail
- Do not cross your legs, either when sitting or when lying down.
- Do not pivot on the operated leg. To change direction, take several short steps so that your whole body turns together.
- Do not take the operated leg backwards while its toes are turned outwards. Do not take long steps. When one leg is in front and the other is behind, do not lower your body. When walking or getting up, do not push off with your toes turned outwards either. In exercises where the leg goes backwards, the movement is short and the toes stay pointing forward.
- Do not bend your hip very deeply while your knee turns inwards; for example, do not squat, and do not pick anything up from the floor while sitting on a low chair.
- Until the end of the sixth week (day 42), do not do any exercise in which you move the operated leg out to the side using your own muscle strength or against a band or weight. The muscles at the side of the hip, which were opened and repaired during the operation, become firm during this time. Moving the leg to the side to get onto and off the bed, and for walking and stairs, is allowed. Exercises for these muscles start on day 43 (the start of the seventh week) and are on the cards for the second and third months.
- After 6 weeks, you gradually set the first four rules aside, and the limits on everyday movements are lifted. When you can drive, play sport and sit on the floor is set out in the “Driving, work, prayer and daily activities” section.
🛏️ Sleeping, sitting and getting dressed
In the first 6 weeks, sleeping, sitting and getting dressed must also fit in with the movement precautions. An ordinary pillow and a sturdy chair with armrests are all you need for this, provided that you sleep in a bed until the end of the third month, not on a mattress laid on the floor.
More detailLess detail
- Until the end of the third month, sleep in a bed, not on a mattress laid on the floor; use a chair for sitting.
- From the first night, sleep on your back or on your non-operated side. Whenever you lie on your side, put an ordinary pillow between your knees and lower legs so that the operated leg does not cross the midline of your body or rotate; this pillow is needed for 6 weeks. When you can sleep on your operated side is covered in the frequently asked questions.
- Sit on a sturdy, ordinary-height chair with armrests, so that your knees are roughly level with your hips. A soft, very low sofa that is hard to get up from is not suitable in these weeks.
- To sit down and get up, place the operated leg slightly further forward and push on the chair’s armrests with your hands; take hold of the walker after you have stood up.
- Get dressed and put on your socks sitting down. Put the operated leg into your trousers first, and when taking them off, take it out last. Bending to put on socks and tie shoelaces is allowed; if it is painful in the first days, a long-handled shoehorn helps. You do not need a sock aid or a reacher.
- Wear loose clothing so that elastic or seams do not rub on the wound at the side of your thigh.
🛡️ The first two weeks
In the first two weeks, the aims are to walk safely with the walker, to get the thigh and buttock muscles working again and to keep the hip moving. Start the exercises in this section on the day of surgery or the day after. In total, exercise for 30 to 60 minutes a day, spread over several sessions.
In the first 6 weeks, follow the four special precautions for this operation in all your exercises: do not cross your legs, do not pivot on the operated leg, do not take the operated leg backwards with the toes turned outwards, and avoid bending very deeply while the knee turns inwards. Until the end of the sixth week (day 42), no exercise for moving the operated leg out to the side is done either; moving the leg to the side to get onto and off the bed is allowed.
1) Walking with a walker (Walker Gait)
With the walker, you practise stepping safely from the day of surgery or the day after, and from the start you put weight on the operated leg as far as pain allows. In the first days, walk for 5 to 10 minutes, 3 to 4 times a day. If you feel dizzy, your leg gives way, you feel a sharp pain in the hip or groin, or you get shortness of breath or chest pain, do not carry on. Sit down on the nearest chair or the edge of the bed, not on the floor. If there is no chair nearby, stay standing where you are, hold the walker’s handgrips firmly and call someone to bring you a chair. For shortness of breath or chest pain, follow the warning-signs section.
More detailLess detail
Before you start: Walking both rebuilds the strength of your leg and is part of preventing blood clots. In Dr Emad’s programme, whether the implant is cemented or uncemented, you can put as much weight on the operated leg as you can tolerate from the day of surgery or the day after. Wear closed, non-slip shoes, and remove small rugs and cables from your path. While you are using the walker, put a chair along your walking route and do not walk alone. Stand upright inside the walker frame with both hands on the handgrips.
How to do it:
- Move the walker one short step forward and make sure all four of its legs are on the ground.
- Step the operated leg forward inside the walker frame so that the heel touches the ground first.
- Pressing down on the handgrips, take part of your weight through the walker and bring the non-operated leg up beside the operated leg.
- Start the next step again by moving the walker forward.
Movement tips: Keep your steps short, and do not let either foot go past the front bar of the walker. Keep the toes of the operated leg pointing forward, and to change direction, take several small steps rather than pivoting on the operated leg. Repeat the order “walker, operated leg, non-operated leg” slowly and at an even rhythm, and look ahead, not at your feet. The sign that you are doing it correctly is that your trunk is upright and both hands are on the handgrips. Mild tiredness is normal; sit down and rest between sessions.
Amount, repetitions and progression: In the first days, walk for 5 to 10 minutes, 3 to 4 times a day, and as your leg gets stronger, build up to 20 to 30 minutes, 2 to 3 times a day. Once you have stood and walked with the walker for more than 10 minutes without leaning your weight on it, it is time for the cane.
Stop immediately if: you feel dizzy, your leg gives way, you feel a sharp pain in the hip or groin, or you get shortness of breath or chest pain; sit down on the nearest chair or the edge of the bed, not on the floor. If there is no chair nearby, stay standing where you are, hold the walker’s handgrips firmly and call someone. For shortness of breath or chest pain, follow the warning-signs section.
Common mistakes: Taking long steps, moving a foot past the front bar of the walker, hanging on your arms, pivoting on the operated leg and looking at your feet.
Easier version: Shorten the route, and have someone walk beside you for the first few sessions.

2) Ankle pumps
Moving the ankle up and down makes the calf muscles work and improves blood flow in the leg. Do 3 sets of 10 repetitions, pausing for 3 seconds at each end of the movement. If you develop new or increasing calf pain, tightness or swelling, especially in one leg, or shortness of breath, stop and follow the warning-signs section.
More detailLess detail
Before you start: This movement helps blood circulation in the leg and is part of preventing blood clots. From the day of surgery, lie on your back or sit leaning back, with your legs straight and your toes pointing to the ceiling. Loosen the bedsheet from around your ankles; no equipment is needed.
How to do it:
- Keep your thigh and knee still so that only the ankle works.
- Slowly pull your toes towards you, as if you were taking your foot off the accelerator pedal, and pause.
- Point your toes away from you, as if you were pressing the accelerator pedal, and pause again.
- Repeat this back-and-forth movement at an even rhythm.
Movement tips: You can move both ankles together. Do not push extra at the end of the movement, and do not hold your breath. The sign that you are doing it correctly is that your thigh and knee stay still and only the ankle and toes move. A feeling of tightness in the calf muscles at the end of the movement is normal and eases after a few moments of rest.
Amount, repetitions and progression: Do 3 sets of 10 repetitions, pausing for 3 seconds at each end of the movement. In the first days, whenever you are lying down or sitting, repeat this movement a few times every 5 to 10 minutes; also do it during long periods of sitting and when travelling.
Stop immediately if: you develop new or increasing calf pain, tightness or swelling, especially in one leg, or shortness of breath; follow the warning-signs section.
Common mistakes: Fast, jerky movement, rotating the whole leg instead of moving the ankle, and holding your breath.
Easier version: Make the movement smaller; even a short ankle movement is better than staying still.
3) Tightening the front thigh muscle (Quadriceps Sets)
Tightening the front thigh muscle without moving the leg makes this muscle active again. Do 3 sets of 10 repetitions, holding each contraction for 5 seconds. If you feel a sharp pain in the hip or knee instead of the muscle tightening, stop.
More detailLess detail
Before you start: The front thigh muscle becomes weak after surgery, and you need it for standing and walking. From the day of surgery, lie on your back on the bed with the operated leg straight and your toes pointing to the ceiling. Also place a small rolled-up towel under the knee.
How to do it:
- Tighten the front thigh muscle and gently press the back of the knee down into the towel.
- Hold the contraction and breathe calmly.
- Relax the muscle completely and rest for a few moments.
- Tighten again; the heel stays on the bed.
Movement tips: The leg hardly moves; only the muscle tightens, and the kneecap moves up slightly. Do not hold your breath, and rest for 5 seconds between repetitions. The sign that you are doing it correctly is that the front thigh muscle stands out and the back of the knee moves closer to the towel. Thigh tiredness is normal.
Amount, repetitions and progression: Do 3 sets of 10 repetitions, holding each contraction for 5 seconds. Once the muscle tightens easily and firmly, hold each contraction for up to 10 seconds.
Stop immediately if: you feel a sharp pain in the hip or knee instead of the muscle tightening.
Common mistakes: Lifting the heel or the buttocks, tightening the non-operated leg instead of the operated one, and holding your breath.
Easier version: Hold the contraction for a shorter time, and start with fewer repetitions.
4) Tightening the buttock muscles (Gluteal Sets)
Squeezing the buttock muscles together makes these muscles active again and improves blood flow in the leg. Do 3 sets of 10 repetitions, holding each contraction for 5 seconds. If you feel a sharp pain at the wound or at the side of the hip, stop.
More detailLess detail
Before you start: When you stand and walk, the buttock muscles keep your pelvis level, and this exercise also helps your circulation. From the day of surgery, lie on your back on the bed (not on a mattress on the floor) with both legs straight; no equipment is needed.
How to do it:
- Gently squeeze your buttock muscles together without lifting your buttocks off the bed.
- Hold the contraction and breathe calmly.
- Relax the muscles slowly and rest for a few moments.
Movement tips: Your legs do not move in this exercise. Do not hold your breath; you can count out loud while you hold. The sign that you are doing it correctly is that your buttocks tighten but your pelvis and legs stay where they are. Muscle tiredness is normal.
Amount, repetitions and progression: Do 3 sets of 10 repetitions, holding each contraction for 5 seconds; 3 to 4 sessions a day are enough.
Stop immediately if: you feel a sharp pain at the wound or at the side of the hip.
Common mistakes: Lifting your buttocks off the bed, holding your breath, and tightening your stomach instead of your buttocks.
Easier version: Make the contraction gentler and shorter.
5) Heel slides
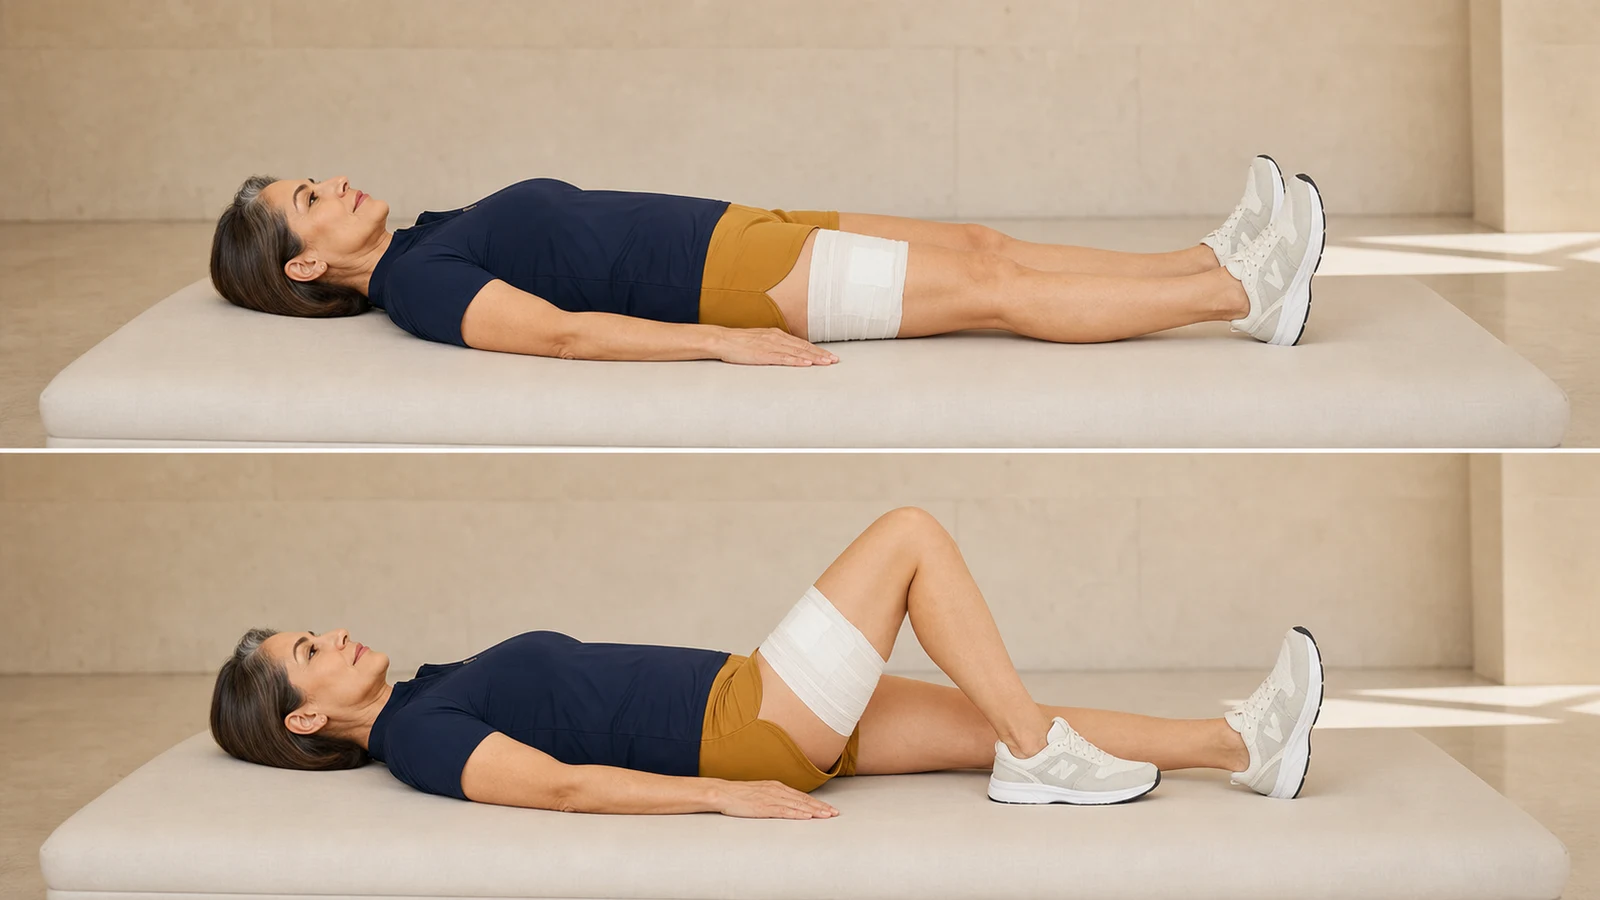
By sliding your heel along the bed, you gently bend the hip and knee to keep the joint moving. Do 3 sets of 10 repetitions, pausing for 5 seconds at the deepest bend. If you feel a sharp pain in the hip or groin instead of a stretch, stop.
More detailLess detail
Before you start: This exercise keeps the bend in your hip and knee that you need for sitting down, getting up and getting dressed. From the first days, lie on your back on the bed (not on a mattress on the floor) with a pillow under your head and both legs straight; keep your arms by your sides with your palms on the bed.
How to do it:
- Slide the heel of the operated leg along the bed towards your buttock so that the hip and knee bend.
- Pause at the deepest bend at which you still feel only a stretch.
- Slowly slide the heel forward until the leg is fully straight again.
- Repeat the movement; the knee stays pointing to the ceiling throughout.
Movement tips: The heel does not lift off the bed, and the other leg stays straight. Keep the knee pointing to the ceiling, and do not let it fall inwards. Breathe out as you bend, do each back-and-forth movement slowly, and rest for 5 seconds between repetitions. The sign that you are doing it correctly is that the heel slides along a straight line and your pelvis does not lift off the bed. A mild stretch at the front of the thigh or knee is normal.
Amount, repetitions and progression: Do 3 sets of 10 repetitions, pausing for 5 seconds at the deepest bend. Each day, if it is comfortable, bend a little further; if the exercise causes pain, reduce the range and go back to a pain-free amount.
Stop immediately if: you feel a sharp pain in the hip or groin instead of a stretch.
Common mistakes: Lifting the heel off the bed, letting the knee fall inwards, lifting the pelvis and jerky movement.
Easier version: Make the range smaller, and slide the heel only halfway.
6) Going up and down stairs with the handrail and cane (Stairs with Rail and Cane)
The rule for stairs is: up with the non-operated leg and down with the operated leg; put both feet on the same step each time. You practise two or three steps before discharge, and at home you use the stairs as much as you need to each day. If you feel dizzy, your leg gives way or you lose your balance, hold the handrail firmly, sit down on the step you are on and do not carry on.
More detailLess detail
Before you start: Going up and down stairs safely is something you need for life at home. From the first days you use the stairs with the handrail and one cane, with someone beside you, and the walker stays at the bottom or top of the stairs. Hold the handrail with one hand and the cane with the other, whichever side the handrail is on. The steps should be no higher than the usual height, that is, about 18 centimetres.
How to do it:
- To go up, stand close to the first step, hold the handrail firmly and put the non-operated leg on the step above.
- Push up with the non-operated leg, with help from the handrail, and bring the operated leg and the cane up onto the same step.
- To come down, first put the cane on the step below, and then slowly lower the operated leg.
- With help from the handrail and the cane, put the non-operated leg beside the operated leg on the same step.
Movement tips: As long as you use the stairs with a cane, follow the rule “up with the non-operated leg, down with the operated leg”. Go one step at a time, keep your trunk upright and do not rush. On the stairs, do not pivot on the operated leg. The sign that you are doing it correctly is that one hand is always on the handrail and the cane is in the other, and both feet are on the same step before you move to the next one.
Amount, repetitions and progression: No fixed number of repetitions is set for stairs; use them as much as you need each day, and until your leg’s strength has come back, have someone with you. Once you walk without the cane and without a limp, usually around the sixth week, you can hold the handrail and put the other foot on the next step each time.
Stop immediately if: you feel dizzy, your leg gives way or you lose your balance; hold the handrail firmly, sit down on the step you are on and do not carry on.
Common mistakes: Going up with the operated leg first, coming down with the non-operated leg first, letting go of the handrail, taking two steps at once and pivoting on the step.
Easier version: Go up and down one step only, with someone standing beside you.

↔️ The second two weeks
The aims of the second two weeks are longer walks, moving from the walker to the cane and starting the standing exercises; your stitches were removed at about day 14. Continue the exercises from the first two weeks and add the exercises in this section; the daily exercise time stays at 30 to 60 minutes. The stationary bike is added from the start of the fourth week, at about day 22.
By the end of these two weeks, the cane has usually taken the place of the walker; hold the cane in the hand opposite the operated leg. The precautions for the first 6 weeks and the ban on exercises that move the leg out to the side still apply; in exercises in which you take the leg backwards, keep the movement short and the toes pointing forward.
7) Sitting down and standing up from a chair with armrests (Sit to Stand)
With this exercise, you practise getting up from a chair safely, and your thigh and buttock muscles get stronger. Start with 5 to 10 repetitions and gradually build up to 10 to 20 repetitions, 3 times a day. If your leg gives way, you feel dizzy or you get a sharp pain in the hip, sit down and do not carry on.
More detailLess detail
Before you start: Getting up from a chair is one of the things you do most often in a day. Use the safe way of getting up every time you stand up from the first day, and start repeating it as an exercise from the third week. Choose a sturdy chair without wheels, with two armrests and of ordinary height, so that your knees are level with your hips when you sit, and place the walker in front of you. Move to the front edge of the chair; the soles of both feet should be on the floor, with the operated leg slightly further forward than the non-operated leg.
How to do it:
- Lean your trunk slightly forward from the hips.
- Push down on the armrests of the chair with your hands and stand up on both legs.
- Stand fully upright, find your balance, and then put your hands on the walker’s handgrips one at a time.
- To sit down, step back until you feel the edge of the chair against the back of your legs, take hold of the armrests one at a time and sit down slowly.
Movement tips: Leaning your trunk forward is necessary for getting up and is allowed; just do not let the knee of the operated leg turn inwards, and keep your knees apart. Breathe out as you stand up, and sit down slowly rather than dropping onto the chair. Do not pull on the walker to get up; the walker is for standing. The sign that you are doing it correctly is that both legs take your weight and your hands go to the walker only after you are fully upright. Tiredness in the thighs and buttocks is normal.
Amount, repetitions and progression: Start with 5 to 10 repetitions, and once it is easy, build up to 10 to 20 repetitions, 3 times a day. Once the movement is smooth and both legs are working equally, rely less on your hands.
Stop immediately if: your leg gives way, you feel dizzy or you get a sharp pain in the hip; sit down.
Common mistakes: Pulling on the walker to get up, dropping onto the chair, using a chair that is too low and getting up with the non-operated leg only.
Easier version: Put a firm cushion on the chair so that the seat is a little higher.

8) Raising the knee while standing (Standing Hip Flexion)
Standing up, you lift the knee of the operated leg a little so that the muscles at the front of the hip get stronger. Repeat 10 times, holding the leg up for 2 to 3 seconds each time; do this 3 to 4 times a day. If you lose your balance or feel a sharp pain in the groin or hip, stop.
More detailLess detail
Before you start: This exercise strengthens the muscles that bring the leg forward when you walk and climb stairs. Start from the third week, once standing with one hand on a support is safe. Stand beside a kitchen counter or another fixed support, with the counter on the side of your non-operated leg; put the hand on that side on the counter and let the other hand hang free by your side.
How to do it:
- Stand up straight and shift your weight onto the non-operated leg.
- Slowly bring the knee of the operated leg forward and up, only as far as the knee stays below your waist.
- Hold the leg up for 2 to 3 seconds.
- Slowly lower the leg until the sole of the foot is back on the floor.
Movement tips: The knee never goes higher than your waist; a small lift is enough, and the thigh stays below horizontal. Keep your trunk upright and do not lean back. Breathe calmly, do not swing the leg, and put the foot down for a few moments between repetitions. The sign that you are doing it correctly is that the non-operated foot stays firmly on the floor and your pelvis stays level. Tiredness at the front of the thigh and hip is normal.
Amount, repetitions and progression: Repeat 10 times, holding the leg up for 2 to 3 seconds each time; do this 3 to 4 times a day. Progress means lifting the leg slowly without swinging it while your trunk stays upright, not lifting the knee higher.
Stop immediately if: you lose your balance or feel a sharp pain in the groin or hip.
Common mistakes: Lifting the knee higher than your waist, leaning your trunk back, swinging the leg and letting go of the support.
Easier version: Lift the knee less, and put your other hand on the counter as well, reaching across the front of your body without turning your trunk.

9) Marching while lying on your back (Supine Marching)
Lying on your back with your knees bent, you lift each sole a few centimetres off the bed in turn so that your stomach muscles and the muscles at the front of the hip work together. Repeat 20 times, and do this at least 2 times a day. If you feel a sharp pain in the groin or lower back, stop.
More detailLess detail
Before you start: This exercise uses the stomach muscles to keep the pelvis and lower back steady and gently activates the muscles at the front of the hip. Start in the second two weeks, once you can do heel slides comfortably. Lie on your back on the bed, bend both knees so that the soles of your feet are on the bed, and put your arms by your sides with your palms on the bed.
How to do it:
- Gently tighten your stomach muscles without stopping your breathing.
- Slowly lift the sole of the operated leg a few centimetres off the bed; the knee stays bent.
- Hold for a moment and slowly lower the foot.
- Do the same with the other leg, and carry on taking turns.
Movement tips: The foot comes up only a few centimetres, and the knee does not come towards your chest. Your pelvis and lower back stay still throughout, and the pelvis does not roll to one side. Breathe calmly and move slowly. The sign that you are doing it correctly is that only a small gap shows under the raised sole and the other foot stays flat on the bed. Tightening of the stomach muscles is normal.
Amount, repetitions and progression: Repeat 20 times, taking turns with each leg, and do this at least 2 times a day. Progress means keeping your pelvis completely still, not lifting the foot higher.
Stop immediately if: you feel a sharp pain in the groin or lower back.
Common mistakes: Bringing the knee up towards the chest, rolling the pelvis, arching the lower back and holding your breath.
Easier version: Lift the foot less, or only lift the heel off the bed.
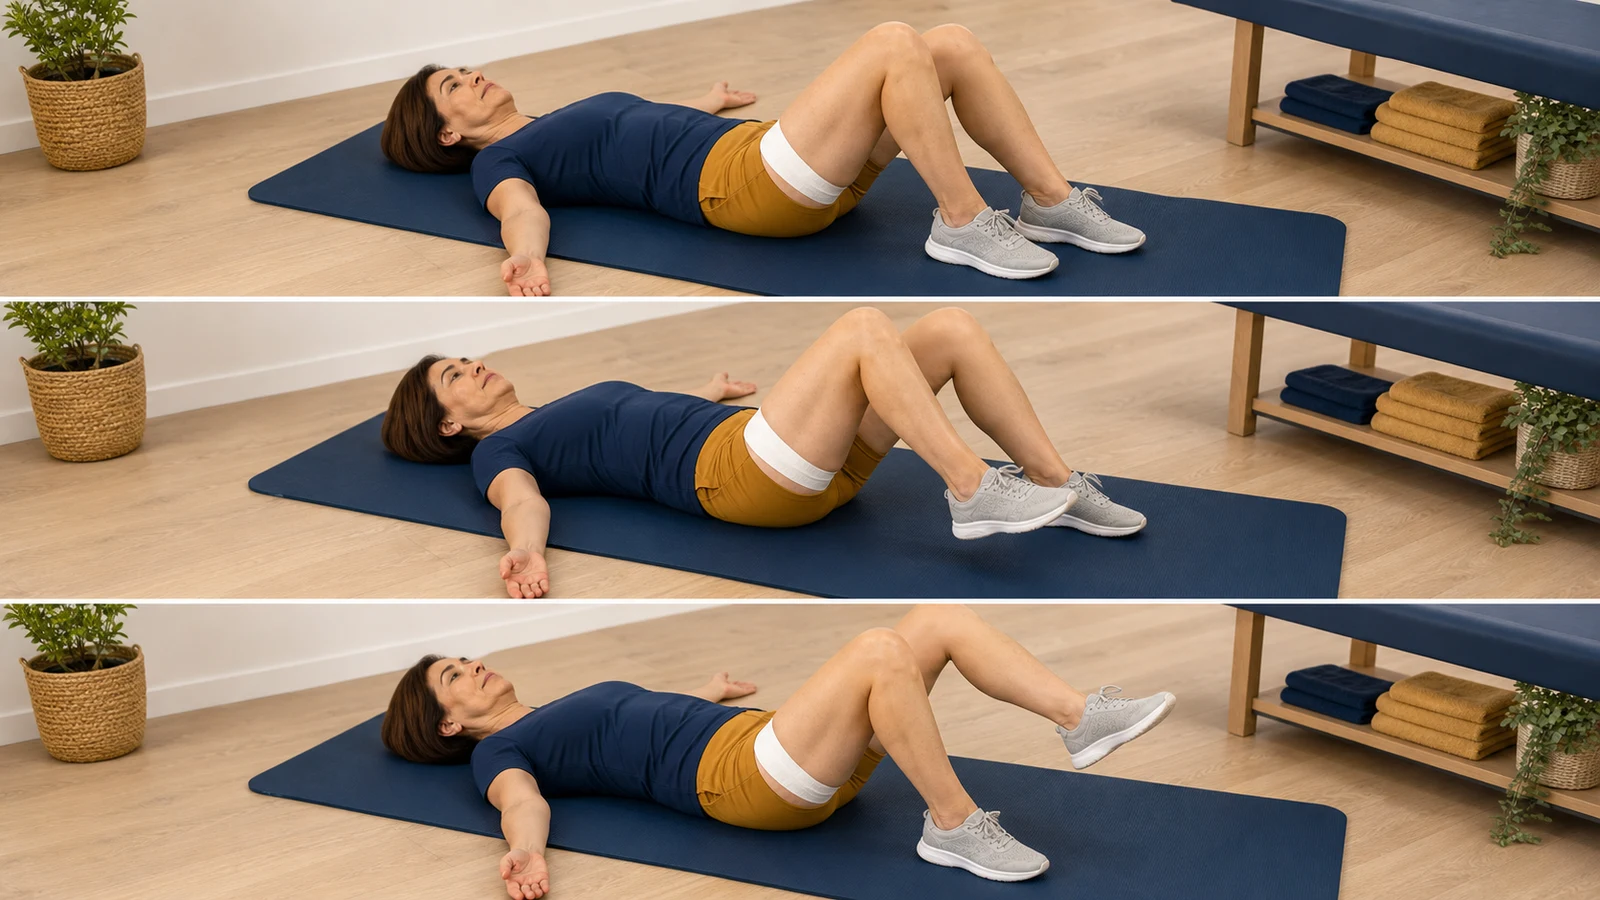
10) Taking the leg back while standing (Standing Hip Extension)
Standing up, you take the operated leg slightly backwards with the toes pointing forward so that the buttock muscles get stronger. Repeat 10 times, holding for 2 to 3 seconds each time; do this 3 to 4 times a day. If you feel a sharp pain at the front of the hip or in the groin, or you lose your balance, stop.
More detailLess detail
Before you start: When you walk, the buttock muscles take the leg backwards and keep the pelvis level. Start from the third week, once standing with support is safe. Stand facing a kitchen counter or another fixed support, put both hands on it and place your feet hip-width apart, with the toes of both feet pointing forward.
How to do it:
- Shift your weight onto the non-operated leg and keep your trunk upright.
- Slowly take the operated leg slightly backwards, with the knee straight and the toes pointing forward.
- Hold the leg there for 2 to 3 seconds.
- Slowly bring the leg back until the sole of the foot is on the floor again beside the non-operated foot.
Movement tips: The movement is short: the leg goes only slightly behind your body, only as far as you can go without your lower back arching or your trunk leaning forward. Keep the toes of the operated leg pointing forward throughout, and do not let them turn outwards; taking the leg backwards with the toes turned outwards is the very movement to avoid in the first 6 weeks. Breathe calmly, and put the foot down for a few moments between repetitions. The sign that you are doing it correctly is that your pelvis stays level and square to the counter. Tightening of the buttock is normal.
Amount, repetitions and progression: Repeat 10 times, holding for 2 to 3 seconds each time; do this 3 to 4 times a day. Progress means a slow movement with the toes pointing forward and the lower back not arching, not taking the leg further back.
Stop immediately if: you feel a sharp pain at the front of the hip or in the groin, or you lose your balance.
Common mistakes: Turning the toes outwards, taking the leg too far back, arching the lower back and leaning the trunk forward.
Easier version: Take the leg back less far, or only tighten your buttock muscles.

11) Stationary bike
Pedalling on a stationary bike improves the movement of your hip and the strength of your leg. From the start of the fourth week, begin with 5 minutes of pedalling without resistance, once a day. If you get groin pain, chest pain or shortness of breath, or your pelvis twists on the saddle, stop there and get off slowly; for chest pain or shortness of breath, follow the warning-signs section.
More detailLess detail
Before you start: Cycling is an exercise without impact that builds up the strength and endurance of the leg together. In Dr Emad’s programme, the stationary bike starts at the beginning of the fourth week, at about day 22. Use only an upright bike, not a recumbent bike with a backrest. Set the saddle high enough that, when the pedal is at its highest point, your knee does not come higher than your hip, and set the resistance to the lowest level.
How to do it:
- Get on with the help of the handlebars, put both hands on the handlebars and slide your shoes into the pedal straps.
- If a full turn is hard at the start, first pedal backwards for a few turns.
- Once a full turn is comfortable, pedal forwards slowly with your trunk upright.
- At the end, slow down and get off slowly, using the handlebars for support.
Movement tips: Even at the highest point of the pedal stroke, the knee of the operated leg stays lower than the hip; if it comes higher, raise the saddle. Keep your pelvis still on the saddle, and do not let it twist to one side to complete the turn. Breathe calmly and steadily. The sign that you are doing it correctly is that your trunk is upright, both hands are on the handlebars and the knee moves up and down in line with your toes. Mild thigh tiredness is normal.
Amount, repetitions and progression: At the start, pedal for 5 minutes, once a day, without resistance. Each time it becomes easy, add 5 minutes, and increase the resistance slightly only when you can pedal comfortably for 20 minutes at the current resistance.
Stop immediately if: you get groin pain, chest pain or shortness of breath, or your pelvis twists on the saddle; get off slowly, and for chest pain or shortness of breath follow the warning-signs section.
Common mistakes: A low saddle that brings the knee higher than the hip, a recumbent bike, too much resistance at the start, and your pelvis shifting on the saddle.
Easier version: Pedal only a few turns backwards and forwards, and shorten the time.

🌱 The second month: days 31 to 60
The aims of the second month are walking without a limp, setting the cane aside and strengthening the buttock and thigh muscles and the muscles at the side of the hip.
From day 43, that is, the start of the seventh week, the low step-up, lifting your hips off the bed (the bridge), taking the leg back while lying on your front, balancing on one leg with both hands on a support, and two exercises that move the leg out to the side are added. Once these two exercises are pain-free, moving the top knee away from the bottom knee while lying on your side (the clamshell) is added as well.
The special hip precautions continue until the end of the sixth week, and after that the limits on everyday movements are gradually lifted. Keep exercising for 30 to 60 minutes a day; you can do different groups of exercises in different sessions or on different days. Set the cane aside when you walk without a limp and without your pelvis dropping to one side; most patients reach this point around the sixth week. If you still limp after that, read the question “How long is it normal to limp after surgery?” in the frequently asked questions.
12) Low step-up
You put the operated leg on a low step and step up with that same leg so that the thigh and buttock muscles get stronger for stairs. Start from day 43; do 3 sets of 10 repetitions, staying on the step for 5 seconds each time. If your leg gives way, your knee falls inwards or you feel a sharp pain in the hip, stop.
More detailLess detail
Before you start: This exercise strengthens the muscles you need for going up stairs. Unlike the “up with the non-operated leg” rule given for the stairs at home, here you deliberately put the operated leg on the step first so that this same leg gets stronger. In Dr Emad’s programme, this exercise starts on day 43 (the start of the seventh week), at the same time as balancing on one leg and the exercises that move the leg out to the side. Stand in front of a low step about 10 centimetres high, with a handrail or fixed support on the side of the operated leg, and put the hand on that side on it.
How to do it:
- Place the whole sole of the operated foot on the step.
- Shift your weight onto this leg and step up until the non-operated leg reaches the step beside it, without pushing yourself up with the non-operated leg.
- Stand upright on the step.
- Slowly bring the non-operated leg back down to the floor, controlling the way down with the leg on the step.
Movement tips: The knee on the step stays in line with your toes and does not fall inwards; your pelvis stays level and does not drop towards the non-operated side. Breathe calmly and come down slowly. The sign that you are doing it correctly is that the operated leg goes onto the step first and lifts your body up. Feeling your buttock and thigh muscles working is normal.
Amount, repetitions and progression: Do 3 sets of 10 repetitions, staying on the step for 5 seconds each time. Once it is easy, gradually increase the height of the step, from about 10 centimetres up to about 30 centimetres.
Stop immediately if: your leg gives way, your knee falls inwards or you feel a sharp pain in the hip.
Common mistakes: Pushing off with the back leg, putting only half of the sole on the step, letting the pelvis drop to one side and letting go of the handrail.
Easier version: Use a lower step, and hold the handrail more firmly.

13) Rising onto the toes with support (Heel Raises)
This exercise strengthens the calf muscles and helps your balance and the push that moves your body forward with each step. Do 3 sets of 10 repetitions, staying on your toes for 5 seconds each time. If you lose your balance, or a calf cramp does not go away even after a few moments of rest, stop. For a calf cramp that does not go away with rest, follow the warning-signs section.
More detailLess detail
Before you start: When you walk and climb stairs, the calf muscles push the body forward with each step. Start in the second month, once you can stand with light support and put your weight evenly on both legs. Stand at a kitchen counter or a fixed handrail, not behind a light chair; keep your feet shoulder-width apart and your toes pointing forward.
How to do it:
- Put both hands on the support and spread your weight over both feet.
- Slowly lift both heels off the floor by the same amount.
- Stay up on your toes.
- Lower your heels slowly to the floor.
Movement tips: Keep your body upright without swaying forwards and backwards; your weight should be equal on both feet. Breathe out as you rise, come down slowly, and rest for 5 seconds between repetitions. The sign that you are doing it correctly is that both heels rise together and by the same amount. Calf tiredness is normal.
Amount, repetitions and progression: Do 3 sets of 10 repetitions, staying on your toes for 5 seconds each time. From the seventh week, once you are stronger, you can do the same exercise on one leg with both hands on the support, taking turns with each leg.
Stop immediately if: you lose your balance, or a calf cramp does not go away even after a few moments of rest; for a calf cramp that does not go away with rest, follow the warning-signs section.
Common mistakes: Leaning on a light chair, putting your weight on the non-operated leg only, and dropping down suddenly.
Easier version: Do not lift your heels as high, and hold on firmly to the support with both hands.
14) Bridge (Double-Leg Bridge)
Lifting your buttocks off the bed strengthens the buttock muscles and the back of the thigh. From the seventh week, do 3 sets of 10 repetitions, staying up for 5 seconds each time. If you get a sharp pain in your lower back or hip, or a cramp in the back of your thigh, stop.
More detailLess detail
Before you start: The buttock muscles keep your pelvis level when you get up, climb stairs and walk. Start from the seventh week. Lie on your back on the bed (not on a mattress or mat on the floor), with both knees bent, your feet flat on the bed hip-width apart, and your arms by your sides, palms on the bed.
How to do it:
- Tighten your stomach and buttock muscles.
- Slowly lift your buttocks until your shoulders, hips and knees form an almost straight line.
- Stay up in this position.
- Slowly lower your buttocks.
Movement tips: Lift your buttocks only until your shoulders, hips and knees form a straight line, no higher; do not arch your lower back. Keep your weight equal on both feet, and do not let your knees drift apart or come together. Breathe calmly, and rest for 5 seconds between repetitions. The sign that you are doing it correctly is that your pelvis rises straight and level and both soles stay on the bed. Tightening of the buttocks is normal.
Amount, repetitions and progression: Do 3 sets of 10 repetitions, staying up for 5 seconds each time. Once it is easy, put a small pillow between your knees and squeeze it gently as you lift your buttocks.
Stop immediately if: you get a sharp pain in your lower back or hip, or a cramp in the back of your thigh.
Common mistakes: Arching the lower back, lifting the buttocks beyond a straight line, letting one side of the pelvis drop and jerking up.
Easier version: Do not lift your buttocks as high, and stay up for a shorter time.

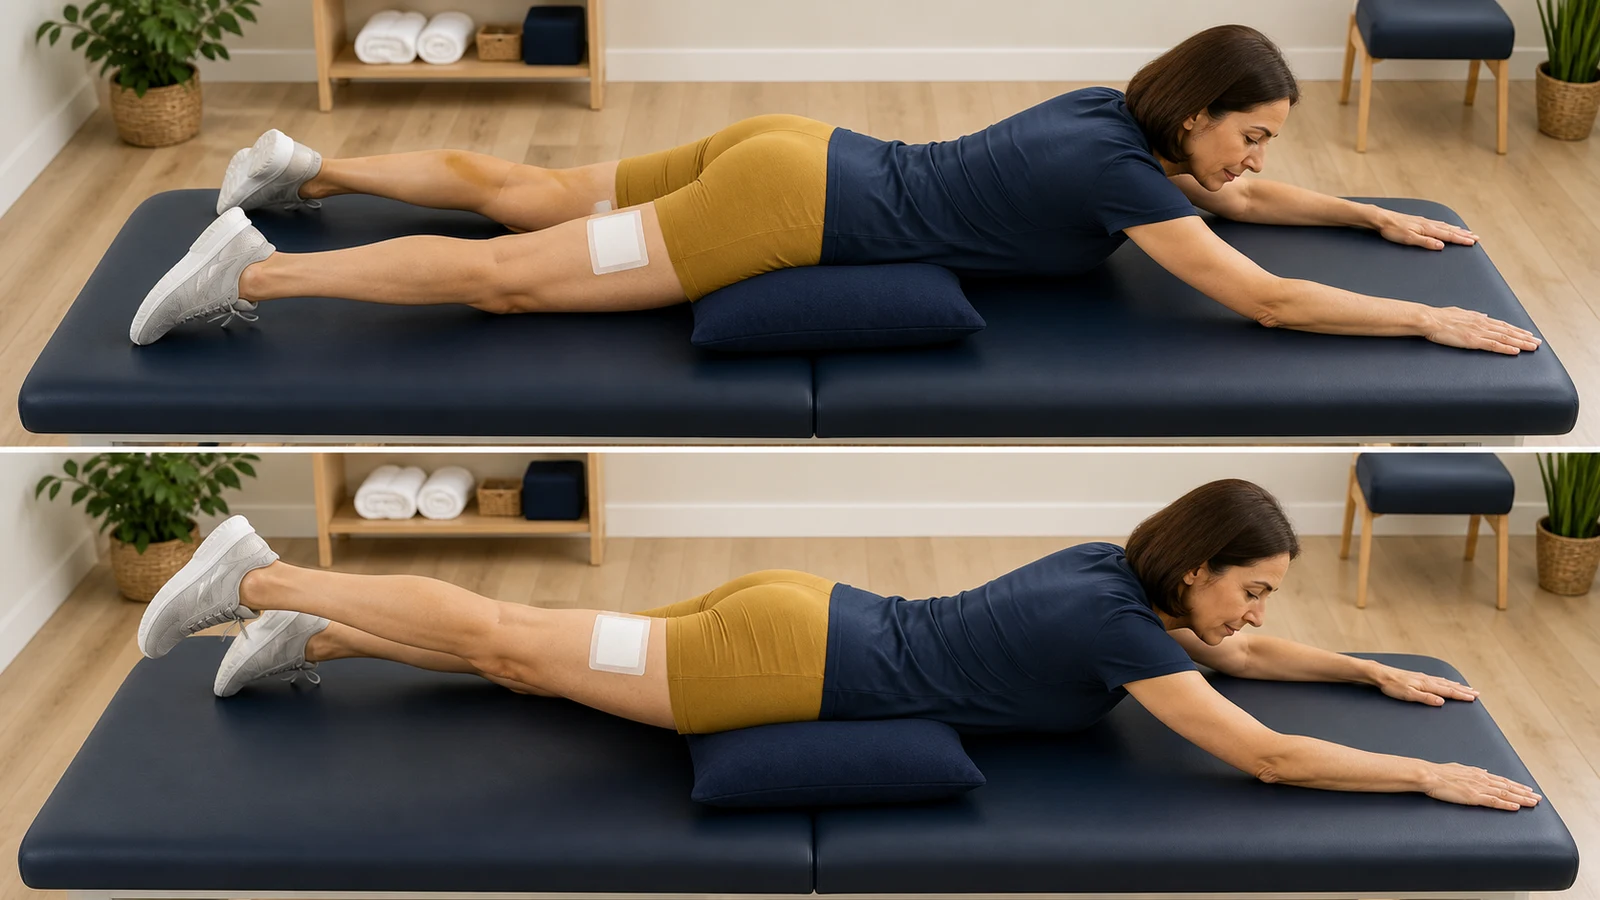
15) Taking the leg back while lying on your front (Prone Hip Extension)
Lying on your front, you lift the operated leg a little with the knee straight so that the buttock muscles get stronger. From the seventh week, repeat 5 to 10 times. If you feel a sharp pain at the front of the hip, in the groin or in your lower back, stop.
More detailLess detail
Before you start: This exercise strengthens the buttock muscles in the position where the leg is behind the body, as at the end of each step. Start from the seventh week; sleeping on your front is also allowed from this time. Lie on your front on a firm bed, put a thin pillow under your pelvis and rest your arms on the bed above your head; both legs lie straight on the bed.
How to do it:
- Tighten your buttock muscles and press your pelvis into the pillow.
- Slowly lift the operated leg a little with the knee straight; your toes keep pointing down to the bed.
- Hold for a moment.
- Slowly lower the leg back onto the bed and relax the muscles.
Movement tips: The leg lifts only as far as your pelvis can stay on the pillow without your lower back arching. Keep the leg in line with your body, and do not let it turn outwards. Breathe calmly, and rest for 5 seconds between repetitions. The sign that you are doing it correctly is that only the operated leg lifts, while your pelvis and the other leg stay on the bed. Tightening of the buttock is normal.
Amount, repetitions and progression: Repeat 5 to 10 times; start with 5, and once you can do them without pain and with your pelvis still, build up to 10. Do not lift the leg higher.
Stop immediately if: you feel a sharp pain at the front of the hip, in the groin or in your lower back.
Common mistakes: Lifting the leg so high that your pelvis comes off the pillow, arching the lower back, turning the leg outwards and bending the knee.
Easier version: Do not lift the leg as high, or only tighten your buttock muscles.
16) Balancing on one leg with support (Supported Single-Leg Balance)
With both hands on the counter, you stand on the operated leg and lift the other leg slightly so that your balance comes back and the muscles at the side of the hip get stronger. From the seventh week, start with 5 to 10 seconds and gradually build up to 30 seconds. If you lose your balance or feel dizzy, put your foot down and do not carry on.
More detailLess detail
Before you start: Standing on one leg brings back your balance and makes the muscles at the side of the hip work to keep your pelvis level. In Dr Emad’s programme, this exercise is done from the seventh week, and only with both hands on a support. Stand beside a kitchen counter or a fixed handrail, put both hands on it and wear closed shoes.
How to do it:
- Place your feet hip-width apart and slowly shift your weight onto the operated leg.
- Lift the non-operated foot a few centimetres off the floor, right beside where it was standing.
- Stay in this position; keep your pelvis level and both hands on the counter.
- Slowly put the foot down, rest for a few moments and repeat.
Movement tips: The lifted leg must not cross behind the operated leg or past the midline of your body, and it comes up only a little. Do not let your pelvis drop towards the lifted leg, and do not lean your trunk towards the standing leg. Breathe calmly and look ahead. The sign that you are doing it correctly is that your pelvis stays level and your body sways less. Do the exercise on the non-operated leg too.
Amount, repetitions and progression: Start by standing for 5 to 10 seconds and repeat 5 to 10 times. Each time it becomes easy, stand for longer until you reach 30 seconds.
Stop immediately if: you lose your balance or feel dizzy; hold the counter firmly, put your foot down and do not carry on.
Common mistakes: Crossing the lifted leg behind the other leg, letting the pelvis drop to one side, letting go with one hand and standing far from the counter.
Easier version: Just take the weight off the non-operated foot, without lifting it fully off the floor.

17) Moving the leg out to the side while standing (Standing Hip Abduction)
With both hands on the counter, you move the operated leg out to the side with the knee straight so that the muscles at the side of the hip get stronger. Start from day 43; do 3 sets of 10 repetitions, holding for 5 seconds each time. If you feel a sharp pain at the side of the hip or at the wound, stop.
More detailLess detail
Before you start: This exercise strengthens the muscles at the side of the hip, the same muscles that were opened and then repaired during this operation. In Dr Emad’s programme, no exercise for moving the leg out to the side is done until the end of the sixth week (day 42), and this exercise starts on day 43 (the start of the seventh week). Stand side-on to the kitchen counter, with the counter on the side of your non-operated leg and your body facing forward, not towards the counter. Put the hand on that side on the counter, and reach the other hand across the front of your body to the counter without turning your trunk; place your feet hip-width apart with your toes pointing forward.
How to do it:
- Shift your weight onto the non-operated leg and keep its knee slightly bent.
- Slowly move the operated leg out to the side, with the knee straight and the toes pointing forward.
- Hold at the end of the movement for 5 seconds.
- Slowly bring the leg back until it is on the floor beside the other foot.
Movement tips: Move the leg out to the side only as far as you can without your trunk tilting or your pelvis hitching up. Keep your toes pointing forward, and do not let the leg drift backwards or turn outwards. Breathe calmly, and rest for 5 seconds between repetitions. The sign that you are doing it correctly is that your trunk stays almost upright, both hands are on the counter and the leg moves straight out to the side. Tightening of the muscles at the side of the hip is normal.
Amount, repetitions and progression: Do 3 sets of 10 repetitions, holding at the end of the movement for 5 seconds each time. Once this exercise and the side-lying version are pain-free, add the clamshell as well.
Stop immediately if: you feel a sharp pain at the side of the hip or at the wound.
Common mistakes: Turning the toes outwards, tilting the trunk, hitching up the pelvis and swinging the leg.
Easier version: Move the leg less far out to the side, and hold it for a shorter time.

18) Moving the leg out to the side while lying on your side (Side-Lying Hip Abduction)
Lying on your non-operated side, you lift the operated leg a little towards the ceiling with the knee straight; this form of the exercise is harder than the standing version. Start from day 43; do 3 sets of 10 repetitions, holding for 5 seconds each time. If you feel a sharp pain at the side of the hip or at the wound, stop.
More detailLess detail
Before you start: This exercise strengthens the muscles at the side of the hip against the weight of the leg itself. In Dr Emad’s programme, this exercise too starts on day 43 (the start of the seventh week), at the same time as moving the leg out to the side while standing; if you find it hard, do only the standing version for now. Lie on your non-operated side on a firm bed, put a thin pillow under your head and bend the knee of the lower leg slightly; the operated leg is on top, straight and in line with your body.
How to do it:
- Keep the toes of the top leg pointing forward and straighten the knee.
- Slowly lift the leg a little towards the ceiling, without your pelvis rolling forwards or backwards.
- Hold at the top of the movement for 5 seconds.
- Slowly lower the leg until it rests on the lower leg.
Movement tips: The leg stays in line with your body or slightly in front of it, and never goes behind your body. Keep the toes pointing forward, not turned up towards the ceiling. Lift the leg only as far as your two hips stay exactly one above the other, with your pelvis rolling neither forwards nor backwards. Breathe calmly, and rest for 5 seconds between repetitions. The sign that you are doing it correctly is that your pelvis stays still and the leg rises straight up towards the ceiling. Tightening of the muscles at the side of the hip is normal.
Amount, repetitions and progression: Do 3 sets of 10 repetitions, holding for 5 seconds each time. If you cannot do 10 repetitions with your pelvis still, start with fewer and gradually build up to 10.
Stop immediately if: you feel a sharp pain at the side of the hip or at the wound.
Common mistakes: Taking the leg behind the body, turning the toes up towards the ceiling, rolling the pelvis forwards or backwards and swinging the leg.
Easier version: Lift the leg less, or for now do only the standing version.

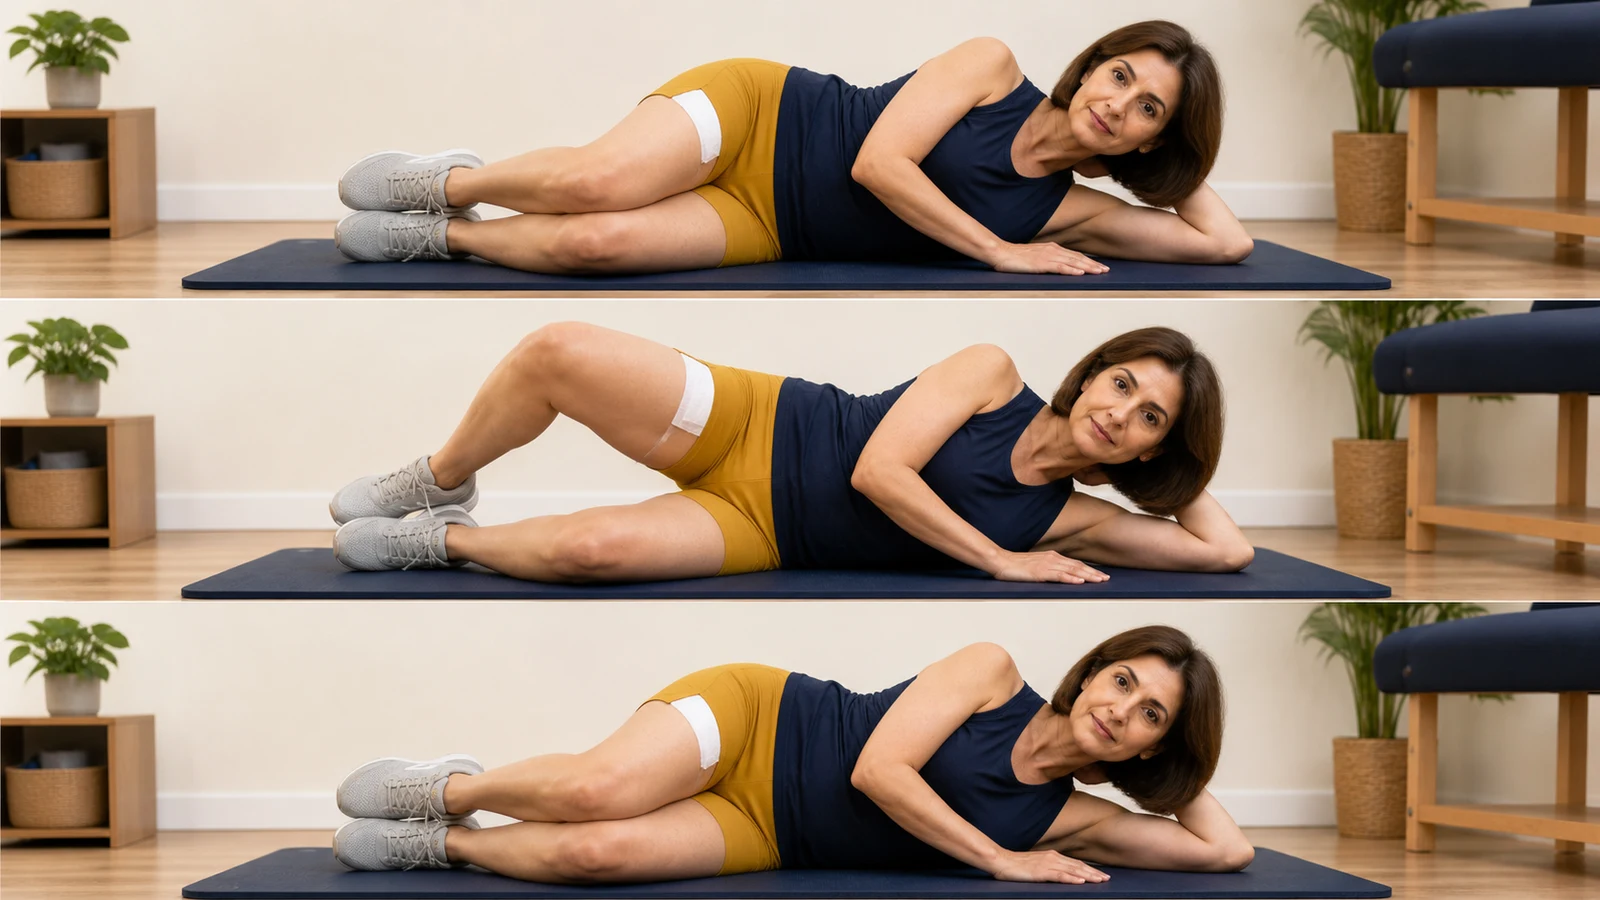
19) Clamshell
Lying on your non-operated side with your heels together, you move the top knee away from the bottom knee so that the muscles at the side of the hip get stronger. Start once the two exercises that move the leg out to the side are pain-free, and repeat 5 to 10 times. If you feel a sharp pain at the side of the hip or in the groin, stop.
More detailLess detail
Before you start: The clamshell strengthens the muscles at the side of the hip with the hip bent. Start it once moving the leg out to the side while standing and while lying on your side has become pain-free; this may already be in the second month. Lie on your non-operated side on the bed with a pillow under your head; bend your hips and knees, with your knees one on top of the other and your heels together. Put the hand on your operated side on the bed in front of your trunk.
How to do it:
- Keep your heels together.
- Slowly move the top knee away from the bottom knee and up towards the ceiling, without your heels separating.
- Hold for a moment.
- Slowly bring the knee back down onto the other knee.
Movement tips: Lift the top knee only as far as your pelvis does not roll backwards; your trunk stays still throughout. Your heels and the shin of the bottom leg do not move. Breathe calmly, and rest for 5 seconds between repetitions. The sign that you are doing it correctly is that your heels stay together throughout and your two hips stay one above the other. Tightening of the muscles at the side of the hip and in the buttock is normal.
Amount, repetitions and progression: Repeat 5 to 10 times; start with 5, and once you can do them without pain and with your pelvis still, build up to 10.
Stop immediately if: you feel a sharp pain at the side of the hip or in the groin.
Common mistakes: Separating the heels, rolling the pelvis backwards, lifting the knee too high and moving fast.
Easier version: Do not lift the top knee as high.
🏋️ The third month: days 61 to 90
In the third month, the exercises become harder so that the hip gets strong enough for stairs, sitting down and getting up, and longer walks. Two exercises with a band, sideways walking with a band and moving the leg out to the side with a band, are added; a controlled step-down and bending a little as if you were about to sit on a chair (a shallow squat) also come into the programme.
Start each new exercise with a small number of repetitions. If an exercise causes pain, reduce its range or number of repetitions, and if the pain persists, set that exercise aside for now. Low-impact sport becomes possible after the third month, from day 91; its conditions and examples are in the “Sport” item of the “Driving, work, prayer and daily activities” section.
20) Sideways walking with a band (Lateral Band Walk)
With a light band just above your knees, you take short steps sideways so that the muscles at the side of the hip get stronger for walking. Take 5 steps to one side and 5 steps to the other side, and repeat this 3 times. If you feel a sharp pain at the side of the hip or lose your balance, stop.
More detailLess detail
Before you start: This exercise works the muscles at the side of the hip in a movement similar to walking. Start in the third month, once moving the leg out to the side while standing and the clamshell have become pain-free. Put a light loop band just above both knees, not around your ankles. Stand close to the kitchen counter with your back to it, and rest the hand on your non-operated side on its edge, beside your body; keep your toes pointing forward and your knees slightly bent. With each sideways step, slide that hand along the edge of the counter with you so that you do not lose your support.
How to do it:
- Place your feet hip-width apart so that the band is slightly stretched.
- Take a short step to the side with the operated leg.
- Slowly bring the other leg closer, only until your feet are hip-width apart, without letting them touch.
- Take 5 steps to one side along the counter, then come back 5 steps the other way.
Movement tips: Keep your trunk upright, and do not let it sway from side to side. Keep your toes pointing forward and your knees in line with your toes. Keep the steps short and slow, and never let your feet touch or cross. Breathe calmly, and stand still for a few moments between rounds. The sign that you are doing it correctly is that the band stays slightly stretched the whole way and your hand is on the counter. Tiredness at the side of the hip is normal.
Amount, repetitions and progression: Take 5 steps to one side and 5 steps to the other side, and repeat this 3 times. Start with a light band; once this amount is easy, without pain and without your trunk swaying, use a slightly firmer band.
Stop immediately if: you feel a sharp pain at the side of the hip or lose your balance.
Common mistakes: Tying the band around the ankles, bringing the feet together, taking long steps and swaying the trunk.
Easier version: Start without a band, or with a looser band and shorter steps.

21) Moving the leg out to the side with a band (Banded Standing Hip Abduction)
With a loop band above your knees, you move the operated leg out to the side while standing so that the muscles at the side of the hip get stronger. Do 3 sets of 10 repetitions, holding for 5 seconds each time. If you feel a sharp pain at the side of the hip or in the groin, stop.
More detailLess detail
Before you start: After surgery through the side of the hip, the strength of the muscles at the side of the hip keeps improving for up to about 6 months, and this exercise makes those same muscles stronger against the resistance of a band. Start in the third month, once moving the leg out to the side while standing without a band is easy for you. Stand side-on to the counter, with the counter on the side of your non-operated leg and your body facing forward, not towards the counter. Put the hand on that side on the counter, and reach the other hand across the front of your body to the counter without turning your trunk; tie a light loop band around both legs, just above the knees.
How to do it:
- Shift your weight onto the non-operated leg.
- Slowly move the operated leg out to the side, with the knee straight and the toes pointing forward, until the band is stretched.
- Hold at the end of the movement for 5 seconds.
- Slowly bring the leg back, without letting the band pull it inwards.
Movement tips: The leg moves straight out to the side, not backwards, and the toes keep pointing forward. Keep your trunk upright, and do not lean it towards the counter. Breathe calmly, bring the leg back more slowly than you move it out, and rest for 5 seconds between repetitions. The sign that you are doing it correctly is that your pelvis stays level and the band stays under control on the way back as well. Tiredness at the side of the hip is normal.
Amount, repetitions and progression: Do 3 sets of 10 repetitions, holding for 5 seconds each time; continue this 2 to 3 days a week. Once it is easy, use a firmer band.
Stop immediately if: you feel a sharp pain at the side of the hip or in the groin.
Common mistakes: Turning the toes outwards, taking the leg backwards, tilting the trunk and letting the band snap back suddenly.
Easier version: Do it without a band, or move the leg less far out to the side.
22) Controlled step-down
You stand on a low step on the operated leg and slowly lower the other leg to the floor, so that you regain control of the hip and knee for coming down stairs. Start with one short set and build up to 2 to 3 sets of 15 to 20 repetitions, 3 to 5 times a week. If your leg gives way, your knee falls inwards or you feel a sharp pain in the hip, stop.
More detailLess detail
Before you start: When you come down stairs, the hip and thigh muscles have to lower your body weight slowly and with control. This strengthening exercise deliberately differs from the rule for the stairs at home: here the operated leg stays on the step so that this same leg gets stronger. As long as you use the stairs with a cane, keep following the “down with the operated leg” rule when you come down the stairs at home. Start in the third month, once stepping up onto a low step has become easy. Stand on a low step, about 10 centimetres high, beside a handrail, and put the hand on the operated side on the handrail; the whole sole of the operated foot should be on the step, and the non-operated leg should stay in the air in front of the edge of the step.
How to do it:
- Hold the handrail and move your weight fully onto the operated leg.
- Slowly bend the knee of the leg on the step until the heel of the non-operated leg comes close to the floor in front of the step.
- Touch the floor with the heel only, and do not put any weight on it.
- Straighten the knee of the leg on the step and slowly come back up.
Movement tips: Keep the knee of the leg on the step in line with your toes, and do not let it fall inwards; keep your pelvis level, and do not let it drop towards the non-operated side. Go down more slowly than you come up, and breathe calmly. The sign that you are doing it correctly is that the knee of the leg on the step clearly bends and the heel of the non-operated leg only touches the floor. Feeling your buttock and front thigh muscles working is normal.
Amount, repetitions and progression: Start with one short set and gradually build up to 2 to 3 sets of 15 to 20 repetitions, 3 to 5 times a week. Once you can do it without pain and with your knee and pelvis staying aligned, gradually increase the height of the step.
Stop immediately if: your leg gives way, your knee falls inwards or you feel a sharp pain in the hip.
Common mistakes: Dropping down suddenly, putting weight on the lowered leg, letting the knee fall inwards and letting go of the handrail.
Easier version: Do not go down as far, and use a lower step.

23) Shallow squat with a chair behind you
With a sturdy chair behind you, you bend a little as if you were about to sit down, and then stand up straight again, so that your thighs and buttocks get stronger. Do 3 sets of 10 repetitions, pausing for 5 seconds each time. If your leg gives way, your knee falls inwards or you feel a sharp pain in the hip, sit down on the chair and do not carry on.
More detailLess detail
Before you start: This exercise builds up the strength you need for sitting down and getting up. Start in the third month, and only once you can get up from a chair and sit down comfortably without help from your hands. Place a sturdy chair without wheels behind you so that you can sit on it if you get tired; keep your feet shoulder-width apart, the soles of your feet on the floor and your hands free.
How to do it:
- Stretch your arms out in front of you to help your balance.
- Take your buttocks slightly back, towards the chair, and slowly bend your knees.
- Pause for 5 seconds in the shallow bend, while your buttocks are still clearly above the level of your knees.
- Push through both feet and slowly stand up straight.
Movement tips: The bend is shallow: your buttocks do not reach the chair, and your heels stay on the floor. Keep your knees in line with your toes; do not let them fall inwards or go further forward than the tips of your toes, and keep your weight equal on both feet. Breathe in as you go down, breathe out as you come up, and rest for 5 seconds between repetitions. The sign that you are doing it correctly is that your trunk comes slightly forward and your hands hold nothing. Tiredness in the thighs and buttocks is normal.
Amount, repetitions and progression: Do 3 sets of 10 repetitions, pausing for 5 seconds each time. Once you can do it without pain and with your knees in line, bend a little deeper, but keep your buttocks above the chair.
Stop immediately if: your leg gives way, your knee falls inwards or you feel a sharp pain in the hip; sit down on the chair.
Common mistakes: Going down deeply, lifting the heels, letting the knees fall inwards and shifting your weight onto the non-operated leg.
Easier version: Bend less, and put one hand on the counter or on a handrail beside you.

🎯 After 90 days: a maintenance programme and returning to activity
After the third month, the aims are to keep your muscles strong and to return to your usual activities. Continue the exercises 2 to 3 days a week so that your muscles stay strong. At this stage, once the two-leg bridge is easy and pain-free, the single-leg bridge is also added to the programme. To choose a sport, see the “Sport” item in the “Driving, work, prayer and daily activities” section.
24) Gradually increasing your walking (Walking Progression)
Build up your walking little by little: first on flat ground, then on uneven ground and uphill. Regular walks of 20 to 30 minutes, 3 to 4 times a week, help you keep your strength. If you develop a new limp, a sharp pain in the hip, chest pain or shortness of breath, stop. For a new limp, let the clinic know; for chest pain or shortness of breath, follow the warning-signs section.
More detailLess detail
Before you start: Regular walking, especially on different surfaces, brings back endurance and balance. Start a regular programme after the third month, once you walk without a cane and without a limp. Wear comfortable shoes with non-slip soles, and choose a flat, familiar route at first.
How to do it:
- Warm up with a few minutes of slow walking.
- Walk at a comfortable pace; your heel touches the ground first, then the sole of your foot, and finally your toes.
- Take steps of equal length and keep your trunk upright.
- At the end, walk more slowly for a few minutes.
Movement tips: Your walking should be even and free of a limp; if a limp that had gone comes back, or comes with new pain at the side of the hip, shorten that day’s walk and let the clinic know. Once a flat route is comfortable, add uneven ground, uphill and downhill. Breathe calmly and steadily, and stop to rest whenever you need to. The sign that you are doing it correctly is that your steps are even on both sides, your pelvis does not drop to one side and your trunk is upright. Mild tiredness in the legs after walking is normal.
Amount, repetitions and progression: Start with the length of time you can now walk comfortably, and each time it becomes easy, add 5 minutes. To keep your strength, continue walking for 20 to 30 minutes, 3 to 4 times a week. If walking makes your hip pain worse, shorten the next session.
Stop immediately if: you develop a new limp, a sharp pain in the hip, chest pain or shortness of breath; stand still or sit down, let the clinic know about a new limp, and for chest pain or shortness of breath follow the warning-signs section.
Common mistakes: Suddenly increasing the distance, starting with uphill walking and carrying on while limping.
Easier version: Shorten the route, or walk in two shorter sessions.
25) Stationary bike for endurance
After the third month, you continue the stationary bike for endurance and slowly build up to 20 to 30 minutes, 3 to 4 times a week. If you get groin or hip pain, chest pain or shortness of breath, get off slowly; for chest pain or shortness of breath, follow the warning-signs section.
More detailLess detail
Before you start: Cycling keeps your muscles strong and your hip flexible without putting impact on the joint. Start this programme after the third month, once 20 minutes of pedalling at low resistance is easy for you. Use the same upright bike with a high saddle, set so that your knee is almost straight when the pedal is at its lowest point.
How to do it:
- Pedal slowly with low resistance to warm up.
- Carry on at a steady, comfortable pace.
- Pedal backwards for part of the time so that other muscles work too.
- At the end, pedal more slowly for a few minutes and get off slowly.
Movement tips: Increase the resistance only when you can pedal comfortably for 20 minutes at the current resistance. Keep your pelvis steady on the saddle, and let your knee move up and down in line with your toes. Breathe calmly and steadily. The sign that you are doing it correctly is that your trunk is upright and your pelvis does not shift on the saddle. Mild thigh tiredness is normal.
Amount, repetitions and progression: Increase the time slowly until you reach 20 to 30 minutes, 3 to 4 times a week. If pedalling makes your hip pain worse, reduce the time and the resistance of the next session.
Stop immediately if: you get groin or hip pain, chest pain or shortness of breath; get off slowly, and for chest pain or shortness of breath follow the warning-signs section.
Common mistakes: Too much resistance, pedalling fast, and your pelvis shifting on the saddle to complete the turn.
Easier version: Shorten the time and reduce the resistance.
26) Balancing on one leg with less support (Single-Leg Balance Progression)
You continue the one-leg balance exercise with lighter support so that your balance in everyday activities comes back. Stand for 30 seconds each time and gradually build up to 1 to 2 minutes. If you lose your balance or feel dizzy, hold the counter and do not carry on.
More detailLess detail
Before you start: Balance training is an essential part of full recovery, and after the third month it continues with less support. Start once standing on each leg for 30 seconds with both hands on the counter is easy for you. Wear closed shoes and stand beside a counter or a fixed handrail so that you can hold it at any moment.
How to do it:
- Stand on the operated leg and lift the other leg slightly off the floor.
- Instead of both hands, rest only the fingertips of one hand on the counter.
- Stay in this position; keep your pelvis level and your trunk upright.
- Switch legs and practise on the non-operated leg too.
Movement tips: Keep the standing leg still, and do not let your pelvis drop towards the lifted leg. Look ahead and breathe calmly. Once 30 seconds with your eyes open is easy, you can stand on a pillow or a soft mat or close your eyes, provided the counter is within reach. The sign that you are doing it correctly is that your body sways less and your hand needs the support less.
Amount, repetitions and progression: Stand for 30 seconds each time; once it is easy, add 10 seconds each time until you reach 1 to 2 minutes. Try the eyes-closed version only when you can hold the same position for 30 seconds with your eyes open.
Stop immediately if: you lose your balance or feel dizzy; hold the counter, put your foot down and do not carry on.
Common mistakes: Standing far from the counter, letting the pelvis drop to one side, looking down, and trying the eyes-closed version too early.
Easier version: Go back to supporting yourself with both hands, and shorten the time.
27) Single-leg bridge
You lift your buttocks off the bed as in the bridge, and this time you also lift the non-operated leg off the bed, so that the buttock muscles on the operated side work on their own and get stronger. After the third month, start once the two-leg bridge is easy and pain-free, and repeat 5 to 10 times. If you get a sharp pain in your lower back or hip, or a cramp in the back of your thigh, stop.
More detailLess detail
Before you start: In this exercise, the buttock muscles on the operated side have to hold your pelvis up and level on their own. The single-leg bridge is a harder version of the same bridge; after the third month, start it only once the two-leg bridge has become easy and pain-free for you. As in the two-leg bridge, lie on your back on the bed, with both knees bent, the soles of your feet hip-width apart on the bed, and your arms by your sides with your palms on the bed.
How to do it:
- Tighten your stomach and buttock muscles, and slowly lift your buttocks until your shoulders, hips and knees form an almost straight line.
- Staying in this position, lift the non-operated leg off the bed and hold it up, either straight or with the knee bent; the sole of the operated foot stays on the bed.
- Slowly put the non-operated leg back down on the bed.
- Slowly lower your buttocks.
Movement tips: Lift your buttocks only until your shoulders, hips and knees form a straight line, no higher; do not arch your lower back. While the non-operated leg is up, keep your pelvis level and do not let one side of it drop; do not turn the non-operated leg outwards. Breathe calmly, and rest for a few moments between repetitions. The sign that you are doing it correctly is that both sides of your pelvis stay level and the sole of the operated foot stays steady on the bed. Tightening of the buttocks is normal.
Amount, repetitions and progression: Repeat the single-leg bridge 5 to 10 times; start with 5, and once you can do them without pain and with your pelvis level, build up to 10.
Stop immediately if: you get a sharp pain in your lower back or hip, or a cramp in the back of your thigh.
Common mistakes: Arching the lower back, letting one side of the pelvis drop, turning the non-operated leg outwards and jerking up.
Easier version: Lift the non-operated leg only a little with the knee bent, or keep doing the two-leg bridge for now.
🚗 Driving, work, prayer and daily activities
For each daily activity, the approximate timing and the condition that must be met beforehand are set out below. Read the timing and the condition together, because reaching the date without meeting the condition is not enough.
- Driving: In Dr Emad’s programme, driving starts about 6 weeks after surgery, whether the right or the left hip was operated on. The condition is that you are not taking an opioid pain medicine, alprazolam or gabapentin, that you can get in and out of the car without a cane and without pain, and that in an emergency you can press the brake pedal quickly and without pain. Before your first drive, practise an emergency stop a few times in the car with the engine off.
- Work: In Dr Emad’s programme, you return to desk work 4 to 6 weeks after surgery and to heavy work about 3 months after surgery. You return to work involving long periods of standing about 6 to 12 weeks after surgery, depending on the type of work and how long you have to stand, provided you have set the cane aside and walk without a limp. In the first 3 months, leave lifting and carrying heavy loads to others.
- Prayer: In the first 3 months, pray on a chair. From about 3 months after surgery, if kneeling on a soft mat is comfortable for you, do the bowing (rukūʿ) as usual and the prostration (sujūd) on the floor. Keep using a chair for the tashahhud (sitting) and for long periods of sitting, because in the tashahhud sitting position your two legs are in two different positions and the hip goes to the end of its range of motion. In choosing the alternative position, follow the guidance of your own religious authority (marjaʿ).
- Sitting on the floor and the toilet: Sitting cross-legged, sitting on your knees for long periods and using a squat toilet are not recommended; use a chair and a sit-down toilet or a commode chair placed over the squat toilet. If, after the third month, you have to sit on the floor, sit down and get up with your hand supported on a firm surface and the operated leg stretched out, not by squatting all the way down.
- Sleep: In the first 6 weeks, follow the rules in the “Sleeping, sitting and getting dressed” section, and keep sleeping in a bed, not on a mattress laid on the floor, until the end of the third month. From the seventh week, the pillow between your knees is optional, and you can also sleep on your front, with your toes pointing down.
- Sexual activity: Once the wound has closed and the stitches have been removed, usually from the third to the sixth week, you can resume sexual activity. Until the end of the sixth week, choose a position in which the operated hip does not take any load and does not twist: lying on your back with the operated leg slightly apart and the toes pointing up, or lying on your non-operated side with a pillow between your knees. A position that takes the operated leg backwards and turns it outwards, or puts weight on the knee on that side, is not allowed until the end of the sixth week. If you feel pain or a sense of the joint shifting, stop. If the joint only shifted for a moment and slipped back, and you can walk, call the clinic the same day; if you have signs of a dislocation, act as set out in the “Seek emergency help” box in the warning-signs section. After the sixth week, other positions gradually become allowed, still without strongly turning the leg outwards while taking it backwards.
- Long journeys: In Dr Emad’s programme, while you are taking the blood thinner, that is, in the first 5 weeks, postpone long flights and road journeys of several hours if possible. If you have to travel, stop several times on the way, walk a little and do ankle pumps; on a plane, walk along the aisle every hour. A flight of more than 4 hours increases the risk of a clot; check with the clinic before taking such a flight. Some airlines may require a doctor’s certificate after surgery; check the airline’s requirements before booking your flight.
- Sport: Walking and the stationary bike are part of the rehabilitation programme, and when to start them is on the exercise cards. In Dr Emad’s programme, low-impact sport starts after the third month, that is, from day 91, provided the wound is fully closed and dry and you walk without a cane and without a limp. Swimming, outdoor cycling, golf, light hiking and doubles tennis (with two players on each side of the net) are examples of low-impact sport. Start with short, gentle sessions and let how you feel the next day be your guide; start swimming with short sessions, and do not jump in from the edge of the pool. Most patients return to their previous low-impact sport by about 6 months after surgery. Regular running, jumping, skiing and contact sports, that is, sports such as football in which bodies collide, are not recommended.
❓ Frequently asked questions
1) How long do pain and swelling last after hip replacement?
Swelling may be considerable in the first weeks, and mild to moderate swelling may last 3 to 6 months after surgery. Discomfort during activity and at night is also common for several weeks, but the overall trend should be towards improvement. New and sudden swelling or pain, especially together with calf pain, or pain that is not controlled by your medicines, is not part of this process; in that case, follow the warning-signs section.
2) When are the stitches removed?
In Dr Emad’s programme, stitches or staples are removed at about day 14 after surgery, at your first visit at the clinic. This visit is 10 to 14 days after surgery; at it, the wound is checked, the dressing is changed and your walking with the walker is checked as well. Do not remove the stitches, staples or the adhesive strips on the wound yourself.
3) When can I start taking showers?
From 48 hours after surgery you may take a short shower, provided the wound is dry and the waterproof dressing is intact and fully stuck down. For the first few showers, sit on a shower chair, and if water gets under the dressing, change it that same day for a new waterproof dressing.
4) When can I sleep on my operated side?
You can sleep on your operated side once the stitches have been removed, that is, from about day 14, provided pressure on the wound does not cause significant pain. Before the stitches are removed, sleep on your back or on your non-operated side. Until the end of the sixth week, whenever you lie on your side, also put a pillow between your knees.
5) When can I stop using the walker and the cane?
In Dr Emad’s programme, a walker is needed for about 2 to 4 weeks, and then a cane until you walk without a limp; this is usually around the sixth week. Switch from the walker to the cane when you can stand and walk for more than 10 minutes without leaning your weight on the walker. Set the cane aside when you walk without a limp and without your pelvis dropping to one side.
6) How long is it normal to limp after surgery?
In the first weeks, a limp and weakness in moving the leg out to the side are normal, because the muscles at the side of the hip were opened and repaired during the operation, and in some patients the nerve that supplies them also works less well for a while. That is why the cane stays until the limp has gone, usually until about the sixth week, and the strength of these muscles keeps improving for up to 6 months. Let the clinic know in three situations: a limp that has not improved for two weeks in a row after the sixth week; a limp that had improved and has got worse again, or that comes with new pain at the side of the hip; or being unable to walk without a cane and without an obvious limp 3 months after surgery.
7) Why does my operated leg feel longer?
This feeling is common in the first weeks and most often goes away on its own. Swelling, tight muscles, a previous tilt of the pelvis and limping cause it. Do not put an insole or a heel lift in your shoe yourself. Your leg lengths are examined at the sixth-week visit, and if there is still a noticeable difference at 3 months, it is measured at the clinic; an insole is prescribed only for a measured difference, and only after 3 months.
8) Will the numbness of the skin beside the wound go away?
Numbness of the skin beside the incision, over the side of the thigh and hip, is normal after this operation and may last for months, but it usually lessens with time. Numbness or tingling in the lower leg and the sole of the foot that is still there after one week or has newly appeared, or new weakness in lifting the front of the foot, is not part of this process; in that case, call the clinic the same day.
9) What should I do if I feel that the joint has dislocated?
If sudden, severe pain in the hip or groin comes on together with one of these signs, the joint may have dislocated: the leg looking shorter or longer, the toes staying turned outwards or inwards, being unable to put weight on the leg or move it, or a sound of the joint shifting. In that case, stay where you are, do not walk, do not let anyone try to put the leg back in place, and act as set out in the “Seek emergency help” box in the warning-signs section. If you only felt the joint shift for a moment and slip back, and you can walk, call the clinic the same day. After surgery through the side of the hip, dislocation is rare; in a large study, it happened in about 5 of every 1000 operations.
10) What is heterotopic ossification after hip replacement?
Heterotopic ossification means some extra bone forming in the muscles around the joint, which can be seen on an X-ray. After surgery through the side of the hip, about one in four people have some of it; it is mostly mild and causes no symptoms. In Dr Emad’s programme, no separate medicine is prescribed to prevent it.
11) When are the check X-rays taken?
In Dr Emad’s programme, a check X-ray is taken three times: after the operation in hospital, at about the sixth week at a clinic visit, and one year after surgery. Between these, an X-ray is needed only if a symptom appears, such as a fall, new pain in the thigh or groin, or the leg becoming shorter or turned.
12) How many years does an artificial hip last?
According to figures from countries that record every joint replacement operation, about 58 per cent of total hip replacements last 25 years. This figure is an average across all patients, not a promise for any single patient.
13) Do weight and the type of exercise affect how long the artificial hip lasts?
Yes. The sliding surface between the ball and the socket of every artificial hip gradually wears with everyday use. Excess weight or high-impact activity may make this wear faster and loosen the implant sooner. Keeping a healthy weight and choosing low-impact exercise help the implant last longer. Also take care to prevent falls, because breaking a leg bone in a fall may mean another operation is needed.
14) Can an infection elsewhere in the body reach the artificial hip?
Yes; germs that enter the bloodstream during dental work, or from a urinary or skin infection, may settle around the implant. For this reason, get tooth infections, urinary symptoms and skin wounds or infections treated early, and tell every doctor you see that you have a hip implant.
15) Do I need antibiotics before dental treatment?
Yes; in Dr Emad’s clinic programme, before any invasive dental procedure, such as a tooth extraction, scaling or a dental implant, you take a preventive antibiotic, for life. Tell your dentist that you have a hip implant, and check with the clinic before your appointment. The 2024 guideline of the American Academy of Orthopaedic Surgeons and the American Association of Hip and Knee Surgeons states that routine preventive antibiotics before dental procedures may not reduce the risk of a later infection around the implant; continuing it is the choice of Dr Emad’s clinic.
16) Can I have magnetic resonance imaging (MRI) with an artificial hip?
Yes, but before the MRI, tell the doctor and the imaging centre that you have a hip implant. The metal of the implant may blur the image and make it harder to see damage around the implant.
17) Will an artificial hip set off the airport metal detector?
It may. Before going through the detector, tell the security officer that you have a hip implant. Setting off the detector does not mean the implant is damaged.
✅ Summary and appointments
Recovery after hip replacement moves forward through regular wound care, preventing blood clots, following the movement precautions of the first 6 weeks and the gradual return of strength to the muscles at the side of the hip. Do the exercises correctly and in the amounts set out in the programme, and judge your progress by walking without a limp, not just by the date.
If you have not yet decided on surgery or are getting ready for it, the guide to total hip replacement before surgery explains the reasons for the operation, preparation and the day of surgery.
If you have a sign from the “Call the clinic the same day” list in the warning-signs section, call that same day. For questions about walking and limping, your exercises or the movement precautions, call Dr Jalil Emad’s clinic on 09137825207, or book an appointment online. In an emergency, do not wait for the clinic to reply; follow the instructions in the warning signs section.
To learn more about this treatment, visit the related service page: Joint replacement and reconstruction.
Related guides: Pre-operative guide: Total Hip Replacement: The Pre-Operative Guide · Service page: Joint Replacement & Reconstruction
This content is provided for general education only and does not replace an examination, advice from your treating doctor, your discharge sheet or your surgeon’s specific protocol. Timing, range of motion, weight-bearing and the amount of exercise differ from person to person and depend on the type of operation and your own condition. Do not change your medicines, dressing or exercise programme without checking with the clinic.
📚 Scientific references
View scientific references
- NICE NG157: Joint replacement (primary): hip, knee and shoulder – recommendations
- NICE NG125: Surgical site infections: prevention and treatment – recommendations
- AAOS OrthoInfo: Activities After Total Hip Replacement
- AAOS OrthoInfo: Total Hip Replacement
- AAOS OrthoInfo: Total Hip Replacement Exercise Guide
- AAHKS HipKneeInfo: Total Hip Replacement
- AAHKS: Home Therapy Exercises After Total Hip Replacement (print guide)
- Cambridge University Hospitals NHS FT: Hip replacement (total) – advice and exercises following
- Brown University Health, Newport Hospital: Total Hip Arthroplasty Protocol (2023)
- Yale New Haven Hospital: Your Guide to Joint Replacement Surgery
- MedlinePlus: Hip joint replacement – discharge
- MedlinePlus: Surgical wound care – closed
- Christensen TH et al. How Does Surgical Approach Affect Characteristics of Dislocation After Primary Total Hip Arthroplasty? J Arthroplasty 2023;38(7 Suppl 2):S300-S305 (PMID 37236286)
- Huang XT et al. Comparisons between Direct Anterior Approach and Lateral Approach for Primary Total Hip Arthroplasty in Postoperative Orthopaedic Complications: A Systematic Review and Meta-Analysis. Orthop Surg 2021;13(6):1707-1720 (PMID 34351056)
- Picado CH, Garcia FL, Marques W Jr. Damage to the superior gluteal nerve after direct lateral approach to the hip. Clin Orthop Relat Res 2007;455:209-211 (PMID 16936578)
- Iwakiri K et al. Changes in patient-perceived leg length discrepancy following total hip arthroplasty. Eur J Orthop Surg Traumatol 2021;31(7):1355-1361 (PMID 33502598)
- Llanes PD et al. Patient Perception of Leg-Length Discrepancy and Satisfaction Following Primary Total Hip Arthroplasty. J Arthroplasty 2026;41(8):2441-2445 (PMID 41260316)
- Mula V et al. Venous thromboembolism rates after hip and knee arthroplasty and hip fractures. BMC Musculoskelet Disord 2020;21(1):95 (PMID 32050949)
- Xie Y et al. Cryotherapy in joint arthroplasty rehabilitation: Effects on pain, analgesic consumption, blood loss, and range of motion. Medicine (Baltimore) 2026;105(1):e46802 (PMID 41496145)
- Magan AA et al. Time for return to sport following total hip arthroplasty: a meta-analysis. Hip Int 2023;33(2):221-230 (PMID 34538122)
- Evans JT et al. How long does a hip replacement last? A systematic review and meta-analysis of case series and national registry reports with more than 15 years of follow-up. Lancet 2019;393(10172):647-654 (PMID 30782340)
- Jamari J et al. Range of Motion Simulation of Hip Joint Movement During Salat Activity. J Arthroplasty 2017;32(9):2898-2904 (PMID 28499625)
- Elmenawi KA et al. When Is It Safe for Patients to Air Travel After Total Hip and Knee Arthroplasty: A Comprehensive Review. JBJS Rev 2025;13(4) (PMID 40259452)
- Oputa TJ et al. Is There a Consensus on Air Travel Following Hip and Knee Arthroplasty? Cureus 2023;15(8):e43814 (PMID 37731433)
- AAOS/AAHKS: Prevention of Total Hip and Knee Arthroplasty Periprosthetic Joint Infection in Patients Undergoing Dental Procedures – clinical practice guideline (2024)
- RadiologyInfo.org (ACR/RSNA): Magnetic Resonance Imaging (MRI) of the Body
- MedlinePlus: Vitamin D
- MedlinePlus: Vitamin C
- DailyMed: Eliquis (apixaban) prescribing information
- DailyMed: Alprazolam prescribing information
- DailyMed: Gabapentin prescribing information
- DailyMed: Acetaminophen and codeine phosphate tablets prescribing information
- DailyMed: Oxycodone hydrochloride prescribing information
- DailyMed: Cephalexin capsules prescribing information
- MedlinePlus: Alprazolam
- Flagstaff Bone & Joint: Total Hip Arthroplasty – Surgery Instructions and Home Exercise Program
- FDA: Opioid and benzodiazepine safety warnings (2016)
- AAOS OrthoInfo: Rheumatoid Arthritis of the Foot and Ankle – Braces (joint-support terminology)
- ITF: Tennis Glossary – doubles; ITF Rules of Tennis 2026, Rule 15 and Rule 26 Case 5