🏥 What happens on the day of total knee replacement surgery?
Anaesthesia: The operation is done under spinal anaesthesia or general anaesthesia, and the choice depends on your physical condition. Sometimes, to control pain in the first hours, the nerves around the knee are also numbed for a while; this is called a “nerve block”. The anaesthetist will explain the right method for you.
Moving from the very first day: You start moving your ankle and tightening the front thigh muscle from the first few hours. Your first walk with a walker takes place on the day of surgery or, at the latest, the day after, and in Dr Emad’s programme you put weight on the operated leg from the first day, as far as pain allows. Physiotherapy sessions start on the second day after surgery and continue at a physiotherapy centre after discharge; you book these sessions yourself.
Knee immobiliser: In Dr Emad’s programme, until you can lift the operated leg straight up off the bed without the knee bending, you wear a knee immobiliser (straight-knee splint) when walking. The immobiliser is there to keep walking safe; you do not need a hinged knee brace or a machine that moves the knee for you (CPM).
Hospital stay and discharge: In Dr Emad’s programme, you stay in hospital for 1 to 2 nights, and a check X-ray is also taken after the operation. Before you go home, you must be able to get out of bed and back into it by yourself, your pain must be bearable, you must be able to eat, drink and use the toilet, walk on a flat surface with the walker, and go up and down 2 to 3 steps.
For home: You receive your instruction sheet and the prescription for your medicines at discharge. You will need the walker, a cane for the stairs, the knee immobiliser and compression stockings at home from the first day. For the first few days to few weeks, someone should also help you with household tasks.
Pain and swelling: In the first days, pain, swelling and warmth around the knee are to be expected. But pain that is not controlled by your medicines, or swelling that suddenly increases, is not normal; in these cases, call the clinic the same day.
⚠️ Warning signs: when should you call urgently?
Call the clinic the same day: Spreading redness, warmth or swelling around the wound; Thick, smelly discharge, or discharge that is not lessening; The wound edges opening; A fever of 38.5°C or above, or chills; Pain not controlled by your prescribed medicines; Sudden or increasing swelling of the knee; New or increasing calf pain, tightness or swelling; Lower-leg or foot numbness or tingling lasting over a week, or new (not skin numbness beside the incision); A fall or a blow to the knee; Red urine, gum or nose bleeding that stops, or unexplained bruising on a blood thinner.
Seek emergency help: Shortness of breath; Chest pain; A very fast heartbeat; Coughing up blood; Bleeding that does not stop with pressure, vomiting blood, or black stools; Fainting; A foot that turns cold or blue; Progressive weakness or numbness; Calf pain and swelling together with shortness of breath or chest pain; Severe sleepiness or slow breathing after an opioid pain medicine or the calming medicine (alprazolam); Hives or swelling of the face after taking a medicine. In Iran, call emergency medical services on 115.
If your symptom is on neither of these two lists, first read the section of this guide that covers it. If you are still worried, do not wait until tomorrow: call Dr Jalil Emad’s clinic on 09137825207, or book an appointment online. In an emergency, do not wait for the clinic to reply; follow the instructions in the emergency box above.
1Care in the first days after surgery
In the first few days, the knee is not expected to be free of pain and swelling; the aim is for pain and swelling to stay under control, for the wound to stay clean and dry, and for the simple movements to be done every day. Do the things below calmly and regularly. The sections below tell you what to expect in the first days.
🩹 Wound care and dressing changes
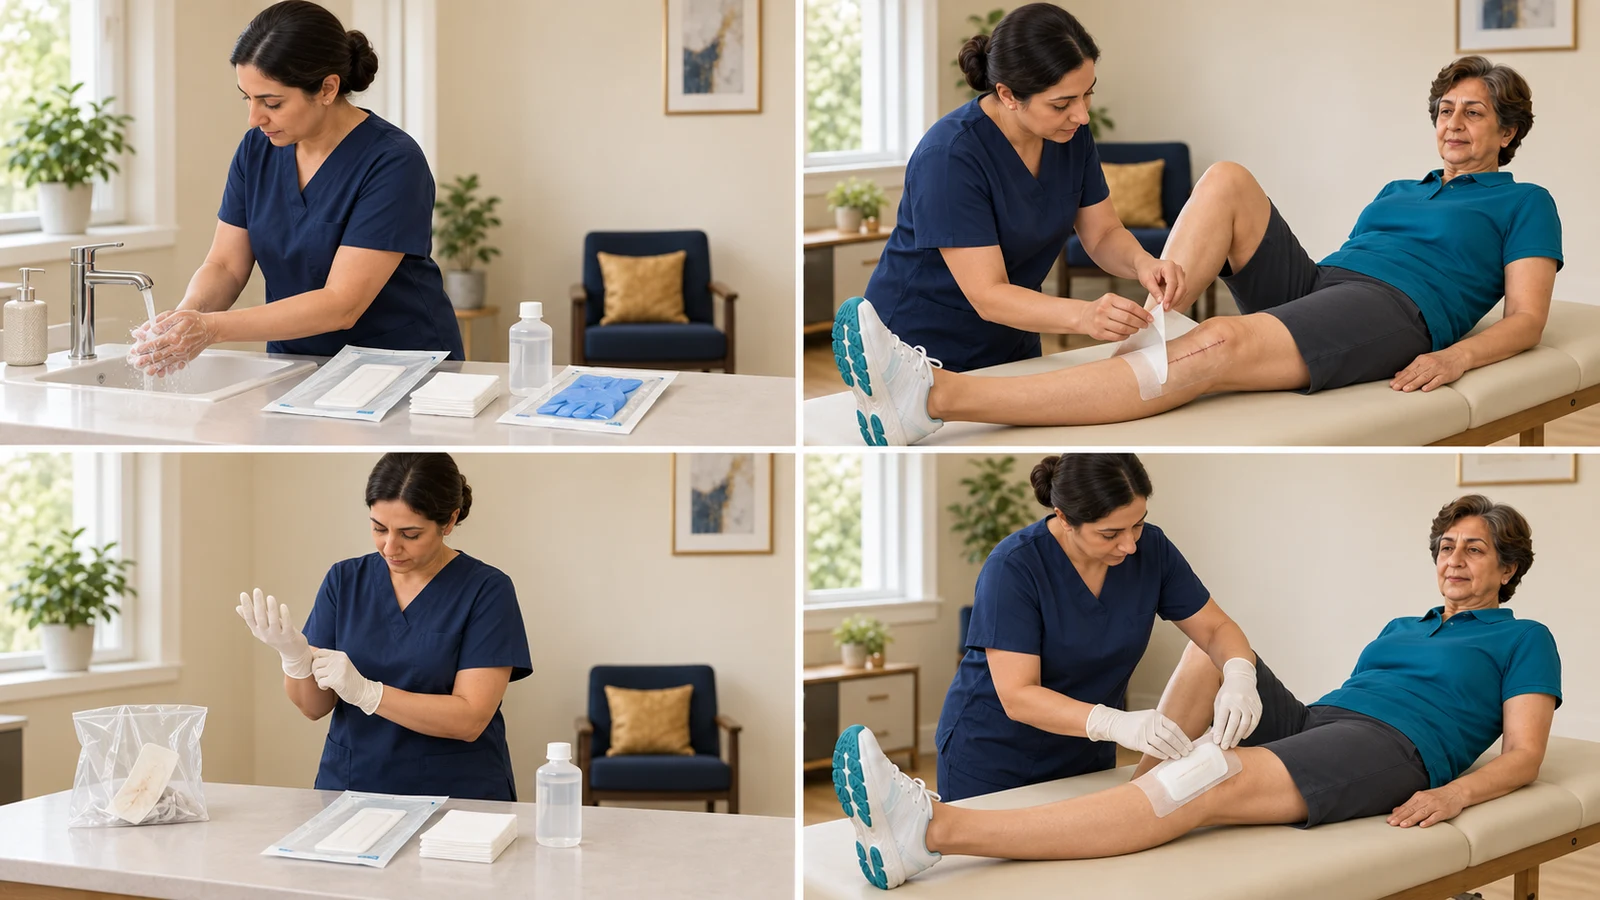
Looking at the wound or changing the dressing may feel a little worrying, but there is no need to rush into doing anything. Under the waterproof dressing, the wound is closing, and it is best left untouched until your first visit; your only task is to keep it clean and dry.
More detailLess detail
- Do not open the waterproof dressing before your first visit, which is 10 to 14 days after surgery; it is changed at that visit, in the clinic. Only if it becomes wet, dirty, loose, or soaked with blood or discharge before then, change it at that moment for a clean, dry dressing; if the bleeding or discharge continues, follow the warning-signs section.
- Before changing it, wash your hands with soap and water, and open the new dressing, gauze and saline on a clean surface. In Dr Emad’s programme, get sterile gloves together with the dressing pack.
- Lift the old dressing gently from one corner without pulling it off in one go, and put it in a bag; then wash your hands again and put on sterile gloves. Stitches, staples, the adhesive strips on the wound and scabs should stay in place. In Dr Emad’s programme, stitches or staples are removed at the clinic about two weeks (14 days) after surgery.
- If the wound needs cleaning, wipe a sterile gauze moistened with sterile saline once from one end of the wound to the other, and dry it the same way with a dry gauze. Apart from sterile saline, do not put anything on the incision line, such as alcohol, Betadine, ointment, cream or powder.
- Put the new dressing on without touching its inner surface and without too much pressure. The tape should not pull on the skin, and your toes should stay warm and pink, with normal feeling.
- Bruising around the knee and slight redness of the skin beside the wound are normal in the first days and fade on their own. If you see spreading redness or warmth, thick foul-smelling discharge or the wound edges opening, follow the warning-signs section.
🚿 Showering with a waterproof dressing
The key points when showering are that water must not get under the dressing, the wound must not be rubbed, and you must not fall in the bathroom.
More detailLess detail
- From 48 hours after surgery you may take a short shower, provided the wound is dry and the waterproof dressing is intact and fully stuck down.
- Do not aim a strong jet of water directly at the knee, and do not rub a washcloth or soap over the dressing. After the shower, dry around the dressing by patting gently with a towel.
- Sit on a sturdy chair in the bathroom, put down a non-slip mat, have a grab handle to hold, and do not bathe alone the first few times.
- If water gets under the dressing or its corners lift, change it at that moment for a clean, dry dressing.
💊 Your medicines and how to take them correctly and PRP
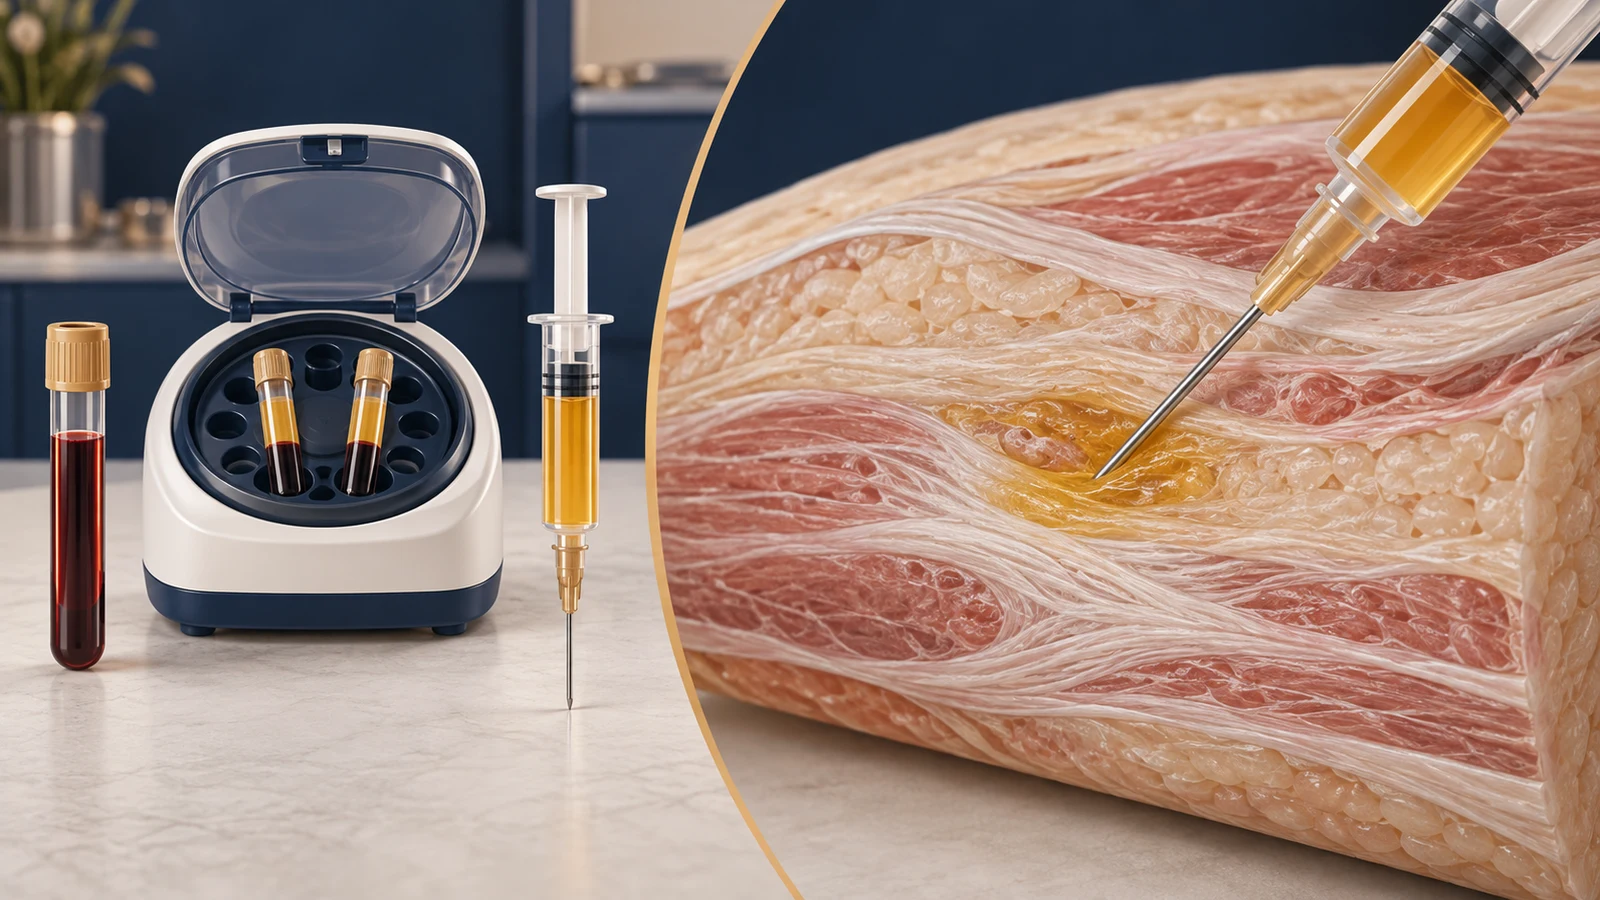
Your prescription may not include all of these medicines. Read the amount of each medicine from your own prescription, and if you are unsure, ask your doctor or pharmacist. Platelet-rich plasma (PRP) is prepared from a small sample of your own blood. Platelets contain growth factors; the aim is to support natural tissue healing.
More detailLess detail
- Cephalexin: This antibiotic prevents infection at the surgical site, and in Dr Emad’s programme it is taken for 7 days. If hives, swelling of the face or shortness of breath appear, stop the medicine and call emergency services right away.
- Aspirin or apixaban: To prevent blood clots in the leg veins, Dr Emad prescribes one of these two, depending on your risk, for 4 to 5 weeks. Take the medicine at a fixed time and do not stop it on your own. If bleeding does not stop with pressure, if you vomit blood or cough up blood, or if you see black stools, call emergency services right away; report red urine, bleeding from the gums or nose that does stop, and unexplained bruising to the clinic the same day.
- Famotidine or pantoprazole: One of these two medicines is prescribed to protect the stomach from pain relievers and aspirin. Take it as prescribed.
- Gabapentin: In Dr Emad’s programme, gabapentin is sometimes prescribed alongside pain relievers to reduce pain after surgery. Do not stop this medicine suddenly. Before your medicine runs out, ask your doctor or pharmacist for the exact reduction plan at the end of the prescribed course. Follow that plan to reduce the daily amount gradually over about a week until you stop.
- Acetaminophen with codeine: This tablet contains codeine, which is an opioid pain medicine; take it only when you are in pain. While you are taking this tablet, do not take any other medicine that contains acetaminophen, such as a cold tablet or cold powder. This tablet may cause constipation; have more water, fruit and vegetables and keep walking, and if you have not had a bowel movement for 3 days, call the clinic.
- Oxycodone: Take this opioid pain medicine only if it is on your prescription and you need it; it is usually not needed for more than a few days. On days when you take this medicine, do not take alprazolam and do not drink alcohol. This medicine may also cause constipation; follow the same advice as for acetaminophen with codeine.
- Alprazolam: This calming medicine is prescribed only in the first days, when needed. On days when you take oxycodone, do not take alprazolam, because together these two medicines may slow your breathing dangerously. Codeine with alprazolam can also increase sleepiness and slow breathing. If both are on your prescription, clarify the exact plan with your doctor or pharmacist and do not take extra doses on your own. If you already take alprazolam regularly, do not abruptly stop it in order to take a pain medicine; clarify the plan with your prescriber before taking the pain medicine.
- Collagen: Collagen is a food supplement, not a medicine. In Dr Emad’s programme 10 g of collagen a day is recommended for 3 months after surgery; take it alongside doing your exercises, not instead of them.
- Vitamin D: Vitamin D helps the body absorb calcium, and the body needs calcium to build bone. In Dr Emad’s programme 1000 to 2000 units a day are taken for 3 months; do not take more than this.
- Vitamin C: The body needs vitamin C to make collagen and to heal wounds. In Dr Emad’s programme 1000 milligrams of vitamin C a day are taken for 6 weeks.
- Write down the name of each medicine and the time of each dose, and if a dose is missed, do not double the next one.
- Do not add any new medicine, supplement or herbal medicine without asking your doctor or pharmacist. Pain relievers such as ibuprofen may interact with your blood thinner.
- While you are taking alprazolam, gabapentin or an opioid pain medicine, do not drive and do not drink alcohol, and keep opioid pain medicines out of children’s reach. If severe sleepiness or slow breathing occurs, the people with you must call emergency services right away; the emergency number is in the “Seek emergency help” box in the warning-signs section.
- After total knee replacement, Dr Emad may consider PRP in selected cases to support tissue healing. In several studies, PRP used during surgery was associated with less pain in some postoperative weeks; however, better movement and overall knee function have not been clearly established, and this evidence does not provide a postoperative injection programme. If suitable for you, your care team decides the details and performs the treatment; continue exercises and physiotherapy as planned.
🧊 Controlling pain and swelling
Swelling, bruising and mild warmth around the knee are common in the first weeks, and mild swelling may last 3 to 6 months. The overall trend should be towards improvement; if today’s activity makes the pain or swelling clearly worse the next morning, cut your activity back to the level you managed before without trouble.
More detailLess detail
- Put a cold pack on the knee for 15 to 20 minutes at a time, 3 to 4 times a day and after exercise. Keep a thin cloth between your skin and the pack, and never let a session go beyond 20 minutes.
- After each session, check the colour and feeling of your skin. If the skin turns very white, or you notice numbness that does not go away or a burning pain, remove the cold and do not repeat it until the skin is back to normal.
- When resting, place your calf and heel on a pillow so that the leg is higher than your heart. Do not put the pillow under the knee itself; the knee needs the chance to straighten fully.
- In the first days, if you need pain medicine for exercise, take it about 30 minutes before exercise or physiotherapy so that moving is easier.
- In Dr Emad’s programme, wear compression stockings during the day for 4 to 6 weeks. The stockings must not wrinkle; check the colour and feeling of your toes every day.
- Do not stay on complete bed rest, and do not sit for more than 45 minutes at a stretch. After every 45 minutes of sitting, get up and walk a few steps.
🚶 Walking, the knee immobiliser, the walker and stairs
You walk with a walker from the very first day and put weight on the operated leg as far as pain allows. In Dr Emad’s programme a walker is needed for about 2 to 4 weeks, and after that you continue with a cane until you walk without a limp; this usually takes up to about 6 weeks.
More detailLess detail
- Wear the knee immobiliser when walking, and take it off for the exercises on the bed and in the chair. Once you can lift the operated leg straight up off the bed without the knee bending, the immobiliser is set aside.
- Walk several short times during the day, a little more each day. The aim for the first few weeks is to build up to about 30 minutes of walking, 2 to 3 times a day.
- Move the walker a little forward, then step the operated leg forward with the knee straight so that the heel touches the ground first, and then bring the non-operated leg forward. To turn, take several small steps, and do not pivot on the operated leg.
- Start using the cane for walking, instead of the walker, when you can stand and walk for more than 10 minutes and no longer lean any of your weight on the walker; in Dr Emad’s programme this is usually 2 to 4 weeks after surgery. Hold the cane in the hand opposite the operated knee; if your left knee was operated on, hold the cane in your right hand.
- On stairs, lead with the non-operated leg going up and with the operated leg coming down, and always hold the handrail; one step at a time. Leave the walker at the bottom or top of the stairs and go up and down with the handrail and one cane: hold the handrail with one hand and the cane with the other, whichever side the handrail is on. Until the knee’s strength has come back, have someone beside you.
- Make your home safe for walking: remove small slippery rugs and cables from your path, leave a light on along the way to the toilet at night, and do not carry anything in your hands while walking. Have a sturdy, fairly high chair with two armrests ready, and a sit-down toilet or a raised toilet seat.
🫀 Preventing blood clots
Blood clots in the leg veins are among the most common complications of knee replacement, and they become dangerous if they reach the lungs. Prevention has four parts; keep up all four until the end of their set period.
More detailLess detail
- Blood thinner (aspirin or apixaban): take it for 4 to 5 weeks, at a fixed time, without stopping it on your own.
- Compression stockings: wear them during the day for 4 to 6 weeks.
- Ankle pumps: do them every waking hour; the details are on the card for this exercise.
- Short, frequent walks: do not forget them, and do not sit for more than 45 minutes at a stretch.
- Know the signs of a blood clot: new or increasing calf pain, tightness or swelling, especially on one side. If a clot reaches the lung, sudden shortness of breath or sudden chest pain may also appear. What to do for each sign is set out in the warning-signs section.
🛡️ The first two weeks
In the first two weeks, the aims are to control pain and swelling, to straighten the knee fully, to activate the front thigh muscle and to take short, safe walks with the walker. Start the exercises in this section from the first day. All the exercises together usually take 20 to 30 minutes, 2 to 3 times a day, and you do not need to do them all in one go.
Full straightening of the knee matters most in these two weeks. Knee bending usually reaches about 90 degrees in the first to second week; that is, when you sit on a chair, your lower leg is perpendicular to the floor. If your knee’s range of motion has not improved for two weeks in a row, call the clinic, whatever stage of recovery you are at.
1) Walking with a walker
With the walker, you practise stepping correctly from the first day: heel first, then the sole of the foot, then the toes. In the first days, walk several short times a day. If you feel dizzy, your knee gives way or you feel a sharp pain, sit down and do not carry on.
More detailLess detail
Before you start: Walking correctly is an important part of the knee’s recovery. Start on the day of surgery, once you have no dizziness or nausea. Wear closed, non-slip shoes, and wear the knee immobiliser until you can lift your leg straight up without the knee bending. Stand upright inside the walker frame and share your weight between your hands and your feet.
How to do it:
- Move the walker one short step forward and make sure all four of its legs are on the ground.
- Step the operated leg forward with the knee straight so that the heel touches the ground first.
- As you move forward, put the whole sole of the foot on the ground and take part of your weight through your hands on the walker.
- Bring the non-operated leg forward, and start the next step by moving the walker forward.
Movement tips: Repeat the order “walker, operated leg, non-operated leg” slowly and at an even rhythm, without rushing. Do not drag your toes along the ground, and to turn, take several small steps rather than pivoting on the operated leg. Signs that you are doing it correctly: your trunk stays upright, both feet are inside the walker frame and the heel touches the ground first. Mild tiredness is normal; sit down between sessions and put your leg up.
Amount, repetitions and progression: In the first days, walk several short times during the day, a little more each day; the aim for the first few weeks is about 30 minutes of walking, 2 to 3 times a day. Once you can stand and walk with the walker for more than 10 minutes without putting your weight on it, it is time for the cane.
Stop immediately if: you feel dizzy, your knee gives way or you feel a sharp pain in the knee; sit down right where you are.
Common mistakes: Pushing the walker too far ahead, hanging on your arms, taking long steps, pivoting on the operated leg, and getting up from a chair by pulling on the walker.
Easier version: Shorten the route, and have someone walk beside you for the first few sessions.
2) Ankle pumps
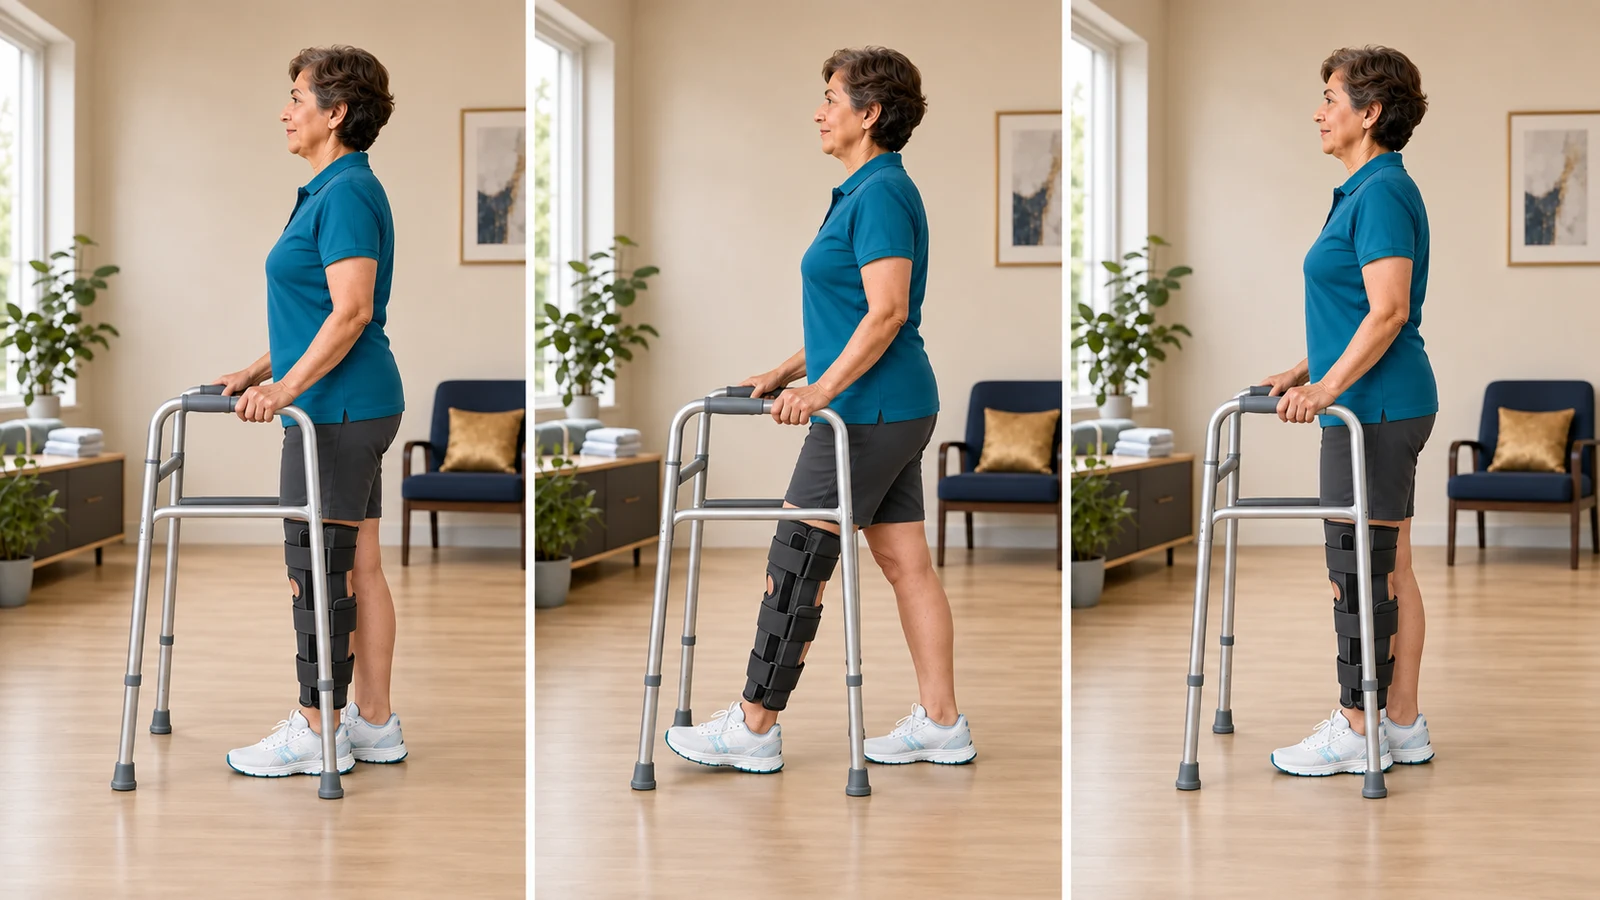
Moving the ankle up and down keeps the calf muscles active and improves blood flow in the leg. From the first hours after surgery, do it 2 to 3 times every waking hour, for 2 to 3 minutes each time. If you develop new or increasing calf pain, tightness or swelling, especially in one leg, or shortness of breath, stop and follow the warning-signs section.
More detailLess detail
Before you start: This movement helps blood circulation in the leg and is part of preventing blood clots. From the first hours after surgery, start lying on your back or half-sitting, with your calf and heel supported; loosen the bedsheet from around your ankle. No equipment is needed.
How to do it:
- Keep your thigh and knee still so that only the ankle works.
- Slowly pull your toes towards your face until you feel a gentle stretch behind the calf.
- Point your toes away from you, as if you were pressing the accelerator pedal.
- Repeat this back-and-forth movement at an even rhythm, without jerking.
Movement tips: You can move both ankles together. Do not push extra at the end of the movement, whether up or down, and do not hold your breath. The sign that you are doing it correctly is that your thigh and knee stay still and only the ankle and toes move. Mild calf tiredness is normal and goes after a few moments of rest.
Amount, repetitions and progression: Do it 2 to 3 times every waking hour, for 2 to 3 minutes each time. Keep doing this exercise at home until the swelling in your ankle and calf has gone completely; also do it during long periods of sitting and when travelling.
Stop immediately if: you develop new or increasing calf pain, tightness or swelling, especially in one leg, or shortness of breath; follow the warning-signs section.
Common mistakes: Fast, jerky movement, rotating the whole leg instead of moving the ankle, and holding your breath.
Easier version: Make the movement smaller; even a short ankle movement is better than staying still.
3) Tightening the front thigh muscle (Quadriceps Sets)
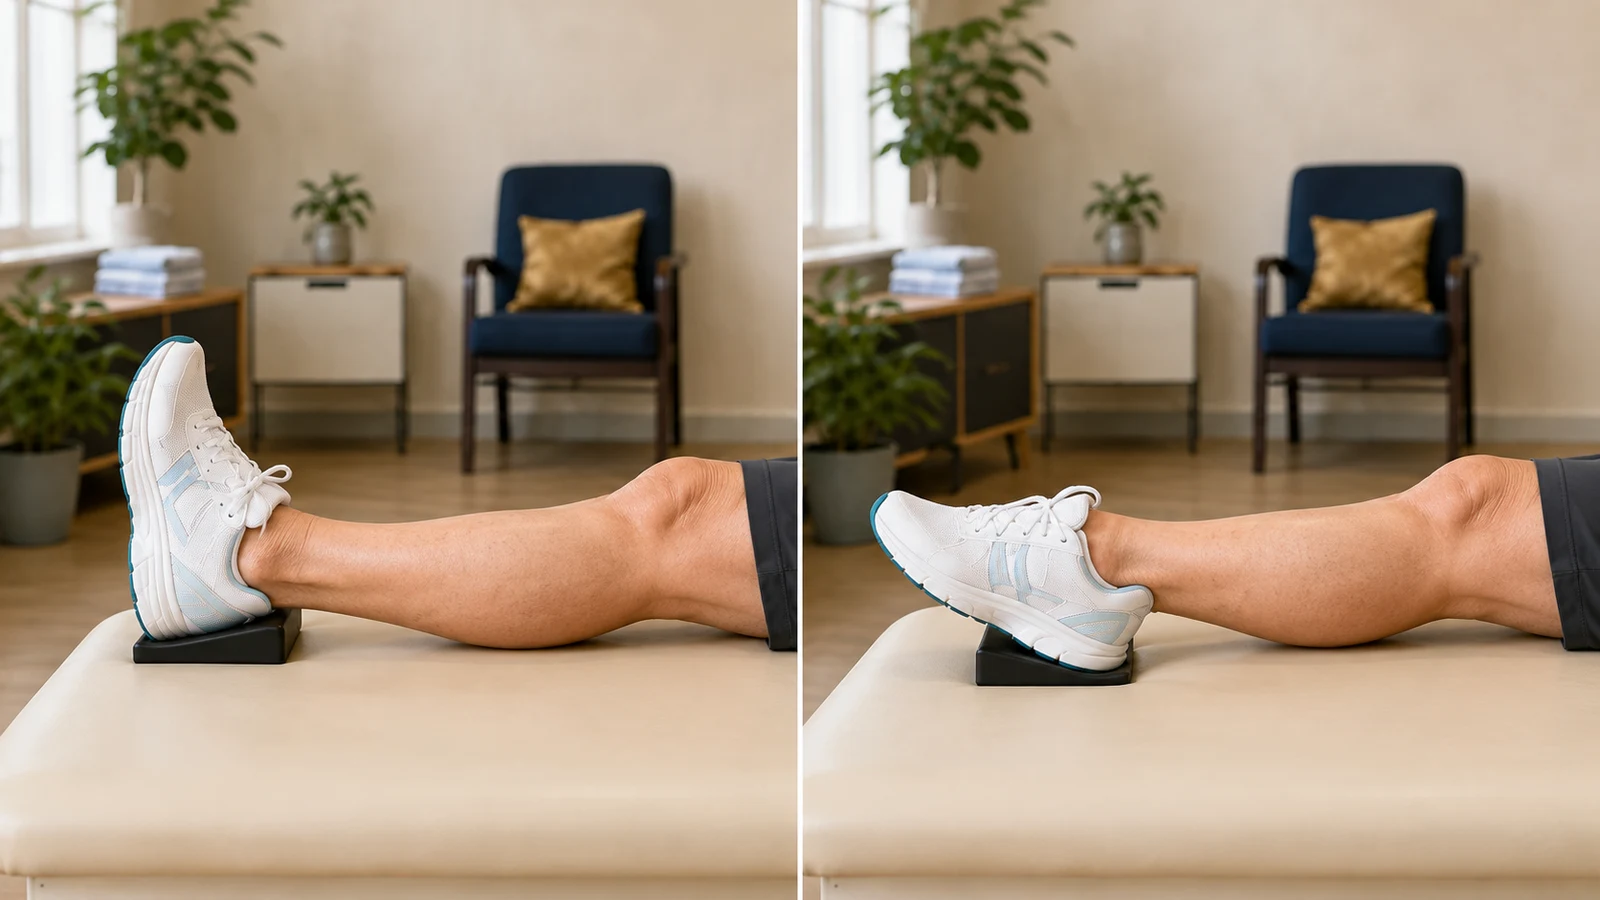
Tightening the front thigh muscle without moving the knee makes this muscle active again. Hold each time for 5 to 10 seconds and repeat about 10 times in 2 minutes. If you feel a sharp pain inside the knee instead of tension in the muscle, or the discharge from the wound increases, stop.
More detailLess detail
Before you start: After surgery, the front thigh muscle is weak and hard to tighten; this exercise gets it working again and is needed to keep the knee straight when you walk. From the first day, start lying on your back or sitting with your leg straight on the bed. For this exercise only, place a small rolled-up towel under the back of the knee, with your toes pointing to the ceiling; remove the towel after the exercise.
How to do it:
- Tighten the front thigh muscle and gently press the back of the knee down into the towel.
- Hold this position and breathe calmly.
- Relax the muscle completely and rest for a few moments.
- Tighten again; the heel stays on the bed.
Movement tips: The knee hardly moves; only the muscle tightens, and the kneecap moves up slightly. Do not tighten your buttocks or the non-operated leg, and do not hold your breath. The sign that you are doing it correctly is that the front thigh muscle stands out and the back of the knee moves closer to the towel. Muscle tiredness is normal, but the knee should not be more swollen after the exercise.
Amount, repetitions and progression: Hold each contraction for 5 to 10 seconds and repeat about 10 times in 2 minutes; then rest for 1 minute and start again until your thigh is tired. Once the muscle tightens firmly, start the straight leg raise.
Stop immediately if: you feel a sharp pain inside the knee instead of tension in the muscle, or the discharge from the wound increases.
Common mistakes: Lifting the heel or the buttocks, tightening the non-operated leg instead of the operated one, and holding your breath.
Easier version: Hold the contraction for a shorter time, and start with fewer repetitions.
4) Straightening the knee with a towel under the heel (Knee Straightening (Heel Prop))
Placing a towel under the heel gives the knee the chance to straighten fully; full straightening is essential for walking properly. Hold the knee straight for 5 to 10 seconds each time; the whole exercise takes about 3 minutes. If you get a sharp pain behind or inside the knee, or your leg tingles, stop.
More detailLess detail
Before you start: A knee that does not straighten fully makes you limp and makes walking tiring. From the first day, lie on your back or sit on the bed, and place a folded towel under the heel only, so that the heel is off the bed and the back of the knee stays completely free.
How to do it:
- Keep your toes pointing to the ceiling.
- Tighten the front thigh muscle and try to bring the back of the knee down to the bed.
- Keep the knee fully straight.
- Relax the muscle and let the weight of your lower leg gently straighten the knee a little further; then repeat.
Movement tips: The support goes under the heel only, never under the knee. A mild stretch behind the knee is to be expected and should settle a few minutes after you finish. Do not press on the knee with your hand, and do not put a weight on it. The sign that you are doing it correctly is that the gap between the back of the knee and the bed gets smaller day by day.
Amount, repetitions and progression: Hold it straight for 5 to 10 seconds each time and repeat until your thigh is tired; the whole exercise takes about 3 minutes. Do this exercise every day; in the first weeks, full straightening of the knee comes first.
Stop immediately if: you get a sharp pain behind or inside the knee, or your leg tingles.
Common mistakes: Putting the towel under the knee, pressing the knee down with your hand or a weight, and turning the toes outwards.
Easier version: Use a thinner towel, and make each session shorter.

5) Heel slides
By sliding your heel along the bed, you gradually increase how far the knee bends. Pause for 5 to 10 seconds at the deepest bend; the whole exercise takes about 2 minutes. If you feel a sharp pain inside the knee instead of a stretch, or the discharge from the wound increases, stop.
More detailLess detail
Before you start: The knee has to bend for sitting down, getting up and stairs, and this exercise gently brings that bending back. From the first day, lie on your back on the bed with both legs straight, or sit leaning back; with socks on, your heel slides more easily on the sheet.
How to do it:
- Slide the heel of the operated leg along the bed towards your buttock so that the knee bends.
- Pause at the deepest bend at which you still feel only a stretch.
- Slowly slide the heel forward until the knee is fully straight again.
- Repeat several times; the kneecap always stays pointing to the ceiling.
Movement tips: Keep the knee in line with your toes, and do not let it fall inwards or outwards. Breathe out as you bend, and do each back-and-forth movement slowly. A stretch at the front of the knee is to be expected and should settle quickly. The sign that you are doing it correctly is that the heel slides along a straight line and your pelvis does not lift off the bed.
Amount, repetitions and progression: Pause for 5 to 10 seconds at the deepest bend and repeat several times, until your leg is tired or the knee bends fully; the whole exercise takes about 2 minutes. Bend a little further each day; if pain or swelling is worse by the next morning, reduce the range and go back to the previous day’s amount.
Stop immediately if: you feel a sharp pain inside the knee instead of a stretch, or the discharge from the wound increases.
Common mistakes: Lifting the pelvis, letting the knee fall inwards, jerky movement and holding the position for a long time in pain.
Easier version: Make the range smaller, or use a towel looped around your ankle to pull your heel gently towards your buttock.
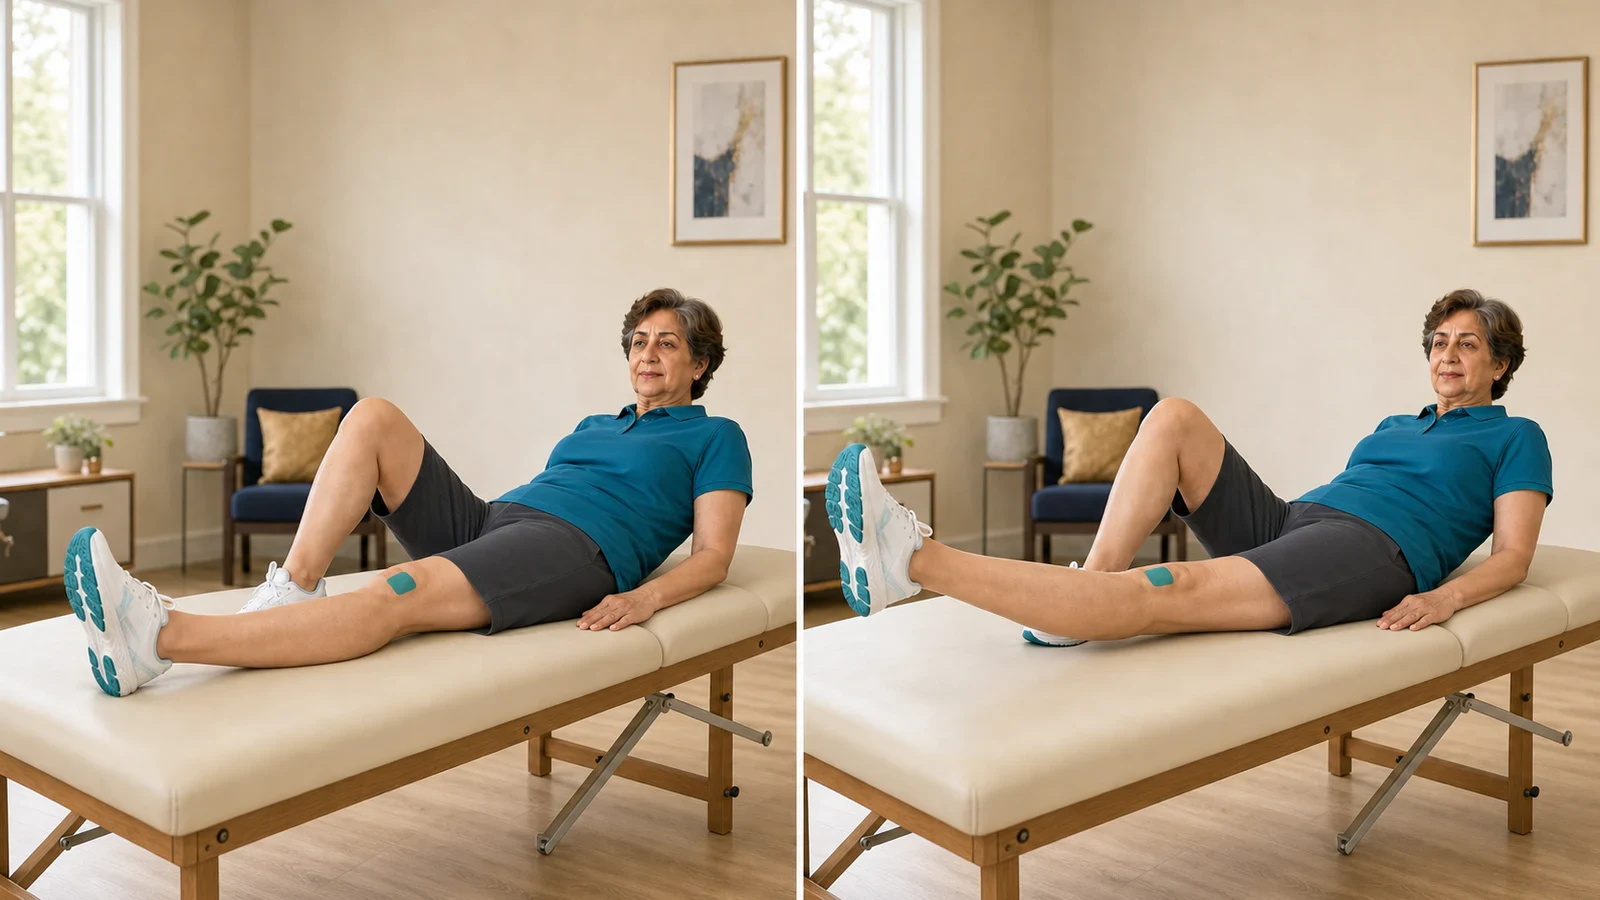
6) Straight leg raise
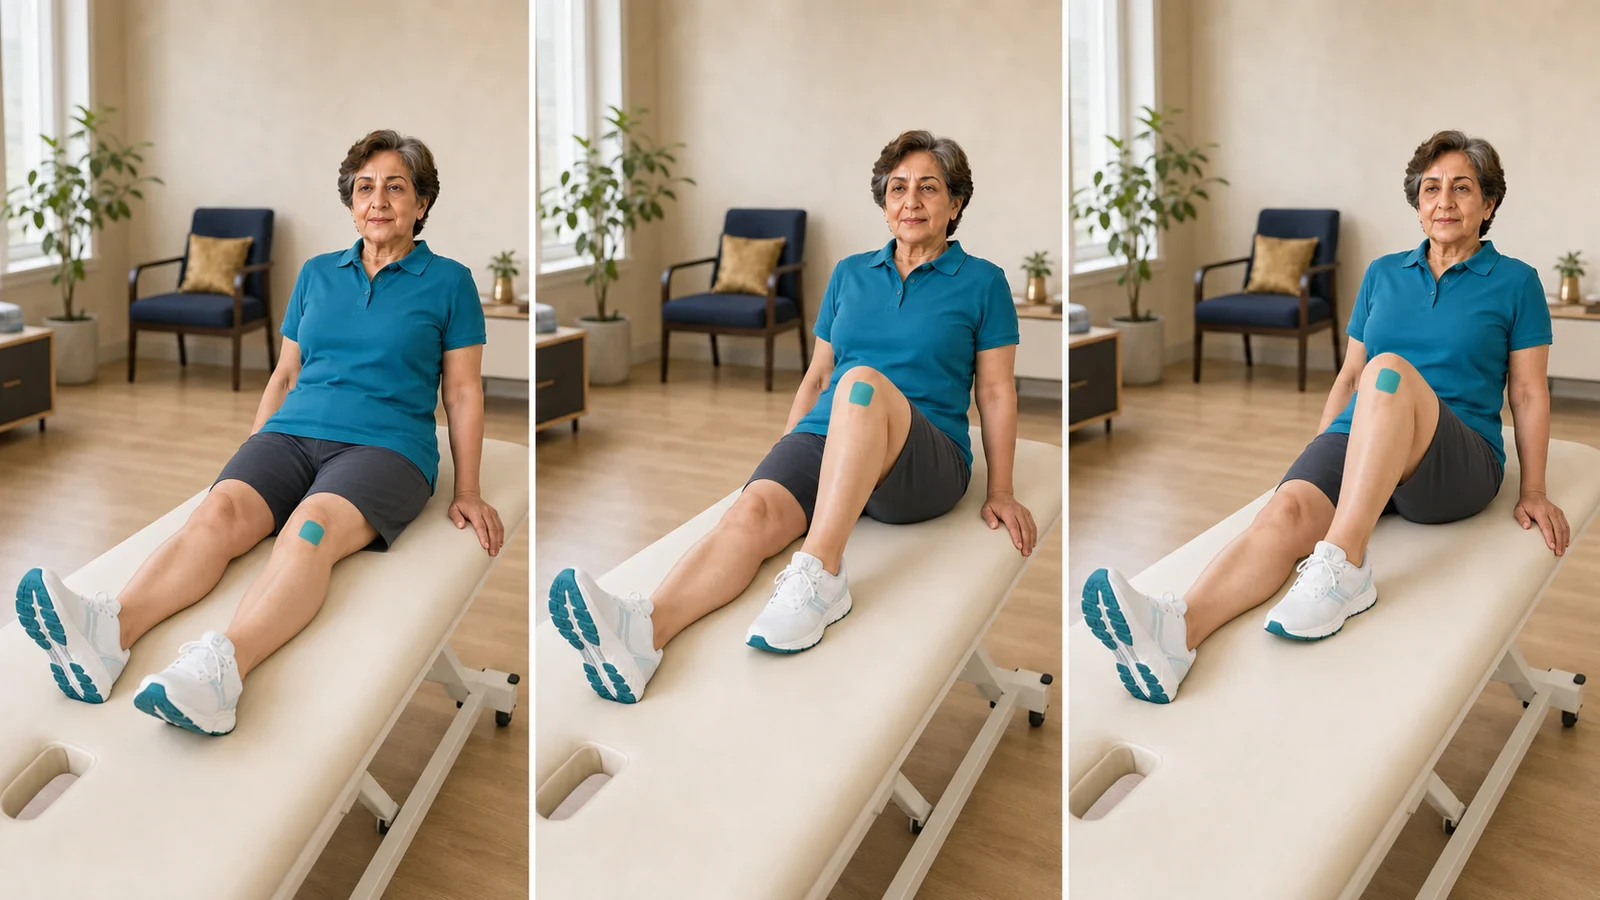
This exercise strengthens the front thigh muscle; once you can lift the leg without the knee bending, the immobiliser is set aside. Hold the leg up for 5 to 10 seconds each time; the whole exercise takes about 3 minutes. If the knee bends as you lift, your lower back arches or you get a sharp pain inside the knee, stop.
More detailLess detail
Before you start: The front thigh muscle must be able to hold the knee straight and firm when you walk. Start in the first few days, once you can tighten the front thigh muscle well. Lie on your back on the bed or sit leaning back; bend the non-operated leg and put its sole flat on the bed, and keep the operated leg straight with its toes pointing to the ceiling.
How to do it:
- Tighten the front thigh muscle of the operated leg so that the knee is fully straight.
- Lift the leg a few centimetres with the knee straight, no higher than the level of the thigh of the bent leg.
- Hold the leg up.
- Lower the leg slowly and relax the muscle.
Movement tips: The knee stays straight throughout the movement; if it bends a little as you lift, the muscle is not ready yet and you need to practise tightening the muscle more. Breathe out as you lift, and lower the leg slowly. Your lower back stays on the bed. Tiredness at the front of the thigh is normal, but joint pain or increased swelling is not.
Amount, repetitions and progression: Hold the leg up for 5 to 10 seconds each time and repeat until your thigh is tired; the whole exercise takes about 3 minutes. Continue this exercise until your thigh strength has fully returned.
Stop immediately if: the knee bends as you lift, your lower back arches or you get a sharp pain inside the knee.
Common mistakes: Lifting the leg before tightening the muscle, letting the knee bend, swinging the leg and holding your breath.
Easier version: For now, only tighten the front thigh muscle, or do not lift the leg as high.
↔️ The second two weeks
By the start of these two weeks your stitches have been removed at the first visit; during them the cane usually takes the place of the walker, and the knee bends further. Standing exercises with a fixed support are added; keep doing the exercises from the first two weeks as well.
Continue the blood thinner and the compression stockings until the end of their set periods. Driving is not yet allowed.
7) Sitting down and standing up from a chair (Sit to Stand)
With this exercise, you practise getting up from a chair safely, and your thighs and buttocks get stronger. Start with one short group of repetitions (a set) and gradually build up to 3 groups each time you exercise, with 15 to 25 repetitions in each group. If your knee gives way, you feel dizzy or you get a sharp pain in the knee, sit down and do not carry on.
More detailLess detail
Before you start: Getting up from a chair is one of the things you do most often in a day. Use the safe way of getting up (pushing on the chair’s armrests, never pulling on the walker) every time you stand up from the first day; start repeating it as a group of consecutive repetitions from the third week, once standing with the walker is safe. Choose a sturdy, fairly high chair without wheels and with two armrests, and place the walker in front of you; sit on the edge of the chair with the soles of both feet on the floor and the operated leg slightly further forward.
How to do it:
- Lean your trunk slightly forward from the hips until your head is above your toes.
- Push down on the armrests of the chair with your hands and stand up on both legs.
- Stand fully upright, and then put your hands on the walker.
- To sit down, step back until you feel the edge of the chair against the back of your legs, take hold of the armrests and sit down slowly.
Movement tips: Both legs should take your weight, and the operated knee should not fall inwards. Breathe out as you stand up, and sit down slowly and with control rather than dropping onto the chair. Never pull on the walker to get up; the walker is for standing, not for pulling yourself up. Thigh tiredness is normal.
Amount, repetitions and progression: Start with one short group of repetitions; the aim is 3 groups each time you exercise, with 15 to 25 repetitions in each group. Do this exercise 5 to 7 days a week. Once the movement is smooth and controlled and both legs are working equally, rely less on your hands and use a lower chair.
Stop immediately if: your knee gives way, you feel dizzy or you get a sharp pain in the knee; sit down.
Common mistakes: Pulling on the walker, dropping onto the chair, tucking your feet under the chair and getting up with the non-operated leg only.
Easier version: Use a higher chair, or put a firm cushion on the chair.

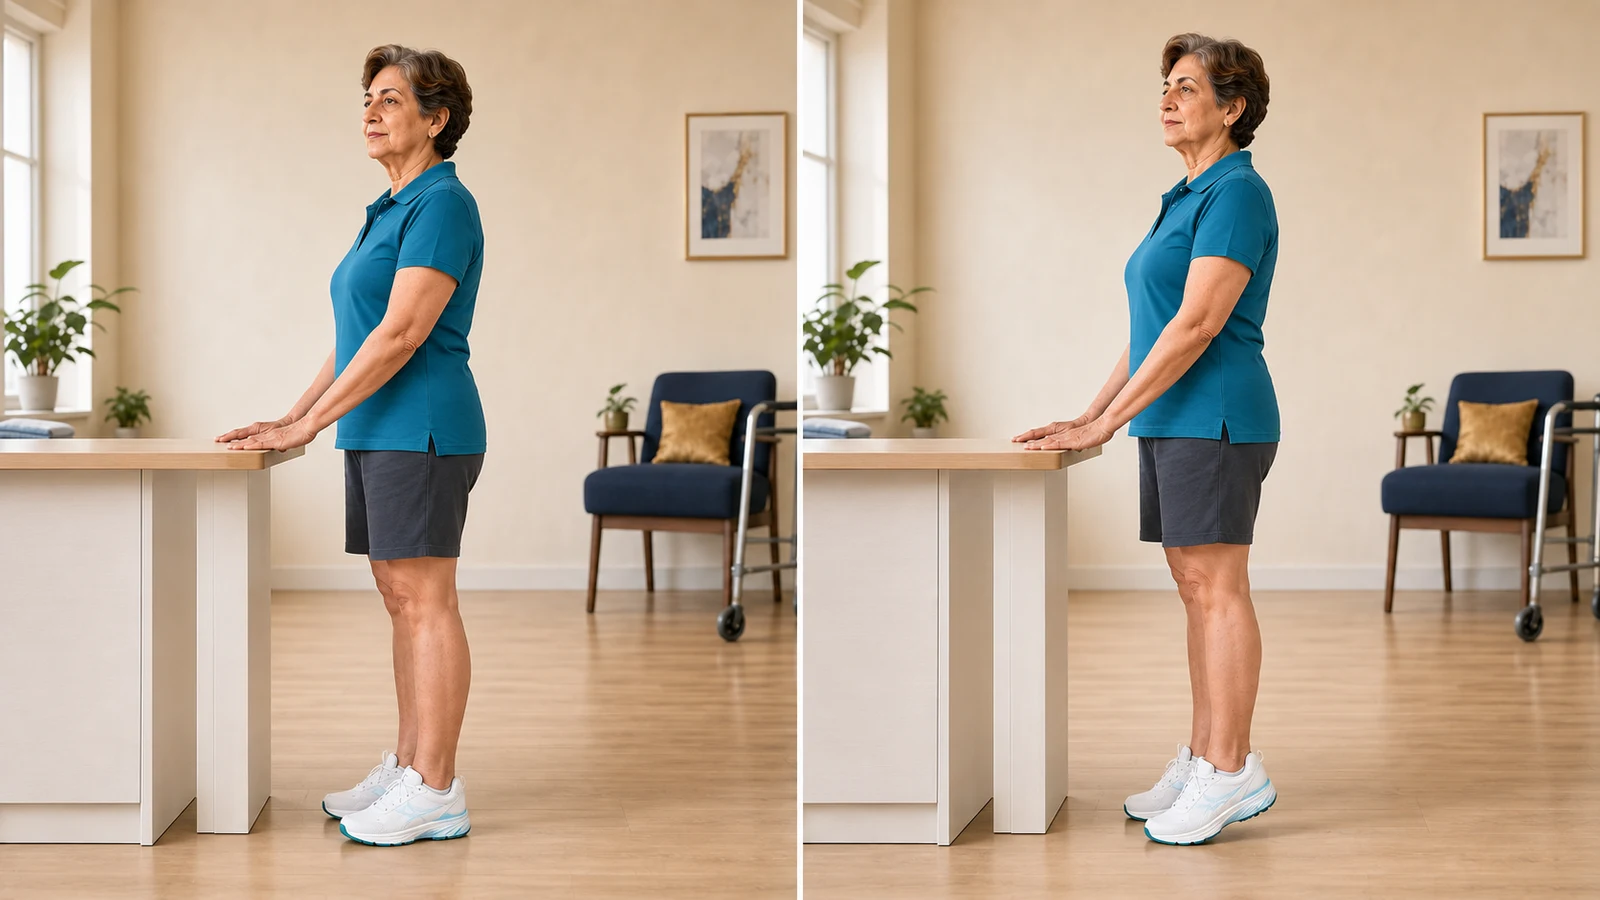
8) Rising onto the toes with support (Standing Heel Raises)
This exercise strengthens the calf muscles and helps your balance and stepping. Each time you exercise, do 3 groups, repeating the movement 10 times in each group, staying on your toes for 5 seconds each time. If you lose your balance, your body sways, or a calf cramp does not go away after a few moments of rest, stop.
More detailLess detail
Before you start: When you walk and use stairs, the calf muscles push the body forward with each step. Start once you can stand with light support and put your weight evenly on both legs. Stand at a kitchen counter or a fixed handrail, not at a light chair; keep your feet shoulder-width apart and your knees straight, but do not push them backwards.
How to do it:
- Put both hands on the support and spread your weight over both feet.
- Slowly lift both heels off the floor by the same amount.
- Stay up on your toes.
- Lower your heels slowly to the floor.
Movement tips: Keep your body upright without swaying forwards and backwards; your weight should be equal on both feet. Breathe out as you rise, and come down slowly. The sign that you are doing it correctly is that both heels rise together and by the same amount. Calf tiredness is normal.
Amount, repetitions and progression: Each time you exercise, do 3 groups, repeating the movement 10 times in each group, staying on your toes for 5 seconds each time. Once you are stronger, do the same exercise on one leg at a time, taking turns with each leg.
Stop immediately if: you lose your balance, your body sways, or a calf cramp does not go away after a few moments of rest.
Common mistakes: Leaning on a light chair, putting your weight on the non-operated leg only, and dropping down suddenly.
Easier version: Do not lift your heels as high, and hold on firmly to the support with both hands.
9) Knee bending while standing (Standing Knee Bends)
Standing up, you bring your heel up towards your buttock so that the knee bends through the work of the hamstrings (back-of-thigh muscles). Each time you exercise, do 3 groups, repeating the movement 10 times in each group, staying at the deepest bend for 5 seconds each time. If you lose your balance or feel a sharp pain in the knee, stop.
More detailLess detail
Before you start: This exercise increases knee bending through the work of the muscles themselves. Start from the third week, once standing with light support is safe. Stand facing a kitchen counter or a fixed handrail and hold on with both hands; keep your weight on the non-operated leg.
How to do it:
- Keep the thigh of the operated leg straight and beside the other thigh.
- Slowly bring your heel up towards your buttock so that the knee bends as far as possible.
- Pause at the deepest bend.
- Lower the leg slowly until the sole of the foot is back on the floor.
Movement tips: The thigh does not move forward and the pelvis stays level; only the lower leg moves up and down. Breathe calmly and move without swinging the leg. The sign that you are doing it correctly is that the two knees stay side by side and your trunk is upright. A stretch at the front of the knee and tiredness at the back of the thigh are normal.
Amount, repetitions and progression: Each time you exercise, do 3 groups, repeating the movement 10 times in each group, staying at the deepest bend for 5 seconds each time.
Stop immediately if: you lose your balance or feel a sharp pain in the knee.
Common mistakes: Moving the thigh forward, hitching up one side of the pelvis, swinging the leg and leaning on a light chair.
Easier version: Bend the knee less and hold it for a shorter time.

10) Knee bending with the help of a towel (Assisted Knee Bends)
Using a towel looped around your ankle, you gently bend the knee further. Stay at the deepest bend for 5 to 10 seconds; the whole exercise takes about 2 minutes. If you feel a sharp pain inside the knee, stop.
More detailLess detail
Before you start: When knee bending is progressing slowly on its own, gentle help from your hands moves it forward. From the third week, lie on your back on the bed, loop a long folded towel around the ankle of the operated leg and hold its two ends in your hands.
How to do it:
- Slide your heel along the bed towards your buttock so that the knee bends.
- Pull gently on the towel to bend the knee a little further.
- Pause in this position.
- Loosen the towel and straighten the leg slowly.
Movement tips: Pull on the towel gently and steadily, not in jerks. The kneecap stays pointing to the ceiling, and the knee does not fall inwards or outwards. Breathe calmly. A stretch at the front of the knee is to be expected and should settle a few minutes after the exercise.
Amount, repetitions and progression: Stay at the deepest bend for 5 to 10 seconds and repeat several times, until your leg is tired; the whole exercise takes about 2 minutes. If the stretch has not settled a few minutes after the exercise, pull less on the towel next time.
Stop immediately if: you feel a sharp pain inside the knee instead of a stretch.
Common mistakes: Pulling the towel suddenly, lifting the pelvis and holding the position for a long time in pain.
Easier version: Pull less on the towel, or do only the heel slides.

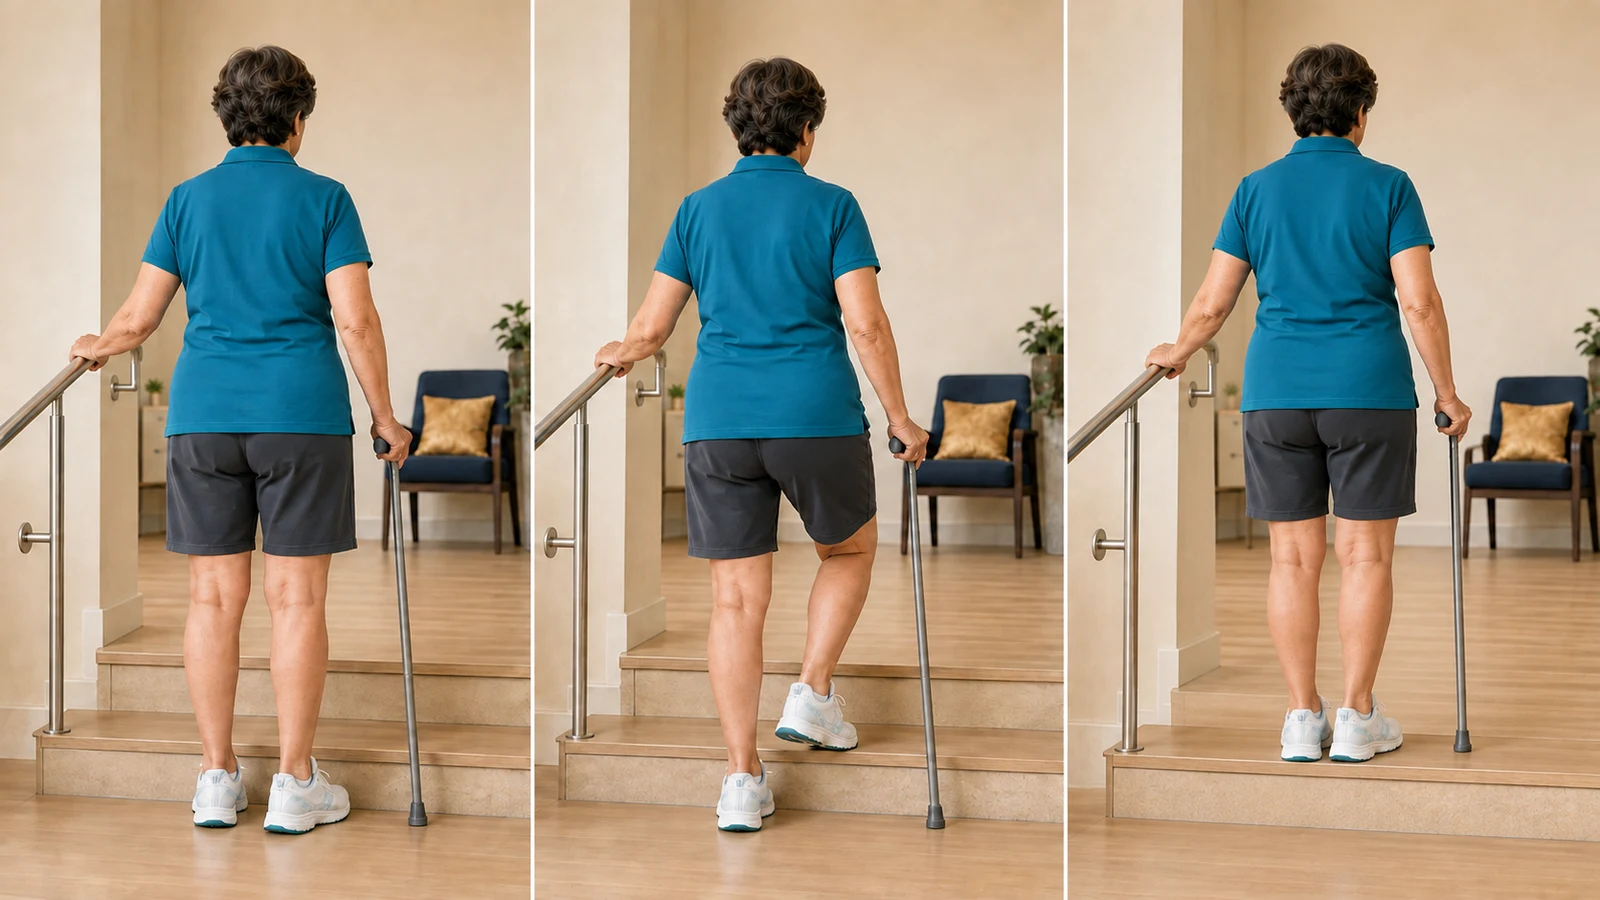
11) Going up stairs with the handrail and cane (Stair Climbing)
Going up stairs, the non-operated leg goes up first, followed by the operated leg and the cane. At the start, 2 to 3 steps are enough. If your knee gives way, you lose your balance, you feel dizzy or you get a sharp pain in the knee, hold the handrail firmly, sit down on the step you are on and do not carry on.
More detailLess detail
Before you start: Going up stairs is both a strength exercise and something you need for life at home. From the first days you use the stairs with the handrail and one cane, with someone beside you, leaving the walker at the bottom or top of the stairs; from the third week, stairs also become part of your daily exercise. Hold the handrail with one hand and the cane with the other, whichever side the handrail is on; the steps should be no higher than the usual height, that is, about 18 centimetres.
How to do it:
- Stand close to the first step and hold the handrail firmly.
- Put the non-operated leg on the step above.
- Push up with the non-operated leg, with help from the handrail, and place the operated leg beside it.
- Bring the cane up onto the same step as well, and start the next step in the same way.
Movement tips: The rule is: “up with the non-operated leg”. Go up one step at a time, and put both feet on the same step. Keep your trunk upright and do not rush. The sign that you are doing it correctly is that you are always supported by the handrail and the cane, and the operated leg comes up after the non-operated leg.
Amount, repetitions and progression: At the start, 2 to 3 steps are enough, and until the knee’s strength has come back, have someone beside you. Add a few more steps each day. Once you walk without the cane and without a limp, put the other foot on the next step each time, as you did before surgery, and keep holding the handrail.
Stop immediately if: your knee gives way, you lose your balance, you feel dizzy or you get a sharp pain in the knee; hold the handrail firmly, sit down on the step you are on and do not carry on.
Common mistakes: Going up with the operated leg first, letting go of the handrail, taking two steps at once and rushing.
Easier version: Go up and down one step only, with someone standing beside you.
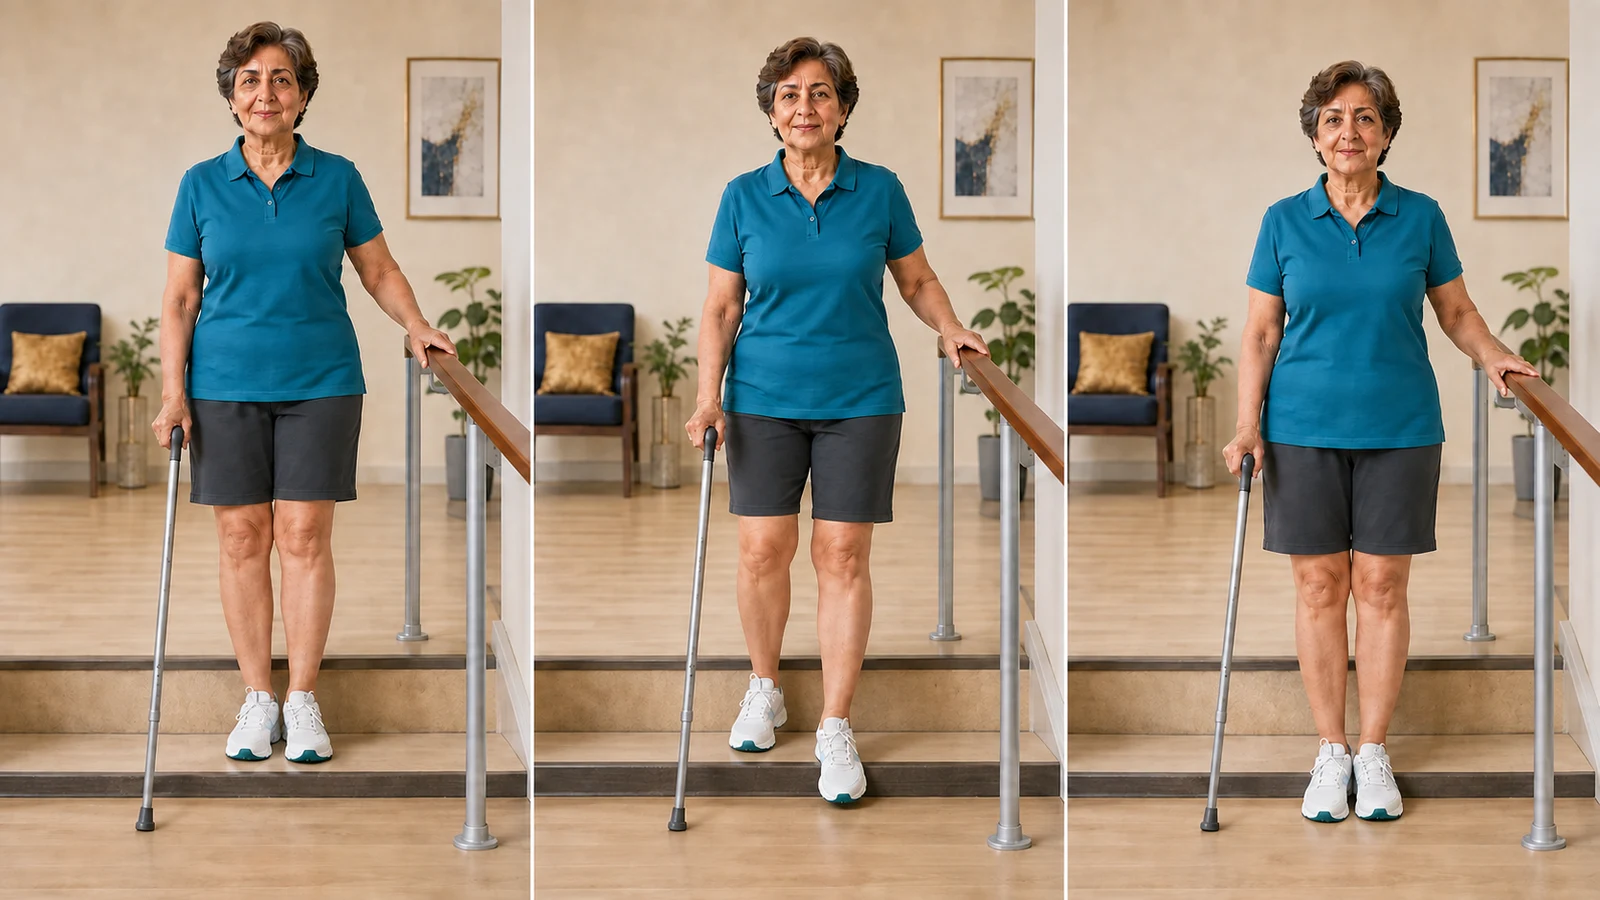
12) Going down stairs with the handrail and cane (Stair Descending)
To go down stairs, put the cane down first, then bring down the operated leg and finally the non-operated leg. At the start, 2 to 3 steps are enough. If your knee gives way, you lose your balance, you feel dizzy or you get a sharp pain in the knee, hold the handrail firmly, sit down on the step you are on and do not carry on.
More detailLess detail
Before you start: Going down stairs is harder for the operated knee than going up. From the first days you come down stairs with the handrail and one cane, with someone beside you, leaving the walker at the bottom or top of the stairs; from the third week, coming down stairs also becomes part of your daily exercise. Stand at the edge of the step, and hold the handrail with one hand and the cane with the other, whichever side the handrail is on.
How to do it:
- Put the cane in the middle of the step below.
- Slowly lower the operated leg onto that same step.
- With help from the handrail and the cane, place the non-operated leg beside it.
- Start the next step in the same way.
Movement tips: The rule is: “down with the operated leg”. Go down one step at a time, and put both feet on the same step. Control your weight with the handrail and the cane, and do not lean forward. The sign that you are doing it correctly is that the operated leg comes down slowly and with control, and the knee does not fall inwards.
Amount, repetitions and progression: At the start, 2 to 3 steps are enough, and until the knee’s strength has come back, have someone beside you. Add a few more steps each day. Once you walk without the cane and without a limp, put the other foot on the next step down each time, as you did before surgery, and keep holding the handrail.
Stop immediately if: your knee gives way, you lose your balance, you feel dizzy or you get a sharp pain in the knee; hold the handrail firmly, sit down on the step you are on and do not carry on.
Common mistakes: Going down with the non-operated leg first, letting go of the handrail, leaning forward and rushing.
Easier version: Go up and down one step only, with someone standing beside you.
🌱 The second month: days 31 to 60
The aims of the second month are walking without a limp, knee bending reaching about 100 to 110 degrees by the seventh week, and starting strength, endurance and balance exercises. Most everyday activities usually become possible by the end of the sixth week.
Set the cane aside when you walk without a limp; this is usually around the sixth week. Driving and desk work also become possible during this month, and the details are in the “Driving, work, prayer and daily activities” section.
13) Stationary bike
A stationary bike both increases how far the knee bends and straightens and makes the muscles stronger. Pedal for 10 to 15 minutes, 2 times a day. If you get a sharp pain in the knee, chest pain, unusual shortness of breath or dizziness, stop and get off slowly; for chest pain or shortness of breath, follow the warning-signs section.
More detailLess detail
Before you start: The bike increases range of motion and strength together, without jarring the knee. Start in the second month; the pedal does not need to turn a full circle from the very beginning. Set the saddle high enough that, when the pedal is at the bottom, the sole of your foot only just reaches it and the knee is almost straight; set the resistance to the lowest level.
How to do it:
- Get on, hold the handlebars and put both feet on the pedals.
- First, turn the pedals slowly backwards.
- Once a full backward turn is comfortable, pedal forwards.
- At the end, slow down and get off slowly, using the handlebars for support.
Movement tips: If a full turn is not possible at first, move the pedal forwards and backwards only as far as is comfortable. To bend the knee further, lower the saddle a little and pedal slowly. The sign that you are doing it correctly is that the knee moves up and down in line with your toes and your pelvis stays still on the saddle.
Amount, repetitions and progression: Pedal 2 times a day, for 10 to 15 minutes each time. Once you are stronger, increase the resistance gradually; if the knee swells after pedalling, shorten the next session.
Stop immediately if: you get a sharp pain in the knee, chest pain, unusual shortness of breath or dizziness; get off slowly, and for chest pain or shortness of breath follow the warning-signs section.
Common mistakes: A saddle that is too low at the start, too much resistance, pedalling fast, and shifting your pelvis on the saddle to complete the turn.
Easier version: Without making full turns, move the pedal forwards and backwards only as far as is comfortable.

14) Supported mini-squat
By bending both knees a little, you make your thighs and buttocks stronger for sitting and stairs. Each time you exercise, do 3 groups, repeating the movement 10 times in each group, with a 5-second pause in each repetition. If the knee falls inwards, you lose your balance or you feel a sharp pain in the knee, stop.
More detailLess detail
Before you start: This exercise strengthens the muscles you need for getting up and for going down stairs. Start in the second month. Stand at a fixed handrail or a kitchen counter and hold on with both hands; keep your feet shoulder-width apart and your toes pointing forward.
How to do it:
- Bend your knees slowly, as if you were about to sit down a little; only as far as a comfortable bend.
- Pause in this position.
- Push through both feet to straighten up slowly.
- Repeat; your knees always stay pointing forward, in line with your toes.
Movement tips: The depth is small; a comfortable bend means that your heels stay on the floor and you have no pain. Your weight should be equal on both legs, and your knees should not fall inwards. Breathe in as you go down and breathe out as you come up. The sign that you are doing it correctly is that your knees stay in line with your toes and your trunk comes slightly forward.
Amount, repetitions and progression: Each time you exercise, do 3 groups, repeating the movement 10 times in each group, pausing for 5 seconds each time. Once you can do it without pain and with your knees in line, bend a little deeper.
Stop immediately if: the knee falls inwards, you lose your balance or you get a sharp pain in the knee.
Common mistakes: Bending deeply, letting your heels lift, putting your weight on the non-operated leg only and letting the knee fall inwards.
Easier version: Bend less, and hold on more firmly with both hands.

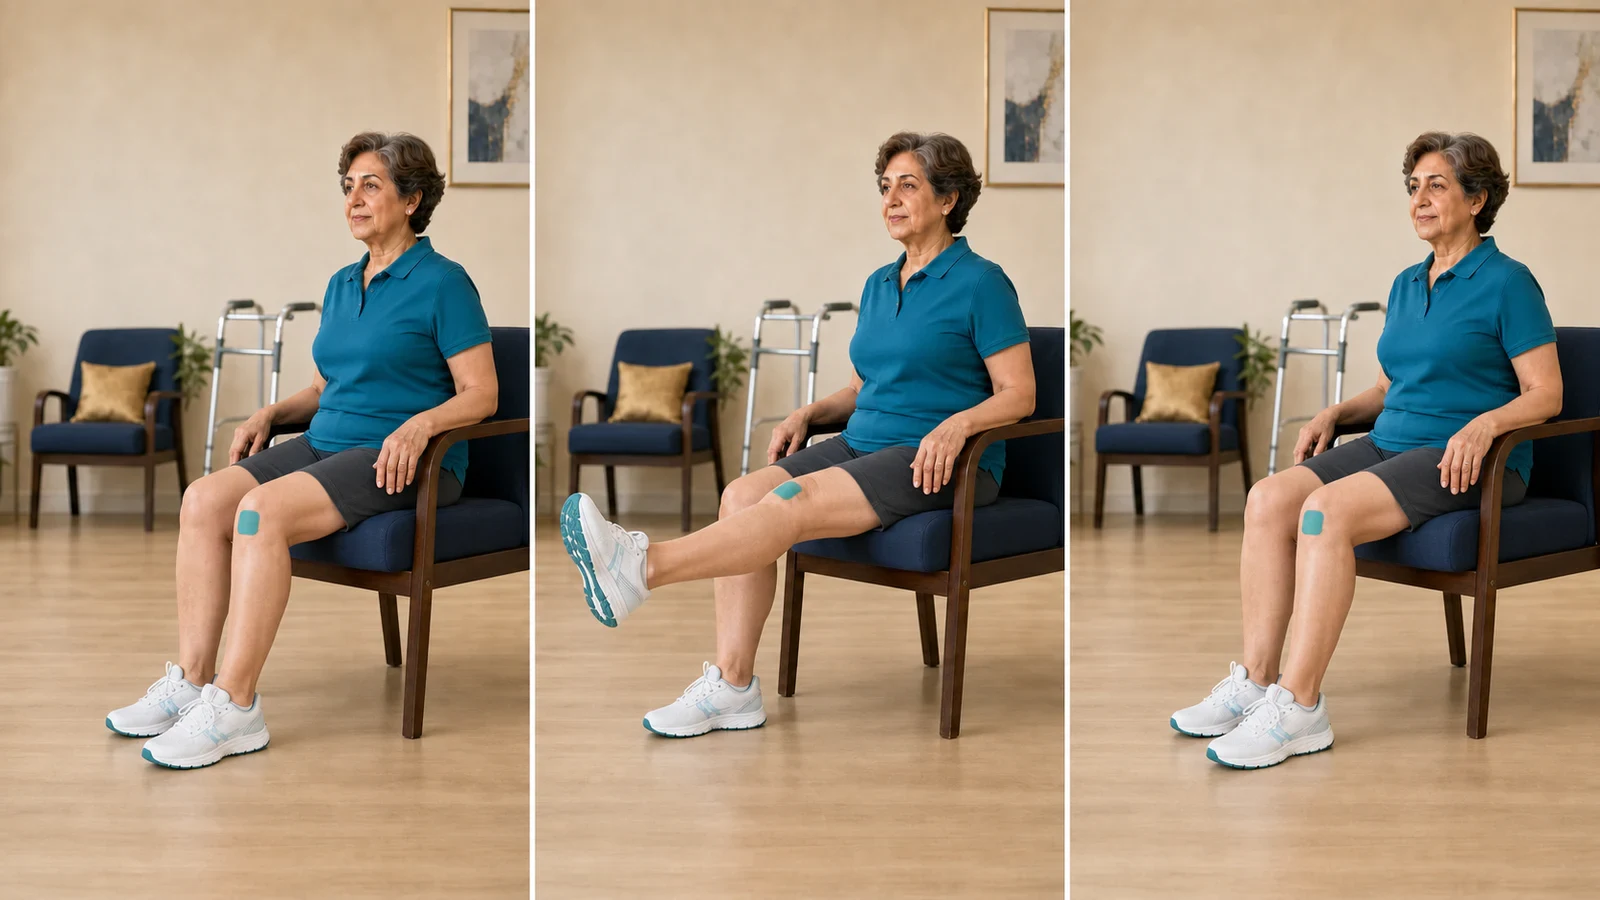
15) Knee straightening while seated (Seated Knee Extension)
Sitting on a chair, you straighten the knee fully and hold it for a few seconds so that the front thigh muscle gets stronger. Hold for 5 to 10 seconds each time; the whole exercise takes about 3 minutes. If you feel a sharp pain in the knee, or a thigh cramp does not go away even after a short rest, stop.
More detailLess detail
Before you start: This exercise strengthens the front thigh muscle in a seated position. Start from the second month. Sit on a sturdy chair with your back resting against the backrest and the soles of both feet on the floor.
How to do it:
- Tighten the front thigh muscle of the operated leg.
- Raise your lower leg until the knee is fully straight.
- Keep the knee straight.
- Lower the leg slowly until the sole of the foot rests on the floor.
Movement tips: Your thigh stays on the chair and only the lower leg comes up. Breathe out as you lift, and lower the leg slowly; your toes should point to the ceiling. The sign that you are doing it correctly is that the knee is fully straight at the top of the movement and your thigh does not lift off the chair. Tiredness at the front of the thigh is normal.
Amount, repetitions and progression: Hold it straight for 5 to 10 seconds each time and repeat until your thigh is tired; the whole exercise takes about 3 minutes.
Stop immediately if: you get a sharp pain in the knee, or a thigh cramp does not go away even after a short rest.
Common mistakes: Lifting the thigh off the chair, swinging the lower leg and letting the leg drop suddenly.
Easier version: Straighten the knee only as far as is comfortable, and hold it for a shorter time.
16) Balance exercise with support (Supported Balance)
Standing with one heel in front of the other foot’s toes, and then on one leg, brings back your balance and control of the knee. Hold each position for 30 seconds. If you lose your balance or feel dizzy, hold on to the kitchen counter at once, put your foot down and do not carry on.
More detailLess detail
Before you start: Balance is reduced after knee replacement, and practising it helps prevent falls. Do it from the second month, at the end of your exercise session. Stand beside a kitchen counter or a fixed handrail so that you can hold on at any moment, and wear closed shoes.
How to do it:
- Place one foot in front of the other, so that the heel of the front foot touches the toes of the back foot.
- Stand upright, look ahead and hold your balance; then swap the position of your feet.
- Once this position is easy, lift the non-operated leg slightly off the floor and stand on the operated leg.
- Rest your hand only lightly on the counter, and hold on firmly whenever you need to.
Movement tips: The knee of the standing leg stays straight, but do not push it backwards, and do not let your pelvis drop to one side. Breathe calmly. The sign that you are doing it correctly is that your trunk is upright and your body sways less. Do the exercise on both legs.
Amount, repetitions and progression: Hold each position for 30 seconds; once it is easy, add 10 seconds each time until you reach 1 to 2 minutes. Try standing with your eyes closed only when you can hold the same position for 30 seconds with your eyes open.
Stop immediately if: you lose your balance or feel dizzy; hold on to the counter, put your foot down and do not carry on.
Common mistakes: Standing far from the support, pushing the knee backwards, looking down, and trying the eyes-closed version too early.
Easier version: Place your feet slightly apart, and hold on with both hands.

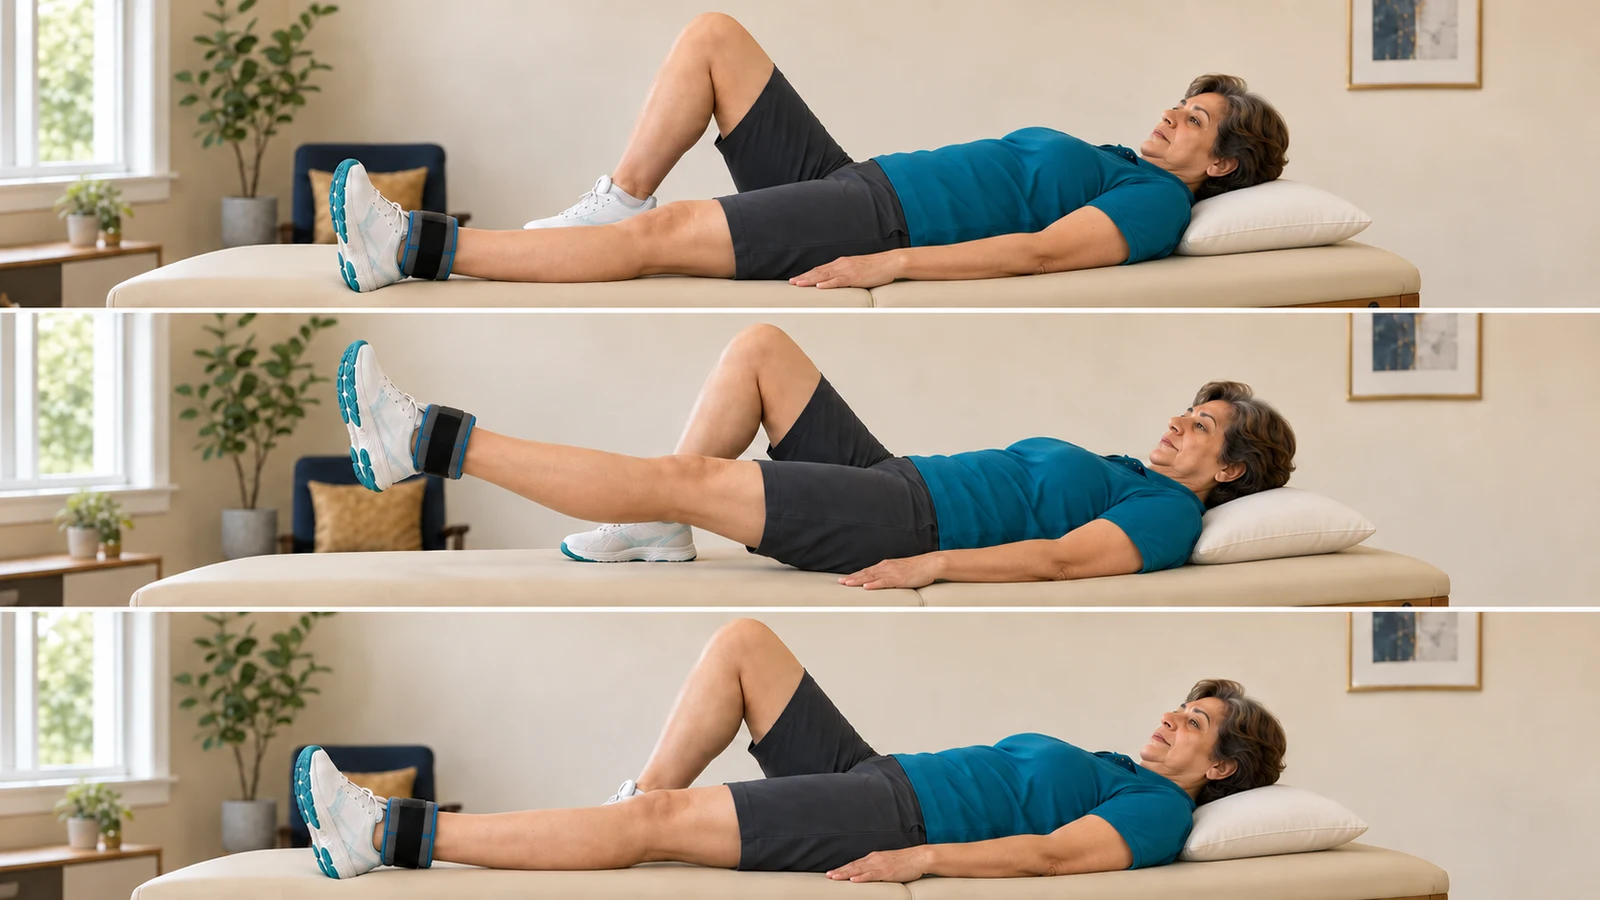
17) Exercise with an ankle weight (Knee Exercises with Resistance)
Strapping a light weight to your ankle and repeating the straight leg raise makes the thigh stronger. Start between the fourth and sixth weeks with a weight of half a kilogram to one kilogram. If the knee bends as you lift, your lower back arches or you feel a sharp pain in the knee, stop and remove the weight.
More detailLess detail
Before you start: Once the straight leg raise without a weight has become easy, a light weight makes the muscle stronger. This exercise usually starts between the fourth and sixth weeks, that is, from the end of the first month or the start of the second month. Strap an ankle weight with a hook-and-loop fastening just above the ankle of the operated leg and, as in the straight leg raise, lie on your back with the non-operated leg bent.
How to do it:
- Strap the weight firmly just above the ankle of the operated leg.
- Tighten the front thigh muscle so that the knee is fully straight.
- Lift the leg a few centimetres with the knee straight, and hold it there.
- Lower the leg slowly.
Movement tips: The knee stays straight throughout the movement; if it bends with the weight on, the weight is still too heavy for you. You can also use the same weight for knee straightening while seated. Breathe out as you lift. The sign that you are doing it correctly is that the heel and the knee rise together.
Amount, repetitions and progression: Start with a weight of half a kilogram to one kilogram, and make it gradually heavier as your strength returns. Hold the leg up for 5 to 10 seconds each time and repeat until your thigh is tired.
Stop immediately if: the knee bends as you lift, your lower back arches or you get a sharp pain in the knee; remove the weight.
Common mistakes: A heavy weight at the start, letting the knee bend, swinging the leg and strapping the weight close to the knee.
Easier version: Remove the weight and continue the straight leg raise without it.
🏋️ The third month: days 61 to 90
In the third month, the exercises become harder: steps, controlled squats, and strengthening the hip and buttock muscles. Running, jumping and contact sports (sports with bodily contact, such as football) are not recommended after knee replacement, either this month or later.
Start each new exercise with a small number of repetitions, and if pain or swelling is worse by the next morning, reduce that exercise back to the amount you managed before without trouble.
18) Low step-up (Step-Ups)
By placing the operated leg on a low step and stepping up with that same leg, you strengthen the thigh muscles for stairs. Each time you exercise, do 3 groups, repeating the movement 10 times in each group, staying on the step for 5 seconds each time. If the knee falls inwards or gives way, or you feel a sharp pain in the knee, stop.
More detailLess detail
Before you start: This exercise strengthens the muscles you need for going up stairs. Unlike the “up with the non-operated leg” rule given for the stairs at home, here you deliberately step up with the operated leg so that this same leg gets stronger. Start in the third month. Stand in front of a low step about 10 centimetres high, with a handrail or a kitchen counter within reach.
How to do it:
- Place the whole foot of the operated leg on the step.
- Shift your weight onto this leg and step up until the non-operated leg reaches the step beside it, without putting weight on the non-operated leg.
- Stand on the step.
- Slowly bring the non-operated leg back down to the floor, controlling the movement with the leg on the step.
Movement tips: The knee on the step always stays in line with your toes and does not fall inwards. The leg on the step does the main work; do not push yourself up with the back leg. Breathe calmly. The sign that you are doing it correctly is that your pelvis stays level and you come down slowly. Feeling your buttock and thigh muscles working is normal.
Amount, repetitions and progression: Each time you exercise, do 3 groups, repeating the movement 10 times in each group, staying on the step for 5 seconds each time. Once it is easy, gradually increase the height of the step, from about 10 centimetres up to about 30 centimetres.
Stop immediately if: your knee falls inwards or gives way, or you get a sharp pain in the knee.
Common mistakes: Pushing off with the back leg, letting the knee fall inwards, letting go of the handrail and coming down suddenly.
Easier version: Use a lower step, and hold the handrail with both hands.

19) Squat to a chair (Squat to Chair)
Go down as if you were sitting on a chair, just touch the chair and stand up again. Start with one short group of repetitions and gradually build up to 3 groups each time you exercise, with 15 to 25 repetitions in each group. If your knee gives way or falls inwards, or you feel a sharp pain in the knee, sit down and do not carry on.
More detailLess detail
Before you start: This exercise practises sitting down and standing up without help from your hands, and makes your thighs and buttocks stronger. Start in the third month, once you can get up from a chair comfortably using your hands. Stand in front of a sturdy chair without wheels, with your feet shoulder-width apart, your toes pointing forward and your arms stretched out in front of you.
How to do it:
- Slowly take your buttocks back and bend your knees, as if you were about to sit down.
- Go down until your buttocks just touch the chair; do not sit down.
- Press through your heels and slowly stand up straight.
- Repeat; your knees always point forward, in line with your toes.
Movement tips: Keep your weight equal on both feet and mostly on your heels. Do not let your knees fall inwards, and let your trunk come slightly forward. Breathe in as you go down and breathe out as you come up. The sign that you are doing it correctly is that you go down slowly and your buttocks only touch the chair.
Amount, repetitions and progression: Start with one short group of repetitions; the aim is 3 groups each time you exercise, with 15 to 25 repetitions in each group. Do this exercise 5 to 7 days a week.
Stop immediately if: your knee gives way or falls inwards, or you get a sharp pain in the knee; sit down.
Common mistakes: Dropping onto the chair, lifting the heels, letting the knees fall inwards and shifting your weight onto the non-operated leg.
Easier version: Choose a higher chair, or at first sit down fully and then stand up again.

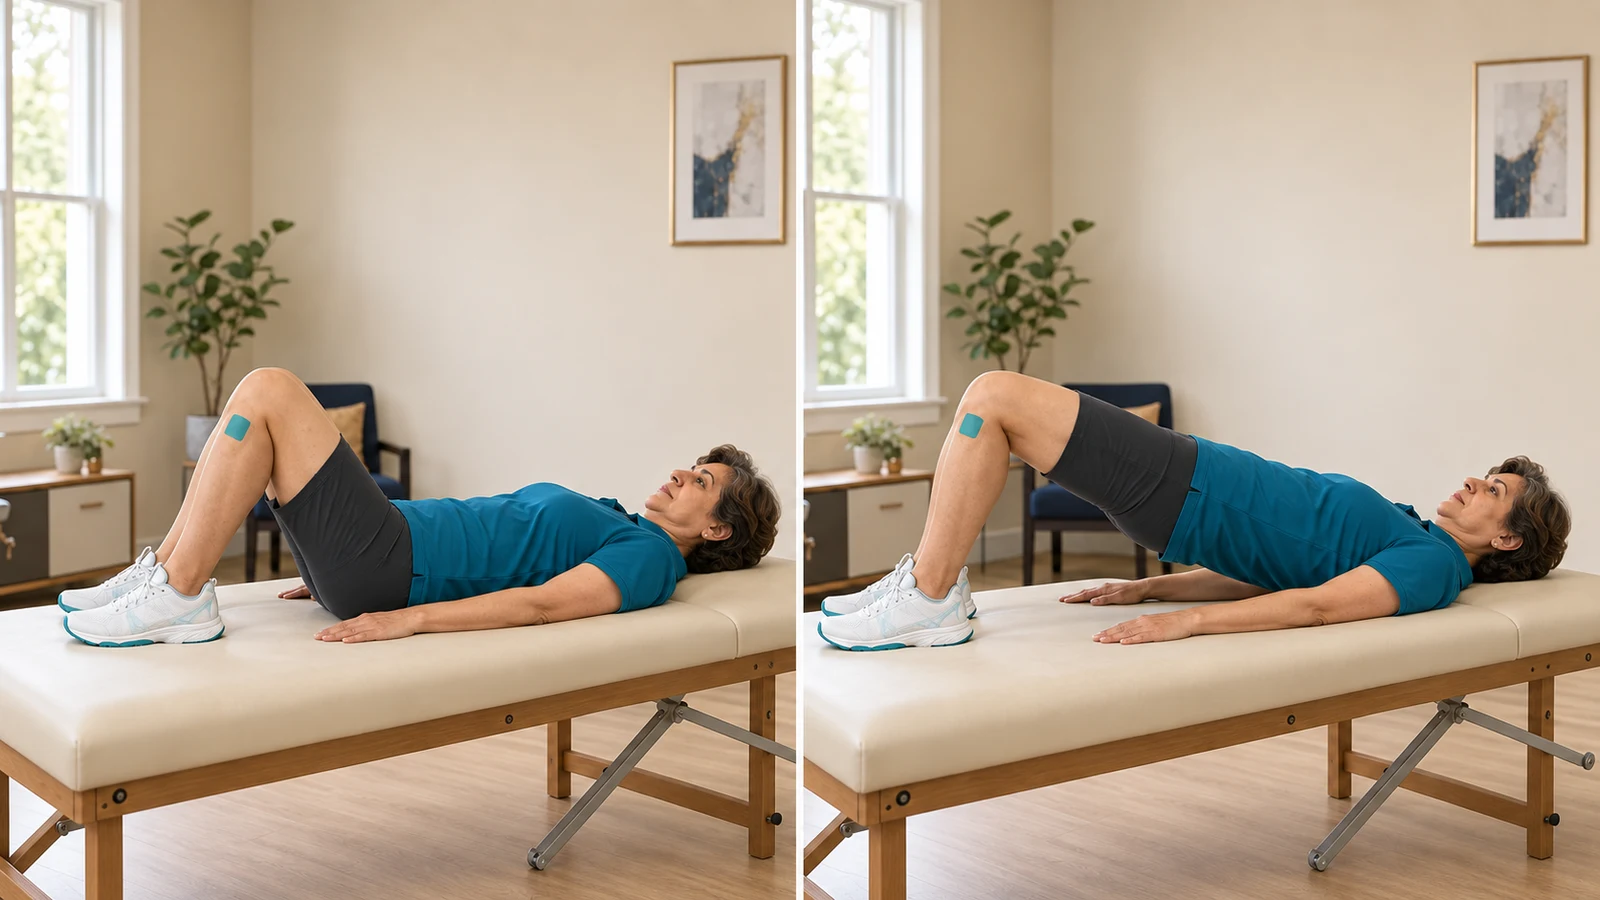
20) Bridge (Bridges)
Lifting your buttocks off the surface strengthens the buttock muscles and the hamstrings (back-of-thigh muscles). Each time you exercise, do 3 groups, repeating the movement 10 times in each group, holding for 5 seconds at the top. If you get a sharp pain in your lower back or knee, or a cramp in the hamstrings, stop.
More detailLess detail
Before you start: The buttock muscles help the knee on stairs, when getting up and with balance. Start from the third month. Lie on your back on a firm bed or a mat, with both knees bent, the soles of your feet flat on the surface hip-width apart, and your arms by your sides.
How to do it:
- Tighten your stomach and buttock muscles.
- Slowly lift your buttocks until your body forms a straight line from your shoulders to your knees.
- Stay at the top.
- Slowly lower your buttocks.
Movement tips: Keep your weight equal on both feet, and do not let your knees drift apart. Do not arch your lower back; lift only as far as a straight line from your shoulders to your knees. Breathe calmly. The sign that you are doing it correctly is that your pelvis rises straight and level.
Amount, repetitions and progression: Each time you exercise, do 3 groups, repeating the movement 10 times in each group, and stay at the top for 5 seconds each time.
Stop immediately if: you get a sharp pain in your lower back or knee, or a cramp in the hamstrings.
Common mistakes: Arching the lower back, letting one side of the pelvis drop and jerking up.
Easier version: Do not lift your buttocks as high.
21) Sideways walking with a band (Lateral Band Walk)
Taking short steps sideways with a band around your thighs strengthens the muscles at the side of the hip, so that the knee falls inwards less when you walk. Each time you exercise, do 3 groups of steps, with 10 steps to each side in each group. If you get a sharp pain in the knee, lose your balance or your lower back starts to hurt, stop.
More detailLess detail
Before you start: The muscles at the side of the hip keep the pelvis level when you walk. Start in the third month, once you can step up onto the low step well. Tie a light exercise band around both thighs, just above the knees, and stand beside a handrail or kitchen counter.
How to do it:
- Bend your knees slightly and place your feet hip-width apart so that the band is slightly stretched.
- Take a short step sideways with the leg on the side you are moving towards.
- Slowly bring the other leg closer, without letting the band go slack.
- Take a few steps to one side, then come back the other way.
Movement tips: Keep your trunk upright, and do not let it sway from side to side. Keep your toes pointing forward and your knees in line with your toes. Keep the steps short and slow. The sign that you are doing it correctly is that the band stays slightly stretched the whole way and your knees do not come closer together.
Amount, repetitions and progression: Each time you exercise, do 3 groups of steps, with 10 steps to each side in each group. Start with a light band, and when it becomes easy, use a firmer band.
Stop immediately if: you get a sharp pain in the knee, lose your balance or your lower back starts to hurt.
Common mistakes: Swaying the trunk, taking long steps, letting the knees fall inwards and letting the band go completely slack.
Easier version: Start without a band, or with a looser band and shorter steps.

🎯 After 90 days: a maintenance programme and returning to activity
Full recovery after knee replacement takes several months, and it may take up to a year before you feel that the knee is really your own. After the 12-week programme ends, continue the exercises 2 to 3 days a week so that your muscles stay strong.
To help the artificial joint last longer, choose low-impact exercise such as walking, cycling, golf and light hiking. Running, jumping, skiing and contact sports are not recommended.
22) Controlled step-down
You stand on a step on the operated leg and slowly lower the other leg down to the floor, so that the knee regains the control it needs for coming down stairs. Do 3 sets of 10 repetitions. If your knee falls inwards or gives way, or you feel a sharp pain in the knee, stop.
More detailLess detail
Before you start: Coming down stairs is the hardest everyday task for the operated knee. This strengthening exercise deliberately differs from the rule for the stairs at home (“down with the operated leg”): here the operated leg stays on the step so that it gets stronger; when coming down the stairs at home, follow the “Going down stairs with the handrail and cane” card. Start after the third month, once stepping up onto a low step has become easy. Stand on a low step, about 10 centimetres high, beside a handrail; the foot of the operated leg should be fully on the step, and the non-operated leg should stay beside it, in the air, beyond the edge of the step.
How to do it:
- Hold the handrail and move your weight fully onto the operated leg.
- Slowly bend the knee of the leg on the step until the heel of the non-operated leg comes close to the floor.
- Touch the floor with the heel only, and do not put any weight on it.
- Straighten the knee of the leg on the step and slowly come back up.
Movement tips: Keep the knee of the leg on the step in line with your toes, and do not let it fall inwards; keep your pelvis level. Go down more slowly than you come up, and breathe calmly. The sign that you are doing it correctly is that the heel of the non-operated leg only touches the floor and the operated knee bends without shaking.
Amount, repetitions and progression: 3 sets of 10 repetitions. Once you can do it without pain and with your knee staying in line, gradually increase the height of the step.
Stop immediately if: your knee falls inwards or gives way, or you get a sharp pain in the knee.
Common mistakes: Letting the knee fall inwards, dropping down suddenly, putting weight on the lowered leg and letting go of the handrail.
Easier version: Use a lower step, and do not go down as far.

23) Gradually increasing your walking (Walking Progression)
Build up your walking little by little: first on flat ground, then on uneven ground and uphill. Each time your current walking time becomes easy, add 5 minutes to your walk. If you start to limp, or get a sharp pain in the knee, chest pain, shortness of breath or dizziness, stop; for chest pain or shortness of breath, follow the warning-signs section.
More detailLess detail
Before you start: Walking, especially on different surfaces, is a good way to rebuild endurance after knee replacement. Start a regular programme after the third month, once you walk without a cane and without a limp. Wear comfortable shoes with non-slip soles, and choose a flat, familiar route at first.
How to do it:
- Warm up with a few minutes of slow walking.
- Walk at a comfortable pace; your heel touches the ground first, then the sole of your foot, then your toes.
- Make each step the same length as the step of the other leg.
- At the end, walk more slowly for a few minutes.
Movement tips: Your walking should be even and free of a limp; if a limp appears, shorten that day’s walk. Once a flat route is comfortable, add uneven ground, uphill and downhill. The sign that you are doing it correctly is that your steps are even on both sides and your trunk is upright.
Amount, repetitions and progression: When your current time becomes easy, add 5 minutes to it. If you see in the morning that the swelling has increased, walk for less time that day. Walking does not replace the strengthening exercises.
Stop immediately if: you start to limp or get a sharp pain in the knee, or you get chest pain, shortness of breath or dizziness; stand still or sit down, and for chest pain or shortness of breath follow the warning-signs section.
Common mistakes: Suddenly increasing the distance, starting with uphill walking and carrying on while limping.
Easier version: Shorten the route, or walk in two shorter sessions.

24) Stationary bike for endurance (Exercise Bike for Endurance)
After the third month, you continue the stationary bike for endurance and slowly build up to 20 to 30 minutes, 3 to 4 times a week. If you get a sharp pain in the knee, chest pain, unusual shortness of breath or dizziness, stop and get off slowly; for chest pain or shortness of breath, follow the warning-signs section.
More detailLess detail
Before you start: Cycling keeps your muscles strong and your knee flexible, without putting impact on the knee. Start this programme after the third month, once 15 minutes of pedalling is easy. Set the saddle so that your knee is almost straight when the pedal is at its lowest point.
How to do it:
- Pedal slowly with low resistance to warm up.
- Carry on at a steady, comfortable pace.
- Pedal backwards for part of the time so that other muscles work too.
- At the end, pedal more slowly for a few minutes and get off carefully.
Movement tips: Increase the resistance only when you can pedal comfortably for 20 minutes at the current resistance. Your knee should move up and down in line with your toes, and your pelvis should stay steady on the saddle. The sign that you are doing it correctly is that your knee is almost straight at the lowest point and bent without strain at the highest point.
Amount, repetitions and progression: Increase the time slowly until you reach 20 to 30 minutes, 3 to 4 times a week. If the pain or swelling in your knee is worse by the next morning, reduce the time and the resistance of the next session.
Stop immediately if: you get a sharp pain in the knee, chest pain, unusual shortness of breath or dizziness; get off slowly, and for chest pain or shortness of breath follow the warning-signs section.
Common mistakes: Too much resistance, a saddle set too low, pedalling fast and your pelvis shifting on the saddle.
Easier version: Shorten the time and reduce the resistance.

25) Balance with floor touches in different directions (Multidirectional Balance Reach)
You stand on the operated leg and, with the toes of the other foot, gently touch the floor in front, to the side and behind. Do each round for 30 seconds. If you lose your balance or feel dizzy, hold the kitchen counter and do not carry on.
More detailLess detail
Before you start: This exercise strengthens your balance in everyday movements, such as turning and picking something up from beside you. Start after the third month, once you can stand on one leg for 30 seconds with your eyes open. Stand beside the kitchen counter and rest one hand lightly on it.
How to do it:
- Move your weight onto the operated leg; keep its knee very slightly bent, and do not push it backwards.
- With the toes of the non-operated leg, gently touch the floor in front of you and come back.
- Do the same to the side and then behind.
- Then swap legs and practise on the non-operated leg too.
Movement tips: Keep the standing leg still, and do not let its knee fall inwards; keep your pelvis level. Only touch the floor, and do not move your weight onto the touching leg. The sign that you are doing it correctly is that your trunk is upright and the standing foot does not move.
Amount, repetitions and progression: Do each round for 30 seconds; when it becomes easy, add 10 seconds each time until you reach 1 to 2 minutes.
Stop immediately if: you lose your balance or feel dizzy; hold the kitchen counter and do not carry on.
Common mistakes: Moving your weight onto the touching leg, letting the knee of the standing leg fall inwards and moving away from your support.
Easier version: Touch the floor closer to you, and support yourself with both hands.

🚗 Driving, work, prayer and daily activities
For each daily activity, the approximate timing and the condition you need to meet are set out below. The figures come from Dr Emad’s clinic programme and from published research. Read the timing and the condition for each activity together, because reaching the date without meeting that condition is not enough.
- Driving: In Dr Emad’s programme, driving starts about 6 weeks after surgery, whether the right or the left knee was operated on. The condition is that you are not taking an opioid pain medicine, alprazolam or gabapentin, that you can get in and out of the car comfortably, and that in an emergency you can press the brake pedal quickly and without pain. Before your first drive, practise an emergency stop a few times in the car with the engine off.
- Work: In Dr Emad’s programme, you return to desk work 4 to 6 weeks after surgery and to heavy work about 3 months after surgery. You return to work involving long periods of standing about 6 to 12 weeks after surgery, depending on the type of work, provided you have set the cane aside and walk without a limp. In the first 3 months, leave heavy household tasks, such as moving heavy objects, to others.
- Prayer: In the first 3 months, pray on a chair. From about 3 months after surgery, if kneeling on a soft mat is comfortable for you, do the bowing (rukūʿ) as usual and the prostration (sujūd) on the floor, but keep using a chair for the tashahhud (sitting) and for long periods of sitting. In choosing the alternative position, follow the guidance of your own religious authority (marjaʿ).
- Sitting on the floor and the toilet: Sitting cross-legged, sitting on your knees for long periods and using a squat toilet are not recommended; use a chair and a sit-down toilet or a raised toilet seat. In the first 6 weeks, also do not cross your legs.
- Sleep: You can sleep on your back, on your side or on your front; just do not put a pillow under the knee.
- Sexual activity: Once the wound has closed, usually from the third to the sixth week, you can resume sexual activity. Choose a position in which the operated knee is not deeply bent and does not take your body weight; if the knee hurts, stop.
- Long journeys: In Dr Emad’s programme, while you are taking the blood thinner, that is, in the first 4 to 5 weeks, postpone long flights and road journeys of several hours if possible. If you have to travel, stop several times on the way, walk a little and do ankle pumps. On a plane, the change in pressure and long periods without moving may make the operated leg swell.
- Sport: Most patients return to low-impact sport about 4 months after surgery. Walking, cycling, golf and light hiking are good choices; running, jumping, skiing and contact sports are not recommended.
❓ Frequently asked questions
1) When are the stitches removed?
In Dr Emad’s programme, stitches or staples are removed at the clinic about two weeks (14 days) after surgery, at your first visit. Do not remove the stitches, staples or the adhesive strips on the wound yourself.
2) When can I take a shower?
From 48 hours after surgery you may take a short shower, provided the wound is dry and the waterproof dressing is intact. If water gets under the dressing, change it at that moment for a clean, dry dressing.
3) How far will the artificial knee bend, and when?
Knee bending usually reaches about 90 degrees in the first to second week. By the seventh week, it usually reaches about 100 to 110 degrees. The average final bend is about 115 degrees; this is enough for going up stairs and getting into a car, but full bending like that of a healthy knee usually does not come back. Your range of motion before surgery also affects the result.
4) What should I do if bending or straightening of the knee does not improve?
If bending or straightening of the knee has not improved for two weeks in a row, call the clinic, whatever stage of recovery you are at. Most of the time, physiotherapy and regular exercise solve the problem; if they do not, the doctor may suggest manipulation under anaesthesia, a procedure in which the knee is gently bent, without any incision, so that the adhesions are released. Do not force the knee to bend by yourself, pushing through pain.
5) How long will the pain and swelling last?
In the first 6 to 8 weeks the pain will often worry you, but it is normal, and it may take up to 2 months to settle. Mild swelling may last 3 to 6 months, and pain during activity and at night is common for several weeks. Swelling that comes on suddenly or gets worse day by day, especially together with calf pain, or pain that is not controlled by your medicines, is not part of this process; in that case, follow the warning-signs section.
6) Is a clunking or clicking sound from the artificial knee normal?
Yes. When bending the knee or walking, most patients feel or hear the sound of the joint’s metal and plastic parts touching. This sound is normal, and it usually draws your attention less as time goes on. If a new sound comes with pain, swelling or the knee giving way, call the clinic.
7) Will the numbness of the skin beside the wound go away?
Most patients have a little numbness in the skin around the wound, especially on the outer side of the knee, and this is normal. This numbness lessens with time. But if numbness or tingling in the lower leg and the sole of the foot is still there after one week, or is new, call the clinic the same day.
8) Does kneeling damage the artificial knee?
No. Kneeling is sometimes uncomfortable, but it does not damage the artificial joint. In Dr Emad’s programme, kneeling on a soft mat is allowed from about 3 months after surgery, if it is comfortable, but sitting on your knees for long periods and sitting cross-legged are not recommended.
9) When can I stop using the cane?
In Dr Emad’s programme, a walker is needed for about 2 to 4 weeks, and then a cane until you walk without a limp; this is usually around the sixth week. What counts is walking without a limp, not just reaching a date.
10) When are the check X-rays taken?
In Dr Emad’s programme, one X-ray is taken in hospital after the operation, one at about the sixth week and one at one year. After that, keep coming to your periodic follow-up visits, even if you have no problems.
11) Do I need antibiotics before dental treatment?
In Dr Emad’s clinic programme, before any invasive dental procedure, such as a tooth extraction or scaling, you take a preventive antibiotic, for life. Tell your dentist that you have a knee implant, and check with the clinic before your appointment.
12) Can an infection elsewhere in the body reach the artificial knee?
Yes; germs that enter the bloodstream from the teeth, a urinary infection or a skin wound may settle around the implant. For this reason, get tooth infections, urinary symptoms or skin wounds treated early, and tell every doctor you see that you have a knee implant.
13) How many years does an artificial knee last?
More than 90 per cent of modern total knee replacements are still working well 15 years after surgery. In a review published in 2019 using national registry data, about 82 per cent had lasted 25 years without revision surgery. The 25-year figures concern earlier patients and implants; neither figure guarantees your individual result.
14) Do weight and the type of exercise affect how long the artificial knee lasts?
Yes. The plastic part of every implant gradually wears with normal use, and excess weight or high-impact exercise makes this wear faster. Keeping a healthy weight, doing low-impact exercise and keeping your muscles strong help the implant last longer.
15) Can I have magnetic resonance imaging (MRI) with an artificial knee?
Yes, but before the MRI, tell the doctor and the imaging centre that you have a knee implant. The metal of the implant may blur the image and make it harder to see damage around the implant.
16) Will an artificial knee set off the airport metal detector?
It may. Before going through the detector, tell the security officer that you have a knee implant. Setting off the detector does not mean the implant is damaged.
✅ Summary and appointments
Recovery after knee replacement moves forward through regular wound care, controlling swelling, preventing blood clots and the gradual return of movement and strength. Do the exercises correctly and in the amounts set out in the programme, and do not forget full straightening of the knee in the first weeks.
If you have not yet decided on surgery or are getting ready for it, the guide to total knee replacement before surgery explains the reasons for the operation, preparation and the day of surgery.
If you have a sign from the “Call the clinic the same day” list in the warning-signs section, call that same day. For questions about bending and straightening the knee, swelling or your exercise programme, call Dr Jalil Emad’s clinic on 09137825207, or book an appointment online. In an emergency, do not wait for the clinic to reply; follow the instructions in the warning signs section.
To learn more about this treatment, visit the related service page: Joint replacement and reconstruction.
Related guides: Pre-operative guide: Total Knee Replacement: The Pre-Operative Guide · Service page: Joint Replacement & Reconstruction · Also related: Kneecap pain and softening of the cartilage behind the kneecap
This content is provided for general education only and does not replace an examination, advice from your treating doctor, your discharge sheet or your surgeon’s specific protocol. Timing, range of motion, weight-bearing and the amount of exercise differ from person to person and depend on the type of operation and your own condition. Do not change your medicines, dressing or exercise programme without checking with the clinic.
📚 Scientific references
View scientific references
- Clinical practice guideline for physical therapist management of total knee arthroplasty: revision 2026. Phys Ther 2026 (APTA; PMID 42506877)
- AAOS OrthoInfo: Total Knee Replacement Exercise Guide
- AAOS OrthoInfo: Activities After Total Knee Replacement
- AAOS OrthoInfo: Total Knee Replacement
- AAHKS: Home Therapy Exercises After Total Knee Replacement (print guide)
- NHS: Recovering from a knee replacement
- MedlinePlus: Knee joint replacement – discharge
- NICE NG157: Joint replacement (primary): hip, knee and shoulder – recommendations
- NICE NG125: Surgical site infections: prevention and treatment – recommendations
- Robert Jones and Agnes Hunt Orthopaedic Hospital NHS FT: Knee Replacement Physiotherapy booklet
- Gateshead Health NHS FT: Physiotherapy Following Knee Replacement Surgery
- West Hertfordshire Teaching Hospitals NHS Trust: Physiotherapy after your Knee Replacement
- Ebert JR, Munsie C, Joss B. Guidelines for the early restoration of active knee flexion after total knee arthroplasty. Arch Phys Med Rehabil 2014;95(6):1135-40 (PMID 24602550)
- Evans JT et al. How long does a knee replacement last? Lancet 2019;393(10172):655-663 (PMID 30782341)
- Amin RM, Vasan V, Oni JK. Kneeling after Total Knee Arthroplasty. J Knee Surg 2020;33(2):138-143 (PMID 30602194)
- High rate of return to low-impact physical activity or sports after total and unicompartmental knee arthroplasty: systematic review with meta-analysis. Knee Surg Sports Traumatol Arthrosc 2026 (PMID 41527885)
- MedlinePlus: Vitamin D
- MedlinePlus: Vitamin C
- DailyMed: Eliquis (apixaban) prescribing information
- DailyMed: Alprazolam prescribing information
- DailyMed: Gabapentin prescribing information
- DailyMed: Acetaminophen and codeine phosphate tablets prescribing information
- DailyMed: Oxycodone hydrochloride prescribing information
- DailyMed: Cephalexin capsules prescribing information
- MedlinePlus: Alprazolam
- MedlinePlus: Surgical wound care – closed
- Platelet-Rich Plasma (PRP): American Academy of Orthopaedic Surgeons patient information (accessed2026-10-11). Full text
- The Application of Platelet-Rich Plasma for Patients Following Total Joint Replacement: A Meta-Analysis of Randomized Controlled Trials and Systematic Review. Frontiers in Surgery. 2022. DOI:10.3389/fsurg.2022.922637. Full text
- FDA. New Safety Measures Announced for Opioid Analgesics, Prescription Opioid Cough Products, and Benzodiazepines. 2016.
- FDA. Boxed Warning updated to improve safe use of benzodiazepine drug class. 2020.